
19 Oct What the Evidence Says About Screening for Men Over 35
Health Screening Notice: Screening recommendations differ between countries and change over time, and the right tests and intervals depend on your age, family history and risk factors. Screening is not a substitute for medical care: see a doctor promptly for symptoms such as chest pain, shortness of breath, blood in the stool, unexplained weight loss or urinary changes, even if recent results were normal. This post is for general information only. Clinics named or linked in this post are not warranted or endorsed by MedicalResearch.com or Eminent Domains Inc.
Screening is one of the most studied areas of medicine, and the evidence for it is more nuanced than the marketing around it. For men over 35, the research supports a clear conclusion: targeted, regular screening for the right conditions can catch disease earlier, but the details matter.
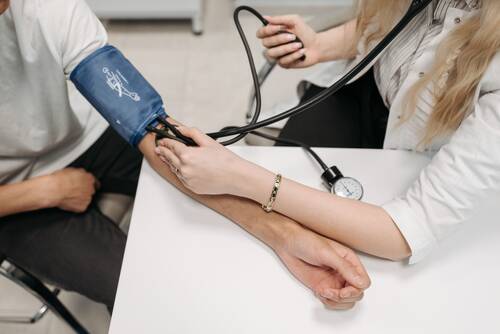
Cardiovascular disease remains the single largest cause of death for men in most high-income and middle-income countries. Large cohort studies and clinical guidelines consistently support blood pressure measurement from early adulthood and lipid assessment from around age 35 to 40, earlier where family history is significant. Some guidelines also support adding ApoB to standard lipid panels, because it counts atherogenic particles more directly than LDL cholesterol and can refine risk prediction.
[caption id="attachment_76645" align="aligncenter" width="500"] Photo by Pavel Danilyuk[/caption]
