
Melanoma
22 May EWG Urges Sunscreen Companies and Consumers To Go Oxybenzone-Free By 2020
MedicalResearch.com Interview with: Carla Burns, M.S.
Environmental Working Group
She is one of the coauthors of the 2018 Guide to Sunscreens.
MedicalResearch.com: What is the background for the EWG report?
Response: Environmental Working Group (EWG) published its first Sunscreen Guide in 2007.
When we first started the guide, many sun protection products sold in the U.S. were not as safe and used misleading marketing claims.
Throughout the years, EWG has continued to find that a common sunscreen ingredient, oxybenzone, poses a hazard to human health and the environment. Despite EWG’s efforts to draw attention to the health hazards associated with this ingredient over the last 12, oxybenzone remains widely used in chemical-based sunscreens. So, this year, we are ramping up our efforts to rid the market of this ingredient by launching a campaign to urge companies and consumers to go oxybenzone-free by 2020.
17 May SKINDER App Teaches Intuitive Visual Diagnosis of Melanoma
MedicalResearch.com Interview with: [caption id="attachment_41796" align="alignleft" width="200"]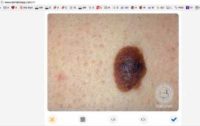 Image from SKINDER APP[/caption]
Michael S. Kolodney, MD, PhD
Section of Dermatology, Department of Medicine
West Virginia University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Melanoma is easily curable if recognized early. Dermatologists are good at spotting melanomas because they develop an innate sense of how melanomas appear after examining thousands of malignant and benign lesions. In contrast, most medical students are relatively disadvantaged by their limited dermatology exposure. We felt that too little experience, rather than lack of knowledge of the rules, is the primary barrier to development of pattern-recognition and intuition as a reliable tool for melanoma diagnosis in non-experts. To remedy this problem, we developed a novel web-based application to mimic the training of a dermatologist by teaching medical students intuitive melanoma diagnosis in a highly condensed period of time.
Our application, which we call Skinder, teaches intuitive visual diagnosis of melanoma by quickly presenting the learner with thousands of benign and malignant skin lesions. The user makes rapid binary decisions, by swiping right for benign or left for malignant, and receives instant feedback on accuracy. With this application, the learner can amass a mental repository of diagnostic experience in a short amount of time. To determine if intuitive visual diagnosis training is superior to a traditional rule-based approach, we compared our web-based application to a rules based approach, the publicly available INFORMED Skin Education Series.
Medical students were tested on the ability top differentiate melanomas from benign pigmented lesions before and after training with either Skinder of the Informed Skin Education Series. The pre-test mean for the Skinder group was 75% correct, compared to 74.7% correct for the INFORMED group. The post-test mean for the skinder application group was 86.3% correct, compared to 77.5% correct for the INFORMED group which was highly signifcant.
18 Apr PAs Do More Biopsies, Find Less Early Melanoma than Dermatologists
Posted at 15:52h
in Author Interviews, Cancer Research, Dermatology, JAMA, Melanoma, Primary Care, University of Pittsburgh
MedicalResearch.com Interview with:
[caption id="attachment_34201" align="alignleft" width="200"] Dr. Laura K. Ferris[/caption]
Laura K. Ferris MD, PhD
Associate Professor, University of Pittsburgh Clinical and Translational Science Institute
Director of Clinical Trials, UPMC Department of Dermatology
University of Pittsburgh
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Dermatology is one of the greatest utilizers of physician extenders, including physician assistants (PAs) in medicine. The scope of practice of PAs has also expanded over time from a role in assisting the dermatologist to taking a more independent role and many PAs now do skin cancer screening examinations and make independent decisions about which lesions are suspicious for skin cancer and need to be biopsied.
Our main findings were that, overall, in comparison to board-certified dermatologists, PAs were more likely to perform biopsies of benign lesions. For every melanoma that they found, PAs biopsied 39 benign lesions whereas dermatologists biopsied 25.
In addition, PAs were less likely than dermatologists to diagnose melanoma in situ, the earliest and most curable, but also hardest to identify and diagnose, form of melanoma. However, PAs had a similar rate of diagnosing the more clinically-obvious forms of skin cancer, including invasive melanoma, basal cell carcinoma, and squamous cell carcinoma.
24 Mar Wistar Study Targets Telomeres To Treat Resistant Melanoma
MedicalResearch.com Interview with: Gao Zhang, Ph.D. Staff scientist in the Herlyn Lab The Wistar Institute MedicalResearch.com: What is the background for this study? Response: The past 7 years have witnessed the great success in treating patients with unresectable or metastatic melanoma. Despite the breakthrough of molecularly targeted therapies and immune checkpoint blockade therapies, a majority of patients have experienced the rapid tumor recurrence and progression, following the dramatic regression. There is an urgent and unmet need to treat therapy-resistant tumors.23 Mar USPSTF: Behavioral Counseling of Children and Teens to Prevent Skin Cancer Recommended
Posted at 12:00h
in Author Interviews, Cancer Research, Dermatology, Environmental Risks, JAMA, Melanoma
MedicalResearch.com Interview with:
[caption id="attachment_40724" align="alignleft" width="142"] Dr. Epling[/caption]
John W. Epling, Jr., M.D., M.S.Ed., Task Force Member
Dr. Epling is is a professor of Family and Community Medicine at the Virginia Tech Carilion School of Medicine in Roanoke, VA. He is also the Medical Director of Research for Family and Community Medicine, Medical Director of Employee Health and Wellness for the Carilion Clinic, and maintains an active clinical primary care practice.
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Skin cancer is the most common type of cancer in the U.S., affecting millions of people every year. The Task Force looked at the latest research to see if clinicians can help people prevent skin cancer by providing counseling about ways to reduce risk, including using sunscreen, wearing protective clothing, and avoiding sunlight during peak hours.
[caption id="attachment_40730" align="alignleft" width="150"]
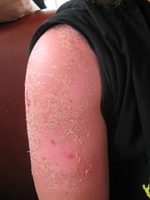 Sunburn damage - wiki image[/caption]
Based on our review of the evidence, we found that counseling younger patients with a fair skin type and their parents is effective at encouraging these sun protective behaviors. By helping reduce their patients’ exposure to harmful UV rays, clinicians can decrease their risk for skin cancer. As such, we recommend that clinicians provide counseling to people who are six months to 24 years old and have a fair skin type. For adults over 24 with a fair skin type, clinicians should consider the individual’s risks for skin cancer when deciding whether or not to provide counseling.
11 Mar Dermoscopy Helps Improve Diagnosis of Early Melanoma
MedicalResearch.com Interview with: [caption id="attachment_40495" align="alignleft" width="200"]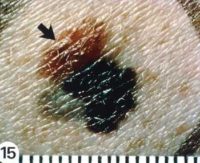 Superficial spreading melanoma arising from a dysplastic nevus
NCI image[/caption] Aimilios Lallas, PhD First Department of Dermatology, School of Medicine Aristotle University Thessaloniki, Greece MedicalResearch.com: What is the background for this study? What are the main findings? Response: Our goal today is to recognize melanoma at the earliest stage, ideally before it invades the dermis and acquires metastatic potential. Melanoma-specific dermoscopic criteria have been tested mainly in the context of invasive melanoma. Although they were proven valid melanoma predictors, the question still remains if they are strong enough to diagnose melanoma in situ (MIS). Our aim was to investigate the diagnostic accuracy of dermoscopic criteria for the diagnosis of melanoma in situ. We identified 5 main positive dermoscopic indicators of MIS: atypical network, regression, irregular hyperpigmented areas, prominent skin markings and angulated lines.
14 Feb Another Obesity Paradox: Obese Males Have Survival Advantage in Melanoma
MedicalResearch.com Interview with: [caption id="attachment_40044" align="alignleft" width="300"]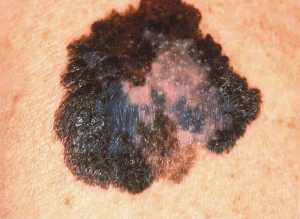 This image depicts the gross appearance of a cutaneous pigmented lesion, which had been diagnosed as superficial spreading malignant melanoma (SSMM). Note the roughened edges of this mole, and its heterogeneous, mottled, multicolored appearance, which are all characteristics that should evoke suspicions about its classification.
CDC Image[/caption] Jennifer McQuade, M.D., lead author Melanoma Medical Oncology The University of Texas MD Anderson Cancer Center MedicalResearch.com: What is the background for this study? What are the main findings? Response: Melanoma is the most deadly of the common skin cancers, and for many years we lacked effective therapies for patients with disease that had spread (metastatic). Over the past 7 years, there has been FDA approval of 2 new classes of drugs that have dramatically improved the survival of patients with metastatic melanoma. Checkpoint inhibitor immunotherapies “take the brakes” off patients’ immune system to allow the immune system to eliminate the cancer. Targeted therapies turn off key molecules expressed by some tumors (BRAF mutant) that they rely on for sustained growth and division. While these types of therapies can result in dramatic long-term disease control in some patients, others may not have any shrinkage of their tumors. Some differences may lie in the tumors themselves, but there is also increasing evidence that “host” factors such as the microbiome and lifestyle choices might influence outcomes in cancer patients. Obesity has been associated with an increased risk of many cancers, and is in fact poised to overtake smoking as the leading preventable cause of cancer. One of the ways that obesity may increase tumor growth is by increasing levels of insulin and other growth factors which then activate a pathway called the PI3K pathway that leads to continued tumor growth. As that PI3K pathway has also been shown to cause resistance to targeted and immune therapies in melanoma, we hypothesized that obesity would be associated with worse outcomes in patients with metastatic melanoma treated with these therapies.
31 Jan Steady Increase in Melanoma In Older Adults
MedicalResearch.com Interview with: Dawn Holman, MPH Behavioral Scientist Division of Cancer Prevention and Control CDC MedicalResearch.com: What is the background for this study? Response: Melanoma is the third most common type of skin cancer and the most deadly. Each year in the United States, over 70,000 people are diagnosed with melanoma, and more than 9,000 die from the disease. Melanoma is often caused by overexposure to ultraviolet (UV) rays from the sun or artificial sources like tanning beds. Previous reports have shown a steady increase in melanoma incidence rates over time, specifically among non-Hispanic whites. The purpose of this study was to determine if this trend differs across age groups. [caption id="attachment_39763" align="aligncenter" width="400"]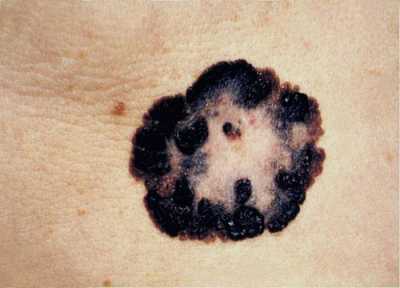 This image depicts the gross appearance of a cutaneous pigmented lesion, which had been diagnosed as superficial spreading malignant melanoma (SSMM). Note the roughened edges of this mole, its heterogeneous, mottled, multicolored appearance, as well as its multi-textural composition, which are all characteristics that should evoke suspicions about its classification.
SSMM makes up 60 – 70% of clinical subtypes of melanoma, can appear at any site on the body, displays a radial growth pattern, and histopathologically, is found to reveal a more pagetoid, i.e., melanocytes spreading upward into epidermal layer, and less elastotic cytoarchitecture. Solar elastosis is characterized by a degeneration of the skin’s elastic and collagen fibers, giving it a sagging, wrinkled appearance.
SSMM:
- diagnosed most frequently between the ages of 30-50 years
- Most common on trunk in men and legs in women
- Brown-black macule that becomes a patch, and eventually takes on the appearance of a nodule
- 1/3rd arise from pre-existing nevus
- Regression common[/caption]
17 Jan Melanoma: New Combination Therapy Targets Resistant Tumors
MedicalResearch.com Interview with: [caption id="attachment_39325" align="alignleft" width="200"] Dr. Peeper[/caption]
Daniel S. Peeper, PhD
Professor of Functional Oncogenomics (VUmc)
Member of Oncode Institute
Head, Division of Molecular Oncology & Immunology
Chair, Scientific Faculty Council
Chair, Translational Research Board
The Netherlands Cancer Institute
Amsterdam The Netherlands
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: BRAF mutant melanomas are now commonly treated with either immunotherapy or with the combination of BRAFi + MEKi. Recent clinical trials showed that combination checkpoint blockade gives 58% 3 year survival for advanced melanoma. For BRAF+MEKi these numbers are somewhat less impressive. Our study relates to the latter setting.
Clearly, most patients treated with this combination do not experience a durable clinical benefit. We showed previously that resistance to these inhibitors is commonly associated with a striking increase in the number of AXL+ cells; this is the rationale for the current study.
14 Dec Familial Members Without Genetic Mutation Can Still Have Increased Risk of Melanoma
MedicalResearch.com Interview with: [caption id="attachment_38934" align="alignleft" width="246"] Dr. Helgadottir[/caption]
Hildur Helgadottir, M.D., Ph.D.
Department of Oncology
Karolinska University Hospital
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Malignant melanoma of the skin is one of the fastest increasing cancer types in the West.
The main risk factors for melanoma are UV light exposure and hereditary factors. It is therefore relatively common for the afflicted to have family members with the disease. Inherited mutations of the tumour suppressor gene CDKN2A are the strongest known risk factors for familial melanoma and mutations in this gene also increase the risk of other cancers. Children, siblings or parents of mutation carriers have a 50-50 chance of also having the mutation, which can be identified with a gene test.
The present study included Swedish and American families with inherited CDKN2A mutations. The researchers studied whether family members who have not inherited the mutation have any higher than normal risk of developing melanoma or other cancers.
Melanoma, but no other cancers, was more common in the non-carriers in these families compared to the normal population. The phenomenon whereby non-carriers of a specific mutation copy the phenotype (in this case melanoma) from their mutation-carrying relatives is known as phenocopy.
Phenocopy can be caused by other risk-modifying genes or exposure patterns that increase the probability of the specific phenotype manifesting itself. Previous studies have shown that people with the mutation who also have certain pigmentation variants run an even higher risk of melanoma.
Even though the CDKN2A mutation should be present in all populations, it has almost exclusively been identified in families with a Caucasian heritage.This suggests that dark-skinned people with this mutation probably don’t develop melanoma as often and are therefore not tested for this specific mutation, presumably because they lack the risk-modifying pigmentation variants that increase the risk of melanoma. The researchers believe that such pigmentation variants also contribute to a higher melanoma risk in the family members who do not carry the mutation.
17 Oct Transplant Network Undercaptures Post-Transplant Skin Cancers
Posted at 19:11h
in Author Interviews, Dermatology, Melanoma, Transplantation, University of Pennsylvania
MedicalResearch.com Interview with:
[caption id="attachment_37504" align="alignleft" width="148"] Dr. Shin[/caption]
Thuzar M.Shin MD, PhD
Assistant Professor of Dermatology
Hospital of the University of Pennsylvania
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The Organ Procurement Transplant Network (OPTN) collects data on cancers that develop after organ transplantation. Previous studies have shown incomplete reporting to the OPTN for many cancers (including melanoma). Skin cancer is the most common malignancy in solid organ transplant recipients and the most common post-transplant skin cancer, cutaneous squamous cell carcinoma (cSCC), is not captured in standard cancer registries. We hypothesized that cSCC and melanoma are underreported to the OPTN. When compared to detailed medical record review obtained from the Transplant Skin Cancer Network database (JAMA Dermatol. 2017 Mar 1;153(3):296-303), we found that the sensitivity of reporting to the OPTN was only 41% for cSCC and 22% for melanoma. The specificity (99% for cSCC and 100% for melanoma) and negative predictive values (93% for cSCC and 99% for melanoma) were high. As a result, the OPTN database is unable to robustly and reliably distinguish between organ transplant recipients with and without these two skin malignancies.
05 Oct Surgical Delays For Melanoma Patients Are Common
MedicalResearch.com Interview with: Adewole Adamson, MD, MPP Department of Dermatology UNC MedicalResearch.com: What is the background for this study? What are the main findings? Response: Surgery is the primary intervention for the treatment of melanoma. Little is known about how delays for surgery, defined as the time between diagnosis and surgical treatment, among melanoma patient differ by insurance type. After adjustment of patient-level, provider-level, and tumor-level factors we found that Medicaid patients experience a 36% increased risk of delays in surgery for melanoma. These delays were 19% less likely in patients diagnosed and 18% less likely in patients surgically treated by dermatologists. Non-white patients also had a 38% increased risk of delays.14 Sep Targeted Immunotherapy Can Prevent Some Melanomas From Spreading
MedicalResearch.com Interview with: [caption id="attachment_36963" align="alignleft" width="116"] Dr. Menzies[/caption]
Dr Alexander Menzies BSc(Med) MBBS (Hons) FRACP PhD
Medical Oncologist and Senior Research Fellow at Melanoma Institute Australia
The University of Sydney and Royal North Shore and Mater Hospital
MedicalResearch.com: What is the background for this study?
Response: For early-stage melanoma, surgical resection is the standard treatment and is associated with an excellent long-term prognosis. However until now, Stage III melanoma patients (where the disease has spread to the lymph nodes) who have had their tumours surgically removed have simply had to play the waiting game to see if their melanoma would metastasise, with many ultimately dying of the disease.
Checkpoint inhibitor immunotherapies and drugs that target the mitogen-activated protein kinase (MAPK) pathway have improved the outcome of patients with metastatic melanoma, but their role as adjuvant therapy is still being actively investigated.
Prior Phase III trials (COMBI-D and COMBI-V) have shown improved overall survival in patients with unresectable or metastatic melanoma with BRAF V600E or V600K mutations. At Melanoma Institute Australia, we were keen to see if this improvement would be seen in the adjuvant setting also. This clinical trial was the first in the world to give targeted therapy to melanoma patients at an earlier stage of the disease to prevent spread and recurrence.
13 Sep Nivolumab Is A Major Advance For Excised Melanoma At Risk of Relapse
MedicalResearch.com Interview with: [caption id="attachment_36922" align="alignleft" width="108"] Dr. Weber[/caption]
Jeffrey Weber, M.D., Ph.D
Laura and Isaac Perlmutter Cancer Center
New York University Langone Medical Center
New York, NY 10016
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: There is a major unmet need for well tolerated and effective adjuvant therapy for high risk melanoma, that is, melanoma that has been removed but the patients have a 50%+ risk of relapse over 5 years, and a 50%+ risk of death over 10 years from melanoma. Since nivolumab is an active and well tolerated drug in metastatic disease, it seemed reasonable to test it after surgery to prevent recurrence. Since ipilimumab is approved for resected stage III melanoma in the US as adjuvant therapy, that was the control arm for comparison, and that is an active control, which prolongs relapse free and overall survival comared to placebo.
08 Sep Study Opens Door To Reducing Melanoma Risk in Redheads
MedicalResearch.com Interview with: [caption id="attachment_36856" align="alignleft" width="120"] Dr. Cui[/caption]
Rutao Cui, MD/PhD
Professor
Vice Chair for Laboratory Administration
Director, Laboratory of Melanoma Biology
Department of Pharmacology and Experimental Therapeutics
Professor of Dermatology
Boston University
Boston, Mass 02118
MedicalResearch.com: What is the background for this study?
Response: Red-headed people are making up to 1~2% of the world’s population. They carry “red hair color” variants of MC1R (MC1R-RHC) which are responsible for their characteristic features, including red hair, pale skin, freckles and poor tanning ability.
MC1R-RHC also increases risk of melanoma, the deadliest form of skin cancer. People without red hair but with a single copy of MC1R-RHC also have an increased melanoma risk, who may make more than 50% of the northern European population. It is unknown why redheads are more prone to melanoma, and whether the activity of red hair color variants could be restored for therapeutic benefits.
06 Sep Study Finds Only 1/3 of Melanomas Arise in Pre-Existing Moles
MedicalResearch.com Interview with: [caption id="attachment_36780" align="alignleft" width="200"]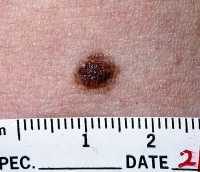 Mole or Nevus
Wikipedia[/caption] Riccardo Pampena MD and Caterina Longo, MD, PhD Dermatology Unit University of Modena and Reggio Emilia Arcispedale Santa Maria Nuova-IRCCS Reggio Emilia Italy MedicalResearch.com: What is the background for this study? What are the main findings? Response: High heterogeneity has been reported in previous studies on the ratio of melanoma associated with moles (nevus-associated melanomas). Despite this heterogeneity, researchers agree that some melanomas may develop in conjunction with a pre-existing mole. We know that nevus-associated melanomas are usually located on the trunk and more frequently occur in younger patients than de novo melanomas (not nevus-associated). Defining the risk for a melanoma to arise in association with a pre-existing mole is important in order to define the best strategies for early melanoma diagnosis. The main finding of our study is that only one third of melanomas arose from a pre-existing mole, in fact the majority were de novo. We also found that nevus-associated melanomas were less aggressive than de novo.
14 Jul Lithium May Reduce Melanoma Risk and Mortality
MedicalResearch.com Interview with: [caption id="attachment_35907" align="alignleft" width="200"] Dr. Asgari[/caption]
Maryam M. Asgari, MD, MPH
Department of Dermatology
Massachusetts General Hospital,
Department of Population Medicine
Harvard Medical School, Boston, Massachusetts
Division of Research, Kaiser Permanente
Northern California, Oakland
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Laboratory studies show lithium, an activator of the Wnt/ß-catenin signaling pathway, slows melanoma progression, but no published epidemiologic studies have explored this association. We conducted a retrospective cohort study of adult white Kaiser Permanente Northern California members (n=2,213,848) from 1997-2012 to examine the association between lithium use and melanoma risk.
Our main finding is that lithium-exposed individuals had a reduced incidence of melanoma, did not develop very thick tumors (> 4 mm Breslow depth) or extensive disease at presentation, and had decreased melanoma-specific mortality compared to unexposed individuals suggesting a possible role for lithium in altering melanoma risk.
22 Jun New Cream May Lead To Non Sun-Induced Tanning
MedicalResearch.com Interview with: [caption id="attachment_35502" align="alignleft" width="200"] Dr. Fisher[/caption]
David E. Fisher MD, PhD
Edward Wigglesworth Professor & Chairman
Dept of Dermatology
Director, Melanoma Program MGH Cancer Center
Director, Cutaneous Biology Research Center
Massachusetts General Hospital
Harvard Medical School
Boston, MA 02114
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: This study grew from an interest to mimic the dark pigmentation patterns in human skin which are known from epidemiology to be associated with low skin cancer risk. In the current work, a molecular inhibitor of the SIK enzyme was used to block the inhibitory action of SIK relative to melanin synthesis. The result was stimulation of dark pigmentation within human skin.
10 May Report of Benign Moles Undergoing Immune Reaction During Nivolumab Therapy in a Patient With Melanoma
MedicalResearch.com Interview with: [caption id="attachment_34514" align="alignleft" width="133"] Dr. Nakamura[/caption]
Yasuhiro Nakamura, M.D., Ph.D.
Associate Professor
Department of Skin Oncology/Dermatology
Comprehensive Cancer Center
Saitama Medical University International Medical Center
Hidaka, Saitama
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Regressing nevi, which are frequently associated with halo phenomenon, occur in approximately 1% of the general population. In patients with melanoma, spontaneous or treatment-related depigmentation of the skin (vitiligo) is sometimes observed. Although humoral and cellular immune responses may play a crucial role in their development, immune reactions to benign melanocytic nevi (BMN) without a halo are extremely rare in both the general population and in patients with melanoma.
This publication reports a rare case with multiple metastatic melanomas who showed a remarkable clinical response to nivolumab with a simultaneous prominent immune reaction to multiple BMN without halo phenomenon. This rare phenomenon may be associated with dramatic efficacy of nivolumab in melanoma patients.
27 Apr Noninvasive Patch Test Can Improve Clinical Diagnosis of Melanoma
MedicalResearch.com Interview with: [caption id="attachment_34201" align="alignleft" width="200"] Dr. Laura K. Ferris[/caption]
Laura Korb Ferris, MD, PhD
Associate Professor, University of Pittsburgh Clinical and Translational Science Institute
Director of Clinical Trials
Department of Dermatology
University of Pittsburgh Medical Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: We found that a non-invasive adhesive patch applied to the skin over a pigmented skin lesion allowed us to capture enough genetic material from the lesion to analyze and predict if that lesion is likely to be melanoma, meaning a biopsy is warranted, or if it is likely benign, meaning the patient would not need a skin biopsy.
In this study, we asked dermatologists to use their clinical judgement to decide if they would recommend biopsying a skin lesion based on photos and information about the lesion and the patients, such as the patient's age, personal and family history of skin cancer, and if the lesion was new or changing. We then provided them the read out of the gene test and asked them how this influence their decision. We found that with this test result, dermatologists were more accurate in their decision making, meaning they were more likely to recommend biopsy of melanomas and less likely to biopsy harmless moles than they were without the test. This is important as it means this test has the potential to reduce the number of unnecessary skin biopsies performed, saving patients from undergoing a procedure and having a scar as a result, without increasing the risk of missing a melanoma.
31 Mar Higher Dose IPI for Some Advanced Melanoma Patients?
MedicalResearch.com Interview with: [caption id="attachment_33563" align="alignleft" width="181"] Dr. Ascierto[/caption]
Dr Paolo A Ascierto MD
Melanoma Cancer Immunotherapy and Innovative Therapy Unit
Istituto Nazionale Tumori Fondazione
Naples Italy
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Although IPI was approved for the treatment of melanoma at dosage of 3 mg/kg, a dose-ranging phase 2 trial suggested longer overall survival (OS) but more treatment-related adverse events with ipilimumab 10 mg/kg vs 3 mg/kg. However, the study MDX010-020 (randomized phase III study which compared ipilimumab 3 mg/kg + gp100 vaccination and ipilimumab 3mg/kg + placebo vs gp100 vaccination + placebo) performed as second line treatment of advanced melanoma patients, showed an OS curve similar to that of the study CA184-169 (randomized phase III study which compared dacarbazine + ipilimumab 10 mg/kg to dacarbazine + placebo) as first line treatment of metastatic melanoma.
For this reason FDA approved ipilimumab at dosage of 3 mg/kg as first and second line treatment for advanced melanoma, but asked for a randomized phase III study of comparison of ipilimumab at the different dosage in order to explore if there was a difference in the outcome of patients with different dosages.
27 Mar Number Of High School Students Who Indoor Tan Dropped In Half
MedicalResearch.com Interview with: Matthew Reynolds Acting Team Lead, Office of Communication Division of Cancer Prevention and Control (DCPC) Centers for Disease Control and Prevention (CDC) Chamblee GA MedicalResearch.com: What is the background for this study? Response: Indoor tanning and sunburns, particularly during adolescence and young adulthood, increases the risk of developing skin cancer. Researchers examined trends in the prevalence of indoor tanning and the relationship between indoor tanning and sunburn among US high school students. Pooled cross-sectional data from the 2009, 2011, 2013, and 2015 national Youth Risk Behavior Surveys. The study included nationally representative samples of U.S. high school students.07 Mar Indoor Tanning By High School Students Drops By Half
MedicalResearch.com Interview with: [caption id="attachment_32722" align="alignleft" width="200"] Dr. Gery Guy[/caption]
Gery P. Guy Jr., PhD, MPH
Senior Health Economist
Division of Unintentional Injury
CDC
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The incidence of skin cancer is increasing in the United States, and individuals who indoor tan are at an increased risk of skin cancer. Treating skin cancer costs $8.1 billion annually.
The number of high school students who indoor tan dropped by half from 2009 to 2015. In 2015, 1.2 million high school students indoor tanned, down from 2.5 million in 2009. This is a much bigger decrease than we have seen in the past and is an encouraging finding. We also found that 82% of indoor tanners reported sunburn in the past year compared with 54% of those who did not engage in indoor tanning.
01 Mar Diabetes Drug Reverses Aging Medium That Promotes Melanoma
MedicalResearch.com Interview with: [caption id="attachment_32560" align="alignleft" width="200"] Dr. Behera[/caption]
Reeti Behera, Ph.D.
Postdoctoral fellow in the Weeraratna lab
The Wistar Institute
Philadelphia PA
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Malignant melanoma is an aggressive disease and is the cause of the majority of skin cancer deaths. In particular, older individuals have a much poorer prognosis for melanoma and are more resistant to targeted therapy than compared to young individuals. A recently published study from our lab has shown that age-related changes in secreted factors in the microenvironment can drive melanoma progression and therapy resistance.
Klotho is a protein whose expression levels decreases with aging. In this study, we have shown that a decrease in klotho levels in the aged microenvironment drives melanoma aggression and therapy resistance by promoting the oncogenic signaling pathway Wnt5A. We also have shown that reconstituting klotho levels in the aged microenvironment by using rosiglitazone, an FDA-approved drug used to treat diabetes, can reduce tumor burden in aged mice. We also show that Klotho expression is decreased in therapy-resistant melanoma tumors. Reconstituting klotho levels in therapy-resistant melanoma cells by treating with rosiglitazone can inhibit Wnt5A levels and MAPK pathway. We also show that rosiglitazone can significantly decrease therapy-resistant tumor burden in the aged mice, but not in the young.
13 Feb Diabetes Drug May Enhance Melanoma Chemotherapy
Posted at 23:05h
in Author Interviews, Brigham & Women's - Harvard, Cancer Research, Dermatology, Diabetes, Melanoma
MedicalResearch.com Interview with:
[caption id="attachment_31978" align="alignleft" width="135"] Dr. Bin Zheng[/caption]
Bin Zheng, PhD
Assistant Professor
Cutaneous Biology Research Center
Massachusetts General Hospital
Harvard Medical School
Charlestown, MA 02129
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Melanoma is the most deadly form of skin cancer with more than 75,000 newly diagnosed cases in the US each year. Over the years, various genetic driver mutations have been identified that cause melanoma, including mutations in the genes BRAF and NRAS. Recent genetic insights into the development of melanoma showed that also mutations in NF1 can lead to melanoma. While there are targeted therapies available for BRAF-mutant melanoma, thus far no such therapies are available for NF1-mutant melanoma. We identified that using a combination of an ERK inhibitor, SCH772984, and the antidiabetic drug phenformin could provide a novel therapeutic strategy for NF1-mutatnt melanomas.
03 Feb New Compounds May Extend Efficiency of Sunscreens
[caption id="attachment_31720" align="alignleft" width="200"] Dr. Diego Sampedro[/caption]
MedicalResearch.com Interview with:
Dr. Diego Sampedro PhD
Department of Chemistry, Centro de Investigación en Síntesis Química (CISQ)
Universidad de La Rioja
Logroño, Spain
MedicalResearch.com: What is the background for this study?
Response: Skin cancer is currently the most common type of cancer. While it implies a relatively low mortality rate, the reported cases of all types of skin cancer have been steadily increasing for the last decades. The ozone layer depletion and longer sunlight exposure times due to outdoors activities contribute to this increase. Solar light is well-known to lead to several skin cellular problems, including DNA damage, mutations, oxidative stress, sunburn and immune suppression. These deleterious effects of sunlight may be mitigated by the use of sunscreens.
Sunscreens are inorganic or organic substances that are directly applied onto the skin, designed to minimize light transmission into the skin, mainly in the ultraviolet region of the solar spectrum. However, serious concerns exist about the safety of several commercial sunscreens components, as well as several drawbacks due to the lack of stability, biodegradability and effectiveness for skin protection. Thus, the development of new (and more efficient) types of sunscreens is of critical importance with a great potential impact in public health and industrial applications.
10 Jan In Global Survey, Risks of Sun Exposure and Tanning Not Well Known
MedicalResearch.com Interview with: [caption id="attachment_31129" align="alignleft" width="200"] Dr. Sophie Seite[/caption]
Sophie Seite, Ph. D
La Roche-Posay Dermatological Laboratories
Asnières, France.
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The survey included nearly 20,000 men and women in 23 countries, ages 16-65, and was primarily conducted online. The questionnaire collected data regarding demographics, sun exposure, behaviors regarding prevention and tanning, risk knowledge, self-examination, medical advice seeking, and social attitude. This unprecedented international survey on sun exposure behaviors and skin cancer detection found that there are many imperfections and geographical inequalities in primary and secondary prevention of skin cancer.
The study was published in the Journal of the European Academy of Dermatology & Venereology by researchers from La Roche-Posay and the George Washington University (GW) Department of Dermatology. Survey results indicate that 88 percent of those questioned were aware of the risks of developing skin cancer when exposed without protection to the sun. However, just 1 in 2 respondents has ever consulted a dermatologist for a mole screening and 4 in 10 people don’t think to protect themselves from the sun outside of vacation.