
Cancer Research
22 May EWG Urges Sunscreen Companies and Consumers To Go Oxybenzone-Free By 2020
MedicalResearch.com Interview with: Carla Burns, M.S.
Environmental Working Group
She is one of the coauthors of the 2018 Guide to Sunscreens.
MedicalResearch.com: What is the background for the EWG report?
Response: Environmental Working Group (EWG) published its first Sunscreen Guide in 2007.
When we first started the guide, many sun protection products sold in the U.S. were not as safe and used misleading marketing claims.
Throughout the years, EWG has continued to find that a common sunscreen ingredient, oxybenzone, poses a hazard to human health and the environment. Despite EWG’s efforts to draw attention to the health hazards associated with this ingredient over the last 12, oxybenzone remains widely used in chemical-based sunscreens. So, this year, we are ramping up our efforts to rid the market of this ingredient by launching a campaign to urge companies and consumers to go oxybenzone-free by 2020.
21 May Multiple Myeloma Cases and Deaths Increase Worldwide
MedicalResearch.com Interview with: [caption id="attachment_41916" align="alignleft" width="125"] Dr. Cowan[/caption]
Andrew J. Cowan, MD
Seattle Cancer Care Alliance
Division of Medical Oncology
University of Washington, Seattle
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Multiple myeloma (MM) is a plasma cell neoplasm with substantial morbidity and mortality. A comprehensive description of the global burden of multiple myeloma is needed to help direct health policy, resource allocation, research, and patient care.
Myeloma cases and deaths increased from 1990 to 2016, with middle-income countries contributing the most to this increase. Treatment availability is very limited in countries with low socioeconomic development.
20 May Pre-Emptive Therapy of CMV in Allogeneic Hematopoietic Cell Transplant
MedicalResearch.com Interview with: [caption id="attachment_41862" align="alignleft" width="125"] Dr. Chemaly[/caption]
Roy F. Chemaly, MD, MPH F.A.C.P., F.I.D.S.A.
Department of Infectious Diseases
Infection Control and Employee Health
Division of Internal Medicine
MD Anderson Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: CytomegalovirusCMV infection is a common cause of morbidity and mortality in allo-HCT recipients. Evidence suggests that CMV infection has not only an enormous clinical burden, but a substantial economic burden as well.
We conducted this study at MD Anderson to determine the economic and clinical burden of preemptive therapy (PET) for CMV infection. Between 2012 and 2015, 100 consecutive patients hospitalized at our institution for allo-HCT who experienced reactivation of CMV and were treated pre-emptively, were enrolled.
The majority of patients were men (55%), who had underlying leukemia (73%), and underwent matched unrelated donor transplant (59%). At the time of hospitalization, most patients had acute GvHD (62%), and were on steroids (58%) within 30 days of CMV reactivation which occurred at a median of 32 days post-HCT (2 -174). A total of 192 episodes of PET occurred in the 100 allo-HCT recipients within 1 year post-HCT. PET consisted of ganciclovir (41%), foscarnet (40%), and valganciclovir (38%). IVIG was also used as adjunct therapy in 20% of episodes.
Progression to Cytomegalovirus disease occurred in 4 patients (4%) and mainly affected the GI tract. Mean length of stay for patients treated with ganciclovir or foscarnet was 32 days (2-141) and 41 days (1-177), respectively. The average direct cost per patient admitted for PET was $126,038 ($7,866-$641,841) and the mean cost of CMV antiviral drug per hospitalization was $6,096 for IVIG, $2,410 for foscarnet, $836 for ganciclovir, and $780 for valganciclovir.
Serious side effects from PET were observed in 35% of patients on ganciclovir and 12% of patients on foscarnet. Total direct cost per encounter was significantly higher in patients who had serious side effects from foscarnet. All-cause mortality was 59% at 1 year post-transplant.
17 May Automated Bone Scan Index Correlates with Survival in Metastatic Prostate Cancer
MedicalResearch.com Interview with: [caption id="attachment_41807" align="alignleft" width="156"] Dr. Armstrong[/caption]
Andrew J. Armstrong, MD ScM FACP
Associate Professor of Medicine, Surgery, Pharmacology and Cancer Biology
Associate Director for Clinical Research in Genitourinary Oncology
Duke Cancer Institute
Divisions of Medical Oncology and Urology
Duke University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Men with prostate cancer commonly develop bone metastases and undergo nuclear medicine bone scans. However, these scans are non-quantitative, and disease burden has been challenging to assess over time and to relate to clinical outcomes.
We developed a software program and measurement called the automated bone scan index that essentially reads a standard of care nuclear bone scan, provides a quantitative metric, and demonstrate in a phase 3 trial that this aBSI is highly associated with clinical outcomes including survival, time to symptomatic progression, and prostate cancer specific survival.
We accomplished this within a prospective phase 3 international trial of men with metastatic hormone resistant prostate cancer who were followed over a long period of time. All bone scans were read and measured using the aBSI at baseline, and we found that the aBSI was highly prognostic. This work validates prior smaller phase 2 BSI studies, and demonstrates both the feasibility and clinical utility for incorporating the aBSI into clinical practice to provide this important prognostic information to patients and providers.
17 May DARZALEX® (daratumumab) Approved for Newly Diagnosed Patients with Multiple Myeloma who are Transplant Ineligible
MedicalResearch.com Interview with: [caption id="attachment_41804" align="alignleft" width="132"] Dr. Jakubowiak[/caption]
Andrzej Jakubowiak, MD, PhD
Professor of Medicine
Director, Myeloma Program
University of Chicago
MedicalResearch.com: What is the background for this announcement? Would you briefly explain what is meant by multiple myeloma?
Response: DARZALEX (daratumumab) in combination with VELCADE (bortezomib), melphalan and prednisone - VMP - received U.S. FDA approval for the treatment of patients with newly diagnosed multiple myeloma who are ineligible for autologous stem cell transplant (ASCT). With this most recent approval, DARZALEX is now the first monoclonal antibody approved for newly diagnosed patients with this disease.
Multiple myeloma is an incurable blood cancer that occurs when malignant plasma cells grow uncontrollably in the bone marrow. Despite the introduction of new medicines over the last decade, which has led to significant improvements in outcomes for patients with multiple myeloma, multiple myeloma remains an incurable disease. In 2018, it is estimated that 30,700 people will be diagnosed and 12,770 will die from the disease in the United States.
17 May SKINDER App Teaches Intuitive Visual Diagnosis of Melanoma
MedicalResearch.com Interview with: [caption id="attachment_41796" align="alignleft" width="200"]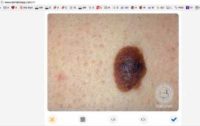 Image from SKINDER APP[/caption]
Michael S. Kolodney, MD, PhD
Section of Dermatology, Department of Medicine
West Virginia University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Melanoma is easily curable if recognized early. Dermatologists are good at spotting melanomas because they develop an innate sense of how melanomas appear after examining thousands of malignant and benign lesions. In contrast, most medical students are relatively disadvantaged by their limited dermatology exposure. We felt that too little experience, rather than lack of knowledge of the rules, is the primary barrier to development of pattern-recognition and intuition as a reliable tool for melanoma diagnosis in non-experts. To remedy this problem, we developed a novel web-based application to mimic the training of a dermatologist by teaching medical students intuitive melanoma diagnosis in a highly condensed period of time.
Our application, which we call Skinder, teaches intuitive visual diagnosis of melanoma by quickly presenting the learner with thousands of benign and malignant skin lesions. The user makes rapid binary decisions, by swiping right for benign or left for malignant, and receives instant feedback on accuracy. With this application, the learner can amass a mental repository of diagnostic experience in a short amount of time. To determine if intuitive visual diagnosis training is superior to a traditional rule-based approach, we compared our web-based application to a rules based approach, the publicly available INFORMED Skin Education Series.
Medical students were tested on the ability top differentiate melanomas from benign pigmented lesions before and after training with either Skinder of the Informed Skin Education Series. The pre-test mean for the Skinder group was 75% correct, compared to 74.7% correct for the INFORMED group. The post-test mean for the skinder application group was 86.3% correct, compared to 77.5% correct for the INFORMED group which was highly signifcant.
16 May Can a Pill Plus Infrared Light Replace Mammograms?
Posted at 20:37h
in Author Interviews, Biomarkers, Breast Cancer, Technology, University of Michigan
MedicalResearch.com Interview with:
[caption id="attachment_41768" align="alignleft" width="200"] Dr. Thurber[/caption]
Greg Thurber, PhD
Assistant Professor
Department of Chemical Engineering
Assistant Professor
Department of Biomedical Engineering
University of Michigan
MedicalResearch.com: What is the background for this study?
Response: Most current disease screening strategies rely on either blood tests, where the physician can obtain information on specific disease molecules but has no idea where they originated in the body, or anatomical imaging, where the physician can see changes in the structure of tissues but doesn’t have any molecular information. We wanted to develop a method that could provide both molecular information and an image of where these molecules were located. We know from decades of research in cancer that this is a molecular disease, so providing molecular information to the physician will help improve detection and diagnosis. Breast cancer screening provides an excellent opportunity to apply this approach to improve detection. Currently, estimates indicate that we are overspending $4 billion per year on the overdiagnosis and overtreatment of breast cancer because we cannot accurately determine which patients need treatment and which can be safely monitored with no intervention. Despite this problem with overdiagnosis, however, screening saves lives…we simply need a better way.
Molecular imaging has the capability of providing both molecular information and the location within the body. However, most of these techniques are expensive and use ionizing radiation, meaning there is a small risk of actually causing cancer. This is not acceptable for screening large numbers of otherwise healthy patients. To avoid this risk and provide a safe, inexpensive, and relatively easy method for patients to undergo screening, we decided to develop near-infrared fluorescent imaging agents that can be taken as a pill. The goal is for the patient to simply take a pill a day or two before their visit, and then the physician shines near-infrared light on the breast tissue to detect tumors where they ‘light up’ by giving off a different color of light.
15 May Checkpoint Inhibitors Rapidly Being Incorporated Into Routine Cancer Care
MedicalResearch.com Interview with: [caption id="attachment_41716" align="alignleft" width="171"] Dr. O'Connor[/caption]
Jeremy O'Connor, MD
Section of General Internal Medicine
Department of Internal Medicine
Postdoctoral Fellow, National Clinician Scholars Program
Yale University
MedicalResearch.com: What is the background for this study?
Response: There has been a lot of enthusiasm for the use of novel therapies in cancer care, and in particular for novel anticancer agents known as immune checkpoint inhibitors. But very little is known about how quickly providers have adopted immune checkpoint inhibitors into clinical practice. Existing studies suggest, in fact, that the process of clinical adoption is slow, with conventional wisdom holding that it takes an average of 17 years for new evidence to change practice.
Our study evaluated whether the adoption of novel therapies might be much faster in certain contexts with the early use of immune checkpoint inhibitors as a notable example.
14 May Men Receive Triple Amount of Cancer Research Funding
MedicalResearch.com Interview with: Dr. Mahiben Maruthappu
Public Health Registrar
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Gender disparities in the fields of science and technology have been documented, and it becomes increasingly apparent at higher levels of seniority. In this analysis, we found a quantifiable difference in cancer research funding awarded to female principle investigators compared to male principle investigators (PIs).
Across all cancer research funding grants that we identified, male PIs received 3.6 times the total investment value, and 1.6 times the average award value compared with their female counterparts.
11 May USPSTF: Men 70 and Older Should Not Be Screened for Prostate Cancer
MedicalResearch.com Interview with: [caption id="attachment_41344" align="alignleft" width="143"] Dr. Krist[/caption]
Alex Krist, M.D., M.P.H
Professor of family medicine and population health
Virginia Commonwealth University and
Active clinician and teacher at the Fairfax Family Practice residency
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Prostate cancer is one of the most common cancers to affect men. However, the decision about whether to be screened is complex and personal. The U.S. Preventive Services Task Force reviewed the latest research on the benefits and harms of screening for prostate cancer using PSA-based testing, as well as evidence on treatment.
We found that men who are 55 to 69 years old should discuss the benefits and harms of screening with their doctor, so they can make the best choice for themselves based on their values and individual circumstances. Men age 70 and older should not be screened, as the benefits of screening diminish as men age and the harms are greater.
05 May Osteoporosis Drug Has Potential To Fight Triple Negative Breast Cancer
MedicalResearch.com Interview with: Chenfang Dong, Ph.D & M.D. Professor Department of Pathology and Pathophysiology Zhejiang University School of Medicine, MedicalResearch.com: What is the background for this study? What are the main findings? Response: Basal-like breast cancer (BLBC), which generally falls into the triple-negative breast cancer subtype, is associated with a poor clinical outcome due to few treatment options and poor therapeutic response; thus there is a pressing need to elucidate the determinants of aggressiveness in BLBC and identify potential therapeutic targets for this challenging disease. By analyzing gene expression profiles of breast cancer in multiple publicly available datasets that contain over 5000 cases, we have identified that UDP-galactose ceramide galactosyltransferase (UGT8), a key enzyme in the sulfatide biosynthetic pathway, promotes BLBC progression by activating sulfatide-αVβ5 axis. Importantly, we identify that zoledronic acid (ZA), a marketed drug for treating osteoporosis and bone metastasis, is a direct inhibitor of UGT8, which has the potential to become a valuable targeted drug for treating Basal-like breast cancer.03 May Liquid Biopsy Can Guide Radiation Therapy in Early Stage Breast Cancer
MedicalResearch.com Interview with: [caption id="attachment_41471" align="alignleft" width="130"] Dr. Goodman[/caption]
Chelain Goodman, MD PhD
PGY-3, Radiation Oncology
Northwestern University
Chicago, IL 60611
MedicalResearch.com: What is the background for this study?
Response: Circulating tumor cells are cancer cells that are shed from the primary tumor into the peripheral blood stream and are hypothesized to be one of the first steps in the initiation of metastatic progression. Prospective studies have demonstrated that approximately 15-25% of patients with early-stage breast cancer can be found to have at least one circulating tumor cell in a small sample of their blood. Currently, all patients with early-stage invasive breast cancer who undergo breast conserving surgery receive adjuvant radiation therapy. In these analyses, we wanted to determine whether presence of circulating tumor cells may be predictive of benefit of radiation therapy following surgery.
03 May What’s the Prognosis If You Get Breast Cancer After a Negative Mammogram?
MedicalResearch.com Interview with: [caption id="attachment_41460" align="alignleft" width="200"] Dr. McCarthy[/caption]
Anne Marie McCarthy, PhD
Department of Medicine
Massachusetts General Hospital and Harvard Medical School
Boston
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Mammography is effective in reducing breast cancer mortality. However, it is not perfect, and approximately 15% of breast cancers are diagnosed despite a negative mammogram before the next recommended screening.
MedicalResearch.com: What should clinicians and patients take away from your report?
Response: Using data from the NCI funded PROSPR (Population-Based Research Optimizing Screening through Personalized Regimens) Consortium, we determined the rates of cancer diagnosis within one year following a negative or positive screening mammogram. The rate of cancer diagnosis within one year of a negative mammogram was small (5.9 per 10,000 screenings), but those cancers were more likely to have poor prognosis than cancers diagnosed after a positive mammogram (43.8% vs. 26.9%). As expected, women with dense breasts were more likely to have cancer diagnosed within 1 year of a negative mammogram. However, breast density was not a good predictor of poor prognosis among women diagnosed with cancer after a negative mammogram. Younger women were more likely to be diagnosed with poor prognosis breast cancer after a negative screening mammogram.
02 May Which Cancers Cost The Most To Treat?
Posted at 22:43h
in Author Interviews, Breast Cancer, Cancer Research, Cost of Health Care, Kaiser Permanente, Lung Cancer, Prostate Cancer
MedicalResearch.com Interview with:
[caption id="attachment_41442" align="alignleft" width="149"] Dr. Banegas[/caption]
Matthew P. Banegas, PhD, MPH
Center for Health Research
Kaiser Permanente
MedicalResearch.com: What is the background for this study?
Response: Despite a large body of research on cancer care costs, we observed a significant evidence gap. Namely, while about one-half of cancer diagnoses in the U.S. occur among people under age 65, it can be difficult to find good data on the costs of care for this population. That’s because most of the current literature on cancer care costs is based on SEER Medicare data, which are limited to Medicare fee-for-service beneficiaries.
At a time of rising costs and an ever-increasing number of new therapies, we felt it was important to improve our understanding of cancer costs for U.S. adults of all ages. We examined medical care costs for the four most common types of cancer in the United States: breast, colorectal, lung, and prostate cancer.
02 May US vs England: Where Do Lung Cancer Patients Live Longer?
MedicalResearch.com Interview with: [caption id="attachment_41398" align="alignleft" width="200"]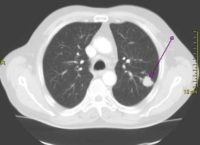 CT scan showing a cancerous tumor in the left lung
Wikipedia image[/caption] Cary P. Gross, MD Department of Internal Medicine Section of General Internal Medicine Cancer Outcomes, Public Policy, and Effectiveness Research (COPPER) Center National Clinician Scholars Program Yale School of Medicine New Haven, CT MedicalResearch.com: What is the background for this study? What are the main findings? Response: In both the US and England, lung cancer is a leading cause of cancer deaths, and there is particular concern about access to high quality care among older persons in both countries. However, little is known about how the two nations compare regarding lung cancer care. We studied over 170,000 patients with lung cancer, and found that patients in the US were more likely to be diagnosed at an early stage (25% in US vs 15% of patients in England). Our international team also found that patients in the US were more likely to receive treatment for their cancer, and were more likely to survive.
18 Apr PAs Do More Biopsies, Find Less Early Melanoma than Dermatologists
Posted at 15:52h
in Author Interviews, Cancer Research, Dermatology, JAMA, Melanoma, Primary Care, University of Pittsburgh
MedicalResearch.com Interview with:
[caption id="attachment_34201" align="alignleft" width="200"] Dr. Laura K. Ferris[/caption]
Laura K. Ferris MD, PhD
Associate Professor, University of Pittsburgh Clinical and Translational Science Institute
Director of Clinical Trials, UPMC Department of Dermatology
University of Pittsburgh
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Dermatology is one of the greatest utilizers of physician extenders, including physician assistants (PAs) in medicine. The scope of practice of PAs has also expanded over time from a role in assisting the dermatologist to taking a more independent role and many PAs now do skin cancer screening examinations and make independent decisions about which lesions are suspicious for skin cancer and need to be biopsied.
Our main findings were that, overall, in comparison to board-certified dermatologists, PAs were more likely to perform biopsies of benign lesions. For every melanoma that they found, PAs biopsied 39 benign lesions whereas dermatologists biopsied 25.
In addition, PAs were less likely than dermatologists to diagnose melanoma in situ, the earliest and most curable, but also hardest to identify and diagnose, form of melanoma. However, PAs had a similar rate of diagnosing the more clinically-obvious forms of skin cancer, including invasive melanoma, basal cell carcinoma, and squamous cell carcinoma.
18 Apr Erectile Dysfunction Drugs May Boost Effects of Chemotherapy
MedicalResearch.com Interview with: [caption id="attachment_41214" align="alignleft" width="143"] Dr Pan Pantziarka[/caption]
Dr Pan Pantziarka, PhD
Program Director, Drug Repurposing: Anticancer Fund
Coordinator: Repurposing Drugs in Oncology
(www.redo-project.org)
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The Repurposing Drugs in Oncology (ReDO) project is an on-going collaboration assessing the evidence of anticancer activity in a wide range of already licensed non-cancer drugs. A subset of these drugs have a sufficient level of evidence to support clinical investigation and these are profiled in detail in order to synthesise the existing evidence and to bring it to the attention of clinical researchers.
In the case of the PDE5 inhibitors sildenafil, tadalafil and vardenafil the evidence is clear that these drugs have multiple anticancer mechanisms of action at clinically relevant dosing. In particular there is evidence that these drugs target anti-tumour immune responses, as shown from a small number of early stage clinical trials. This opens up the prospect of using these cheap and widely available drugs in combination with existing therapies to improve the number and duration of responses. The chance to increase the therapeutic effectiveness of immune checkpoint inhibitors is especially compelling and definitely warrants clinical research.
18 Apr Chemotherapy Choice Can Be Aided By Assessing TDP Profile
MedicalResearch.com Interview with: [caption id="attachment_41267" align="alignleft" width="200"] Dr. Ed Liu[/caption]
Ed Liu, M.D
President and CEO
The Jackson Laboratory (JAX)
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: A few years ago we and others identified a complex genomic instability profile commonly found in the genomes of breast, ovarian and endometrial carcinomas, which is characterized by hundreds of isolated head-to-tail duplications of DNA segments, called tandem duplications. We refer to this configuration as the tandem duplicator phenotype, or TDP.
In this study, we perform a meta-analysis of over 2,700 cancer genomes from over 30 different tumor types and provide a detailed description of six different types of TDP, distinguished by the presence of tandem duplications of different sizes. Collectively, these profiles are found in ~50% of breast, ovarian and endometrial carcinomas as well as 10-30% of adrenocortical, esophageal, stomach and lung adeno-carcinomas. We show that distinct genetic abnormalities associate with the distinct TDPs, clearly suggesting that distinct molecular mechanisms are driving TDP formation. In particular, we provide strong evidence of a casual relationship between joint abrogation of the BRCA1 and TP53 tumor suppressor genes and the emergence of a short-span (~11 Kb) TDP profile. We also observe a significant association between hyper-activation of the CCNE1 pathway and TDP with medium-span (~230 Kb) tandem duplications, and between mutation of the CDK12 gene and medium- and large-span TDP (coexisting 230 Kb and 1.7 Kb tandem duplications).
Importantly, we find that different forms of TDP result in the perturbation of alternative sets of cancer genes, with short-span TDP profiles leading to the loss of tumor suppressor genes via double transections, and larger-span TDP profiles resulting in the duplication (i.e. copy number gain) of oncogenes and gene regulatory elements, such as super-enhancers and disease-associated SNPs.
17 Apr Risk of Cancer Triples Following Blood Clot in Leg
MedicalResearch.com Interview with: Dr. Jens Sundbøll Department of Clinical Epidemiology Aarhus University Hospital Aarhus, Denmark MedicalResearch.com: What is the background for this study? What are the main findings? Response: The incidence of acute peripheral arterial occlusion is approximately 1.5 cases per 10,000 person-years. In comparison, the incidence rate of deep venous thrombosis is about 5-10cases per 10,000 person-years. It has been established previously that deep venous thrombosis in the lower limb and pulmonary embolism may be presenting symptoms of cancer and is associated with a poor cancer prognosis. However, whether arterial thromboembolism of the lower limb also can represent prodromal symptoms of occult cancer and worsen cancer prognosis has never been investigated.17 Apr Blood Pressure Med Linked to Increased Risk of Pancreatic Cancer in Postmenopausal Women
Posted at 12:12h
in AACR, Author Interviews, Baylor College of Medicine Houston, Blood Pressure - Hypertension, Pancreatic
MedicalResearch.com Interview with:
[caption id="attachment_41101" align="alignleft" width="200"] Dr. Wang[/caption]
Zhensheng Wang, M.P.H., Ph.D.
Postdoctoral Associate
Duncan Cancer Center-Bondy
Baylor College of Medicine
Houston, TX
MedicalResearch.com: What is the background for this study?
Response: Our prior research consistently found a significant inverse association between circulating levels of soluble receptor for advanced glycation end products (sRAGE), an anti-inflammatory factor, and risk of pancreatic cancer. It has also been found that sRAGE levels or RAGE signaling are modulated by anti-hypertensive (anti-HT) medications, including angiotensin-converting-enzyme inhibitors (ACEi), β-blockers, and calcium channel blockers (CCBs). These medications have been shown in prior pre-clinical or experimental research to either increase sRAGE concentrations, decrease formation of advanced glycation end-products (AGEs), or dampen pro-inflammatory receptor for AGE (RAGE) signaling pathway. We therefore hypothesized that there would be an inverse association between use of anti-HT medications and risk of developing pancreatic cancer.
Pancreatic cancer is a major public health concern in the United States, as it is the 4th leading cause of cancer-related mortality with an estimated of 43,090 deaths in 2017. Pancreatic cancer typically occurs in elderly individuals who also have chronic comorbid medical conditions, such as hypertension. Anti-HT medication use in individuals ≥ 18 years old has increased from 63.5% in 2001-2002 to 77.3% in 2009-2010, according to the National Health and Nutrition Examination Survey in the U.S. Therefore, it is of great public health significance to address the potential association between anti-HT medication use and risk of pancreatic cancer in the general population.
17 Apr Rhabdomyosarcoma Can Develop From Hijacked Blood Vessel Cells
MedicalResearch.com Interview with: [caption id="attachment_41199" align="alignleft" width="200"] Dr. Hatley[/caption]
Mark E. Hatley, M.D., Ph.D.
Assistant Member
Molecular Oncology Division, Department of Oncology
St. Jude Children's Research Hospital
Memphis, TN 38105
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Rhabdomyosarcoma (RMS) is the most common soft tissue sarcoma occurring in children. Tumors appear histologically and genetically as undifferentiated skeletal muscle and are thus thought to solely originate from early skeletal muscle cells. However, tumors occur throughout the body, including sites devoid of skeletal muscle. In addition, tumor location is a key feature of staging and 40% of patients develop RMS in the head and neck. Interestingly, head and neck muscle development is distinct from the development of trunk and limb muscle. Previously we described a model of rhabdomyosarcoma which occurred specifically in the head and neck and originated from non-muscle cells. In this study we investigated how normal development programs are hijacked to drive rhabdomyosarcoma location.
We demonstrated that RMS can originate from immature blood vessel cells that lie in between muscle fibers specifically in the head and neck. During development, these cells are hijacked, and become reprogrammed into rhabdomyosarcoma rather than mature endothelial cells. These RMS cells express factors important in head and neck muscle development. Our findings highlight that cell of origin contributes to RMS location and may explain why a high proportion of RMS occurs in the head and neck.
16 Apr Public Dissemination of Cancer Study Findings Delayed About 10 Months
MedicalResearch.com Interview with: Lindor Qunaj BSc MD'19 Medical student, Warren Alpert Medical School of Brown University Brown Center for Biomedical Informatics Providence, Rhode Island MedicalResearch.com: What is the background for this study? What are the main findings? Response: Our study was motivated by growing concerns that incomplete or delayed release of clinical trial data may put patients at risk of harm or suboptimal treatment and slow the pace of biomedical innovation. Especially in a field as rapidly evolving as oncology, complete and timely dissemination of clinical trial results is critical to the advancement of both patient care and scientific discovery. In an analysis of press releases from eight large pharmaceutical companies, we found that the median delay from presumed availability of Phase 3 trial data to peer-reviewed publication or public posting of results was 300 days. Studies reporting positive findings were published more rapidly than those with negative results.16 Apr Protein Associated with Metastatic Breast Cancer
MedicalResearch.com Interview with: Yingfei Wang, Ph.D. and Weibo Luo, Ph.D. Department of Pathology UT Southwestern Medical Center Dallas TX 75390 MedicalResearch.com: What is the background for this study? Response: Breast cancer is the most commonly diagnosed cancer in women. Tumor metastasis is frequently found in breast cancer patients and causes more than 90% of cancer death. There is currently no cure for this deadly disease. We have known that breast tumor is not supplied with sufficient oxygen (a phenomenon known as hypoxia), which makes breast cancer cells more aggressive and may be responsible for tumor recurrence, metastasis, and therapy resistance. Hypoxia-inducible factor (HIF) is a master regulator frequently detected in the hypoxic regions and switches on many oncogenes needed for breast cancer cells to grow and spread around the body. The role of HIF in gene regulation is precisely controlled and shutting down of HIF’s activity would be a promising strategy for the treatment of metastatic breast cancer.13 Apr Could Some Iron Supplements Raise Your Risk of Colon Cancer?
MedicalResearch.com Interview with: [caption id="attachment_41173" align="alignleft" width="133"] Dr. Scheers[/caption]
Nathalie Scheers PhD
Asst. Professor
Chalmers University of Technology
Dept of Biology and Biological Engineering
Food and Nutrition Science
Göteborg, Sweden
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Many different forms of iron supplements are used to treat iron deficiency symptoms or as phosphate binders in patients with renal disease. two of these iron supplements, the chelates ferric citrate and ferric EDTA have been observed to drive colon cancer in mice. In the newly published study in Oncotarget, we are reporting our work on how these iron compounds differ compared to the simple salt ferrous sulphate, which is another common iron supplement.
The main finding of this study was that ferric citrate and ferric EDTA promoted the cancer biomarker amphiregulin which in turn activated the MAP kinase ERK in gut epithelial cancer cells. There were no such effects in ferrous sulphate-treated cells.
09 Apr Does Drug Industry Money Affect Cancer Prescriptions?
Posted at 23:13h
in Author Interviews, Cancer Research, Cost of Health Care, JAMA, Pharmaceutical Companies
MedicalResearch.com Interview with:
[caption id="attachment_41105" align="alignleft" width="133"] Dr. Mitchell[/caption]
Aaron Mitchell, MD
Division of Hematology/Oncology, Department of Medicine,
Lineberger Comprehensive Cancer Center
The Cecil G. Sheps Center for Health Services Research
The University of North Carolina at Chapel Hill
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Financial relationships between physicians and the pharmaceutical industry are very common. However, we are just beginning to figure out whether these relationships may lead to potentially concerning changes in physician behavior - whether physicians tend to prescribe more of the drugs made by a company that has given them money. We decided to ask whether oncologists who receive money from drugmakers are more likely to use the cancer drugs made by companies that have given them money in the past.
In studying two specific groups of cancer drugs, one for kidney cancer and one for chronic myeloid leukemia (CML), we found that oncologists who had received payments such as meals, consulting fees, travel & lodging expenses from the manufacturer of one of these drugs tended to use that drug more. When looking at oncologists who received payments for research, we found increased prescribing among the kidney cancer drugs but not the CML drugs.
08 Apr Combination Inhibitors May Attack More Lung Cancers
MedicalResearch.com Interview with: [caption id="attachment_41075" align="alignleft" width="132"] Dr. Kalaany[/caption]
Nada Kalaany, PhD
Harvard Medical School
Boston Children's Hospital
Boston, MA 02115
MedicalResearch.com: What is the background for this study?
Response: Non-small cell lung cancer (NSCLC) is the predominant form of lung cancer and the leading cause of cancer death in the US and worldwide. Over a quarter of NSCLC harbors activating mutations in the KRAS oncogene, which despite decades of attempts, has proven to be very difficult to target.
KRAS has previously been demonstrated to directly bind to and activate the pro-proliferative kinase PI3K, which is typically activated by insulin/insulin-like growth factor1 (IGF1) signaling. KRAS-PI3K binding is required for KRAS-driven lung cancer formation and progression. However, whether this interaction is sufficient for lung tumor formation and whether additional input is required from insulin/IGF1 signaling, has remained largely controversial.
04 Apr Combination EGFR + TNF Inhibition May Knock Out Most Lung Cancers
MedicalResearch.com Interview with: [caption id="attachment_40982" align="alignleft" width="142"] Dr. Amyn Habib[/caption]
Amyn Habib, M.D.
Associate Professor, Neurology & Neurotherapeutics
UT Southwestern Medical Center
MedicalResearch.com: What is the background for this study?
Response: The epidermal growth factor receptor (EGFR) is expressed in most lung cancers and could play an important role in driving the growth of lung cancer. Drugs are available that can block the activity of the EGFR. However, EGFR inhibitors are successful in only a small subset of lung cancers that have a mutant form of the EGFR, and do not work in the majority of lung cancers that have the normal form of the EGFR.
03 Apr Reassessment of Tumor Sequencing For Patients with Potentially Inheritable Colon Cancer
MedicalResearch.com Interview with: [caption id="attachment_40952" align="alignleft" width="200"] Heather Hampel[/caption]
Heather Hampel, MS, LGC
Associate Director, Division of Human Genetics
Associate Director, Biospecimen Research
Professor, Internal Medicine
Licensed Genetic Counselor
The Ohio State University Comprehensive Cancer Center
Columbus, OH 4322
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The background is that we had recently shown that some colorectal cancer patients who underwent traditional screening for Lynch syndrome were eventually found to have double somatic (two acquired) mutations in the MMR genes and they did not have Lynch syndrome at all. This was discovered after their tumor had already had MSI and/or IHC screening test, followed by MLH1 methylation and/or BRAF testing, followed by germline DNA testing on a blood sample from the patient for MMR gene mutations, then finally by sequencing their tumor. This gave us the idea to reverse the sequence and start with tumor sequencing since it might streamline testing, save time, and prevent several other tests.
In addition, we knew that all stage IV colorectal cancer are already supposed to have tumor sequencing of the KRAS, NRAS, and BRAF genes and MSI testing for treatment purposes. Our hypothesis was that an upfront tumor sequencing test could replace all these separate tests with similar sensitivity and specificity.
29 Mar Most Baby Boomers Still Aren’t Screened For Hepatitis C
MedicalResearch.com Interview with: [caption id="attachment_39686" align="alignleft" width="165"]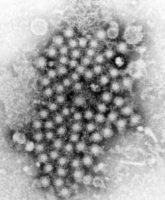 Hepatitis Virions
CDC/ E.H. Cook, Jr.[/caption] Dr. Monica Kasting PhD first author Dr. Anna Giuliano PhD Susan. T. Vadaparampil, Ph.D., M.P.H. Senior Member/Professor Center for Infection Research in Cancer H. Lee Moffitt Cancer Center, Tampa, Florida.Department of Cancer Epidemiology, H. Lee Moffitt Cancer Center, Tampa, Florida MedicalResearch.com: What is the background for this study? What are the main findings? Response: In the U.S., approximately 1 in 30 baby boomers are chronically infected with hepatitis C virus. Half of all cases of liver cancer are caused by hepatitis C and liver cancer is one of only three cancer types that are actually increasing in incidence in the US. Because of this, in 2012 the CDC issued a recommendation for universal screening for hepatitis C virus for everyone born between 1945 and 1965 (baby boomers). We wanted to look at the time period after that to see if the rates of screening in that population increased. From 2013-2015 screening among baby boomers only increased by 0.9% (from 11.8% to 12.7%) which indicates we still have a long way to go before we meet our goal of universal screening.