
OBGYNE
12 Jun Unique Vaginal Cells Facilitate HIV Infection and Persistence
MedicalResearch.com Interview with: [caption id="attachment_42314" align="alignleft" width="114"] Dr. Sagar[/caption]
Manish Sagar, MD
Infectious Disease Physician at Boston Medical Center
Boston MA
MedicalResearch.com: What is the background for this study?
Response: Women compromise the majority of new infections in the world and most of them acquire the virus after sexual exposure. The goal of the study was to understand how HIV establishes initial infection in the female genital tract. We obtained discarded vaginal tissue and isolated cells present in the outermost layer that contact the virus during exposure.
11 Jun Children of Older Mothers More Susceptible to Heart Disease
MedicalResearch.com Interview with: [caption id="attachment_42306" align="alignleft" width="159"] Dr. Davidge[/caption]
Sandra T. Davidge, PhD, FCAHS
Executive Director, Women and Children's Health Research Institute
Canada Research Chair in Maternal and Perinatal Cardiovascular Health
Professor, Depts. of Ob/Gyn and Physiology
University of Alberta
Edmonton, Alberta
Canada
MedicalResearch.com: What is the background for this study?
Response: This research contributes to the growing body of literature that developmental programming of adult onset cardiovascular disease originates in the womb.
Our study is among the first to discover that maternal age may be considered a ‘prenatal stress’ in certain circumstances.
08 Jun Hypertension Disorders in Pregnancy Associated With Increase in ASD and ADHD in Offspring
Posted at 00:59h
in Author Interviews, Autism, Blood Pressure - Hypertension, JAMA, OBGYNE, Pediatrics
MedicalResearch.com Interview with:
 Ali Khashan, PhD
Senior Lecturer in Epidemiology
School of Public Health & INFANT Centre
University College Cork
Cork, Ireland
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: There is some evidence to suggest an increased likelihood of neurodevelopmental disorders in relation to hypertensive disorders in pregnancy, however consensus is lacking. Considering hypertensive disorders in pregnancy are among the most common prenatal complication, we decided to synthesise the published literature on this topic by conducting a comprehensive systematic review and meta-analysis.
Our main findings suggest that hypertensive disorders in pregnancy are associated with about 30% increase in the likelihood of autism spectrum disorders (ASD) and ADHD in the offspring, compared to offspring not exposed to hypertensive disorders in pregnancy.
29 May ADHD More Common if Grandmother Used DES During Pregnancy
MedicalResearch.com Interview with: [caption id="attachment_41811" align="alignleft" width="165"] Dr. Kioumourtzoglou[/caption]
Marianthi-Anna Kioumourtzoglou ScD
Assistant Professor
Environmental Health Sciences
Mailman School of Public Health
Columbia University
MedicalResearch.com: What is the background for this study?
Response: The prevalence of neurodevelopmental disorders, like attention deficit/hyperactivity disorder (ADHD) has been increasing. One of the hypothesized risk factors for increased risk for neurodevelopmental disorders is a class of chemicals known as endocrine disrupting chemicals (EDCs). These chemicals are known to interfere with the endocrine system, i.e. the system that uses hormones to control and coordinate metabolism, reproduction and development. Several high production volume chemicals, ubiquitously present in commercial products, are known or suspected endocrine disruptors. Because of their widespread use in consumer products, the population-wide exposure to known and suspected EDCs is very high.
Recently, there has been increased attention in the potential effects of EDCs on neurodevelopment that span multiple generations. Animal studies have provided evidence that exposure to EDCs, such as phthalates and bisphenol A (BPA), alter the behavior and social interactions in mice in three to five generations after exposure. However, evidence of such multi-generational impacts of EDC exposure on neurodevelopment in humans is unavailable, likely because of the lack of detailed information on exposures and outcomes across generations.
For this study we leveraged information from a nationwide cohort, the Nurses’ Health Study II (NHSII), to investigate the potential link between exposure to diethylstilbestrol (DES) and third generation ADHD, i.e. ADHD among the grandchildren of the women who used DES while pregnant. DES is a very potent endocrine disruptor that was prescribed between 1938 and 1971 to pregnant women thought to prevent pregnancy complications. In the United States, between 5 and 10 million women are estimated to have used DES, although the exact number is not known. DES was banned in 1971, when was linked to vaginal adenocarcinomas (a rare cancer of the reproductive system) in the daughters of the women who had used it during pregnancy. Since then, DES has been also linked to multiple other reproductive outcomes in DES daughters, as well as with some reproductive outcomes in the grandchildren of the women who used it, such as hypospadias and delated menstrual regularization. However, to our knowledge, no study to date has evaluated the association between DES, or any other EDC, and multigenerational neurodevelopment.
23 May No Link Found Between Autism and Maternal Fish Ingested During Pregnancy
MedicalResearch.com Interview with: Dr Caroline M Taylor
Wellcome Trust Research Fellow
Centre for Child and Adolescent Health
Bristol Medical School, University of Bristol
Oakfield House, Oakfield Grove, Bristol
MedicalResearch.com: What is the background for this study?
Response: Mercury is a toxic metal that is widespread in the environment. In pregnancy, mercury in the mother’ bloodstream is transferred through the placenta to the fetus, where is can affect development of the nervous system. Mercury from vaccines has been the focus of attention particularly in regard to a link with autism in children. However, the amount of mercury used in the vaccines is small in comparison with mercury from the diet and atmospheric pollution, and in the EU at least, childhood vaccines no longer contain this preservative. The fear that mercury is linked to autism has persisted, despite increasing evidence that this is not the case.
The aim of our study was to look at mercury from the diet rather than vaccines – specifically from fish – in pregnant women. We measured the women’s mercury levels in their blood and asked them about how much fish they ate. We then followed up their children for 9 years and recorded how many of them had autism diagnosed within that time. We also measured how many of them had autist traits by measuring their social and communication difficulties. The data were part of the Children of the 90s study (Avon Longitudinal Study of Parents and Children – ALSPAC), which is based in Bristol, UK.
16 May Does Acupuncture Increase Live Births For Women Undergoing IVF?
MedicalResearch.com Interview with: Caroline Smith, PhD
Professor Clinical Research
Western Sydney University Research Theme Champion Health and Wellbeing
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Despite technological improvements to IVF the success of IVF treatment remains low. Consequently, new drugs, laboratory techniques and other treatments need to be developed and rigorously tested to explore their effects on producing healthy babies for women undergoing IVF. In 2002, the first randomised controlled trial of acupuncture administered a specific form of IVF acupuncture at the time of embryo transfer.
The results indicated the chance of achieving a pregnancy from acupuncture was twice that to women undergoing IVF treatment alone. From mid 2000s many women have started to use adjunctive treatments such as acupuncture whilst undergoing IVF. We conducted and reported on a pilot study in 2006 which produced results suggesting a benefit. It is important that these findings were rigorously examined in a larger trial.
Findings are presented from our trial presented in JAMA. Our study of over 800 Australian and New Zealand women undergoing acupuncture treatment during their IVF (in vitro fertilization) cycle has failed to confirm significant difference in live birth rates.
16 May Changes in Gestational Age and Perinatal Mortality in US
MedicalResearch.com Interview with: [caption id="attachment_41636" align="alignleft" width="165"] Dr. Ananth[/caption]
Dr. Cande V. Ananth, PhD, MPH
Adjunct professor
Department of Health Policy and Management
Mailman School of Public Health
Columbia University, NY
MedicalResearch.com: What is the background for this study?
Response: Preterm delivery rates have declined between 2005 and 2014 in the US and in several European countries. Since reductions in preterm and early term deliveries, and perinatal mortality remain a global health priority, determining the relationship between gestational age distribution and perinatal mortality, remains a challenge. Efforts expended to a more complete understanding of the impact of new interventions, policies, and practices on reducing the burden of early deliveries, and in turn improvements in perinatal survival will be of tremendous benefit for clinical management and care of women during their pregnancy and the newborn.
07 May Is It Safe to Have a Vaginal Birth after Cesarean Section?
MedicalResearch.com Interview with: Dr. Carmen Young
Department of Obstetrics and Gynecology
University of Alberta
MedicalResearch.com: What is the background for this study?
Response: For women who have had a single previous cesarean section, the optimal mode of delivery in a subsequent pregnancy is controversial. This is because there are risks and benefits to attempting a vaginal birth after cesarean section (VBAC) or having an elective repeat cesarean section. Attempted VBAC is associated with a higher risk of uterine rupture and other maternal and infant complications. Repeat cesarean sections are associated with an increased risk of surgical complications and placental complications in subsequent pregnancies. Furthermore, it is difficult to predict which patients will have a successful VBAC.
This study is unique in that it uses recent Canadian data, allowing assessment of the impact of contemporary obstetrical care on maternal and neonatal outcomes in Canada.
02 May Diet Soda and Excess Sugar During Pregnancy May Depress Child’s Cognition
MedicalResearch.com Interview with: Juliana F. W. Cohen, ScM, ScD
Department of Health Sciences
Merrimack College
North Andover MA 01845.
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Sugar consumption among Americans is above recommended limits and this excess intake may have important health implications.
This study examined the associations of pregnancy and offspring sugar consumption, as well as sugar-sweetened beverages, other beverages (diet soda, juice), and fruit consumption with child cognition.
This study found that when pregnant women or their children consumed greater quantities of sugar, as well as when women consumed diet soda during pregnancy, this was associated with poorer childhood cognition. However, children’s fruit consumption was associated with higher cognitive scores.
12 Apr Women With PCOS Should Be Screened for Mental Health Issues
MedicalResearch.com Interview with: Aled Rees, MD, PhD Neuroscience and Mental Health Research Institute Cardiff University School of Medicine, Health Park Cardiff United Kingdom MedicalResearch.com: What is the background for this study? Response: PCOS is a common condition, affecting 5-10% of women globally, in which elevated male hormone levels can cause a range of distressing and life-limiting symptoms, including reduced fertility, irregular periods, excessive facial and body hair, and acne. Previous studies have suggested a link between PCOS and poor mental health in women but the studies were small and did not adequately take other factors that can affect mental health into consideration. In addition, high levels of testosterone during pregnancy have been reported to increase the risk of neurodevelopmental disorders, such as ADHD and autism, in children.11 Apr Prenatal Exposure to SSRIs May Be Linked to Changes in Infant Brain Development
MedicalResearch.com Interview with: [caption id="attachment_41081" align="alignleft" width="133"] Dr. Jiook Cha[/caption]
Jiook Cha, PhD
Assistant Professor
Division of Child and Adolescent Psychiatry
Columbia University Medical Center
New York, NY 10032
MedicalResearch.com: What did we already know about the connection between maternal SSRI use during pregnancy and infant brain development, and how do the current study findings add to our understanding? What’s new/surprising here and why does it matter for mothers and babies?
Response: Prior studies have shown mixed results in terms of the associations between maternal SRI use during pregnancy and offspring’s brain and cognitive development. Neurobiological studies with animal models suggest that SSRI use perturbs serotonin signaling and that this has important effects on cognitive development (a study conducted an author of this paper, Jay Gingrich, MD, PhD: Ansorge et al., 2004, Science). The human literature has been more mixed in terms of the associations of prenatal exposure to SSRI with brain and cognitive development.
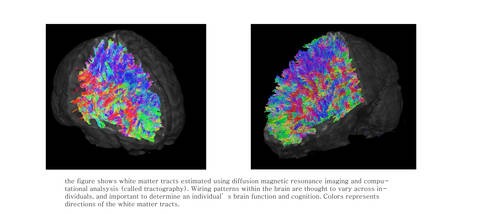
In our study, we used neonatal brain imaging because this is a direct, non-invasive method to test associations between SSRI use and brain development at an early developmental stage, limiting the effects of the post-natal environment. In our study, we had two different control groups, that is, a non-depressed SSRI-free group (healthy controls), and depressed but SSRI-free (SSRI controls) group. Also, in our study we used rigorous imaging analytics that significantly improve the quantitative nature of MR-derived signals from the brain structure using two of the nation’s fastest supercomputers (Argonne National Laboratory and Texas Advanced Computing Center) and allows robust reconstruction of brain’s grey and white matter structure in the infants’ brains.
We report a significant association of prenatal exposure to SSRI with a volume increases within many brain areas, including the amygdala and insula cortex, and an increase in white matter connection strength between the amygdala and insular cortex. We were surprised by the magnitude of the effects (or the statistical effect size), compared with other brain imaging studies in psychiatry with children or adults’ brains. Importantly, it should be noted that our estimates of brain structure are still experimental and for research-purpose only. This means that our data need to be replicated and rigorously tested against confounders in order to make a firm conclusion. While our study suggests a “potential” association between prenatal exposure to SSRI and a change in fetal or infant brain development, we still need more research.
09 Apr Prenatal SSRI Exposure Linked to Altered Infant Brain Development
MedicalResearch.com Interview with: [caption id="attachment_41072" align="alignleft" width="200"] Dr. Lugo-Candelas[/caption]
Claudia I. Lugo-Candelas, PhD
Postdoctoral Research Fellow
Columbia University Medical Center/ New York State Psychiatric Institute
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: We have seen, in the last decade, an increase in the amount of mothers being prescribed SSRIs during pregnancy. While we know that untreated prenatal maternal depression has adverse consequences for both the mother and child, it’s not really clear what, if any, are the consequences of prenatal SSRI exposure on infant’s brain development. There have been some studies finding increased depression and anxiety in children prenatally exposed to SSRIs, but not all studies find these associations.
We thus looked at 2-4 week old infants’ brains, using neuroimaging. We found increased gray matter volume within the amygdala and insula, and increased white matter connectivity between these two structures in infants prenatally exposed to SSRIs. Of note, the statistical significance and the size of the effects we detected are quite large, even greater than the brain changes that we usually observe in our studies of children and adults with psychiatric disorders. Further, because these structures are involved in emotion processing, and alterations in volume and connectivity are sometimes seen in clinical populations, or in people at risk for anxiety, it important to learn more about what these volume and connectivity differences could mean for these infants.
22 Mar Two Genes Linked to Severe Nausea and Vomiting in Pregnancy
MedicalResearch.com Interview with: [caption id="attachment_40709" align="alignleft" width="92"] Dr. Fejzo[/caption]
Marlena Fejzo, PhD
Aassociate researche
David Geffen School of Medicine
UCLA.
MedicalResearch.com: What is the background for this study?
Response: Most women experience some nausea and vomiting of pregnancy, and the worst 2% are diagnosed with Hyperemesis Gravidarum which is associated with poor maternal and fetal outcomes. I had HG in 2 pregnancies. In my second pregnancy my HG was so severe that I could not move without vomiting and did not keep any food or water down for 10 weeks. I was put on a feeding tube, but ultimately lost the baby in the second trimester. I am a medical scientist by training so I looked into what was known about HG. At the time, very little was known, so I decided to study it. I partnered with the Hyperemesis Education and Research Foundation (HER) and we did a survey on family history of .Hyperemesis Gravidarum that provided evidence to support a role for genes. I collected saliva samples from HG patients and their unaffected acquaintances to do a DNA study. Then I partnered with the personal genetics company, 23andMe to do a genome scan and validation study, which identified 2 genes, GDF15 and IGFBP7, linked to HG.
20 Mar Estrogen Improved Disordered Eating Patterns in Young Women With Irregular Menses
Posted at 14:56h
in Author Interviews, Brigham & Women's - Harvard, Endocrinology, OBGYNE, Weight Research
MedicalResearch.com Interview with:
[caption id="attachment_40663" align="alignleft" width="200"] Dr.Madhusmita Misra[/caption]
Madhusmita Misra, MD, MPH
Division Chief, Pediatric Endocrinology
Fritz Bradley Talbot and Nathan Bill Talbot Professor of Pediatrics,
Harvard Medical School
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Disordered eating behavior is common in conditions of functional hypothalamic amenorrhea, such as anorexia nervosa and exercise-induced amenorrhea, which are also associated with anxiety and depression. In hypoestrogenic rodents, estrogen replacement reduces anxiety-related behavior. Similarly, physiologic estrogen replacement in adolescents with anorexia nervosa reduces anxiety and prevents the increased body dissatisfaction observed with increasing weight. However, the impact of estrogen administration on disordered eating behavior and psychopathology in normal-weight young women with exercise-induced amenorrhea is unknown.
Adolescent and young adult normal-weight athletes 14-25 years old with irregular periods were randomized to receive (i) physiologic estrogen replacement using a transdermal patch with cyclic progesterone, or (ii) an oral estrogen-progesterone containing pill (an oral contraceptive pill), or (iii) no estrogen for 12-months. The Eating Disorder Inventory-2 (EDI-2) and Three-Factor Eating Questionnaire (TFEQ) were administered ag the beginning and the end of the study to assess disordered eating behavior and psychopathology.
We found that the group that did not receive estrogen had a worsening of disordered eating behavior and psychopathology over the 12-months duration of the study, but this was not observed in the group that received estrogen replacement. Further, body dissatisfaction scores improved over 12-months in the groups receiving estrogen replacement, with the transdermal estrogen group showing the strongest effect.
20 Mar Topical Estrogen No Better Than Moisturizer for Postmenopausal Vaginal Dryness
Posted at 00:05h
in Author Interviews, Brigham & Women's - Harvard, JAMA, Menopause, OBGYNE, Sexual Health
MedicalResearch.com Interview with:
[caption id="attachment_40595" align="alignleft" width="200"] Dr. Caroline Mitchell[/caption]
Caroline Mitchell, MD, MPH
Vincent Center for Reproductive Biology
Assistant Professor, Obstetrics, Gynecology & Reproductive Biology
http://massgeneral.link/MitchellLab
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: In this study we compared two commonly recommended treatments for menopausal vaginal discomfort - low dose vaginal estradiol tablets and a vaginal moisturizer - to placebo, and found no difference in reduction of symptom severity; all three groups improved over 12 weeks of treatment. This is great news for women, as it means that using any treatment regularly is likely to have benefit, whether it costs $20 or $200.
Symptoms of vaginal dryness, irritation and pain with sex, which occur in over half of postmenopausal women, cause a significant decrease in quality of life and negatively impact intimate relationships. The significant impact of these symptoms is reflected in the fact that we enrolled all 302 participants in under a year, a faster enrollment than any of the four prior trials conducted by the MsFlash research network that evaluated treatments for hot flashes. Women were desperate for some kind of intervention for these symptoms.
02 Mar Can Probiotics and Fish Oil Supplements During Pregnancy Reduce Childhood Allergies?
Posted at 20:41h
in Allergies, Author Interviews, Fish, Imperial College, Nutrition, OBGYNE, Omega-3 Fatty Acids, Probiotics
MedicalResearch.com Interview with:
Dr Robert Boyle, Reader in Paediatric Allergy
Department of Medicine
Imperial College London
MedicalResearch.com: What is the background for this study?
Response: Diet in early life may influence whether or not an infant develops allergies or autoimmune disease. We undertook a project for the UK Food Standards Agency to evaluate the evidence for this.
MedicalResearch.com: What are the main findings?
Response: We found that a probiotic supplement during the last 2-4 weeks of pregnancy and during breastfeeding may reduce an infant’s chances of developing eczema; and that omega-3 fatty acid supplements taken from the middle of pregnancy (20 weeks gestation) through the first few months of breastfeeding may reduce an infant’s chances of developing food allergy. We also found links between longer duration of breastfeeding and improved infant health, but for most other variations in diet during pregnancy or infancy we did not find evidence for a link with allergies or autoimmune disease.
12 Feb Pregnancy in Type 1 Diabetes: Glucose Control Can Reduce Fetal Overgrowth
MedicalResearch.com Interview with: [caption id="attachment_39976" align="alignleft" width="200"] Dr. Rachel McGrath[/caption]
Rachel McGrath BSc (Hons), PhD
Senior Research Fellow - Department of Endocrinology, RNSH
Clinical Senior Lecturer - Northern Clinical School
University of Sydney
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Women with type 1 diabetes are significantly more likely to experience complications during pregnancy and to have infants with high birth weights. This can result in adverse outcomes at the time of delivery for both mother and baby, and can also predispose infants to obesity and chronic disease in later life.
The relationship between maternal blood glucose levels and foetal growth in type 1 diabetes in pregnancy has not been completely elucidated. Thus, we examined the association between maternal glycaemic control and foetal growth by examining serial ultrasound measurements and also by determining the relationship between HbA1c (a measure of circulating glucose exposure over a three month time period) and infant birth weight.
We found that maternal glucose levels were directly related to foetal abdominal circumference in the late second and third trimesters and also to birth weight. We also confirmed the results of previous studies to show that the optimal HbA1c during pregnancy to reduce the likelihood of large-for-gestational-age neonates is < 6%.
08 Feb Relationship Status Helps Determine Contraception Choice
MedicalResearch.com Interview with: Marie Harvey, DrPH MPH
Lisa P. Oakley, PhD MPH
College of Public Health and Human Sciences
Oregon State University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Because decisions about contraceptives are often made by young adults in the context of their relationships and specific partners, the characteristics of that relationship and feelings about that partner will likely influence how those decisions are made. Many studies have previously investigated individual factors that affect contraceptive choice and when examining partner influences have used questions that were not specific to a particular partner. Intuition, however, suggests that feelings for a specific partner would likely influence one’s perception of risk for disease acquisition, and thereby, their contraceptive choice. So, it was important to us to look at the influences of each specific partner and how the unique dynamics of each partnership influence contraceptive use.
In this study, we investigated how relationship qualities and dynamics (such as commitment and sexual decision-making) impact contraceptive choice above and beyond individual factors. We also used partner-specific questions.
We found that both individual and partner-specific relationship qualities and dynamics predicted contraceptive use, but these factors varied by contraceptive method. For example, young adults who reported greater exclusivity with a specific partner and more relationship commitment were less likely to use only condoms with that partner. Additionally, individuals who felt they played a strong role in making sexual decisions in their relationship were also more likely to only use condoms.
08 Feb How Much Genetic Information From Prenatal Testing Do Pregnant Women Want?
 MedicalResearch.com Interview with:
Professor Jane Halliday, PhD
Group Leader, Public Health Genetics
Genetics
Murdoch Childrens Research Institute
The Royal Children’s Hospital
Parkville, Victoria AUS
MedicalResearch.com: What is the background for this study?
Response: The aim of the study was to examine the choice that pregnant women make about the amount of genetic information they want from their pregnancy. Women who underwent prenatal testing via chorionic villus sampling (CVS) or amniocentesis were recruited from across seven sites in Victoria.
Provision of this choice is not routinely offered but we thought it was important to look at this issue carefully, in a real-time setting, because, over the last five years, advances in technology have transformed how genetic abnormalities can be detected during a pregnancy. Rather than examining genetic material (chromosomes) down the microscope, it is now possible to use a technique called ‘microarray’ which can do the analysis with 100 times greater depth than can be achieved using a microscope. The plus side is that the microarray technique can detect a far greater number of potentially important genetic differences; but a down side is that it can also detect many changes for which the impact on the health of the baby is unknown or uncertain.
Examples of genetic differences that carry certainty are major chromosome abnormalities such as the trisomies e.g. Down Syndrome, and deletions associated with severe intellectual disability in 100% of cases, e.g. 1p.36 deletion. Uncertain findings are the various small deletions and duplications that are known to only have an adverse outcome in 10-20% of people with them.
All participants were provided with a decision aid which described in detail the choice available in regards to the genetic information. The options were ‘targeted’, where only the information that would affect health of the baby was provided, or ‘extended’, where all information, even the uncertain aspects, was provided. Participants were asked to read the decision aid, complete a ten minute survey along with indicating their choice of genetic information.
29 Jan Teenage Daughters More Likely To Have Abortion If Their Mother Had One
MedicalResearch.com Interview with: Ning Liu PhD Student
Senior Research Analyst at ICES
Institute of Health Policy, Management and Evaluation
Institute for Clinical Evaluative Sciences
University of Toronto
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Previous studies suggested intergenerational tendencies between a mother and her daughter in fertility patterns, such as when they give birth to a child for the first time, or the total number of children they have during their lifetime.
We explored whether there is also an intergenerational tendency for induced abortion practices between a mother and her teen daughter.
To do so, we used anonymized records of 431,623 daughters and their mothers, and found that a teenage daughter was twice as likely to have an induced abortion if her mother had had an induced abortion.
24 Jan Study Evaluates Effects of Probiotics During Pregnancy
MedicalResearch.com Interview with: Mahsa Nordqvist MD
Department of Obstetrics and Gynecology
Sahlgrenska University Hospital
Gothenburg, Sweden
MedicalResearch.com: What is the background for this study?
Response: We have shown in earlier observational studies that there is an association between probiotic intake and lower risk of preterm delivery and preeclampsia. Since pregnancy is a time of rapid change and different exposures can have different effect depending on the time of exposure, we wanted to find out if there is any special time point of consumption that might be of greater importance when it comes to these associations.
24 Jan PCOS: Hyperandrogenism Associated With Changes in Gut Microbiome
MedicalResearch.com Interview with: [caption id="attachment_39566" align="alignleft" width="133"] Dr. Thackray[/caption]
Varykina Thackray, Ph.D.
Associate Professor of Reproductive Medicine
University of California, San Diego
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Previous studies have shown that changes in the composition of intestinal microbes (gut microbiome) are associated with metabolic diseases. Since many women with polycystic ovary syndrome (PCOS) have metabolic dysregulation that increases the risk of developing type 2 diabetes and cardiovascular disease, we wondered whether PCOS was associated with changes in the gut microbiome and if these changes were linked to any clinical features of PCOS.
We collaborated with Beata Banaszewska and her colleagues at the Poznan University of Medical Sciences in Poznan, Poland to obtain clinical data and fecal samples from 163 premenopausal women recruited for the study. In collaboration with Scott Kelley at San Diego State University, we used 16S ribosomal RNA gene sequencing and bioinformatics analyses to show that the diversity of the gut microbiome was reduced in Polish women with PCOS compared to healthy women and women with polycystic ovaries but no other symptoms of PCOS.
The study confirmed findings reported in two other recent studies with smaller cohorts of Caucasian and Han Chinese women. Since many factors could affect the gut microbiome in women with PCOS, regression analysis was used to identify clinical hallmarks that correlated with changes in the gut microbiome. In contrast to body mass index or insulin resistance, hyperandrogenism was associated with changes in the gut microbiome in this cohort of women, suggesting that elevated testosterone may be an important factor in shaping the gut microbiome in women.
20 Jan Medicaid Expansion Linked To Decreased Infant Mortality, Especially Among African Americans
MedicalResearch.com Interview with: [caption id="attachment_39409" align="alignleft" width="200"] Dr. Bhatt[/caption]
Chintan Bhatt MBBS, MPH (HE/HIM/HIS)
Department of Health Promotion & Disease Prevention,
Robert Stempel College of Public Health and Social Work,
Florida International University
Miami Fl
MedicalResearch.com: What is the background for this study?
Response: Women and children are disproportionately affected by the uncertainty around medical health insurance rising in the United States. The Patient Protection and Affordable Care Act was implemented on Jan 1st, 2014, since then the uninsured rate decreased considerably, especially in women aged 18 to 64 years. ACA revised and expanded Medicaid eligibility. Under the law, all U.S. citizens and legal residents with income up to 133% of the poverty line, including adults without dependent children, would qualify for coverage in any state that participated in the Medicaid program. Because of the large proportion of maternal, infant, and child health care and preventive services funded by Medicaid. The purpose of our study was to examine the potential effect of Medicaid expansion on infant mortality rates by comparing infant mortality rate trends in states and Washington D.C. by Medicaid expansion acceptance or decline.
20 Jan Doxylamine-Pyridoxine May Not Be Effective For Nausea and Vomiting of Pregnancy
MedicalResearch.com Interview with: [caption id="attachment_39405" align="alignleft" width="200"] Dr. Persaud[/caption]
Navindra Persaud MD, MSc, BA, BSc
Department of Family and Community Medicine and
Li Ka Shing Knowledge Institute
St Michael’s Hospital
Toronto, Ontario, Canada
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: I used to prescribe doxylamine-pyridoxine for nausea and vomiting during pregnancy. I was taught to prescribe it. The medication was recommended as the first line medication for nausea and vomiting during pregnancy. When I looked carefully at the clinical practice guidelines that recommended this medication, they did not cite supporting studies. So I tried to find the basis for the recommendations. It was surprisingly difficult to obtain information about this commonly prescribed drug.
The medication seems to be ineffective based on the results of this trial.
I was also surprised that important information about the trial was hidden until now. Although some results were published in 2010, the earlier reports did not mention the fact that a difference of 3 points on the 13-point symptom scale was prespecified as the minimal important difference (or the smallest difference that a patient would deem as important).
16 Jan Benefits of Gastric Bypass in Diabetes Control Significant But Diminish Over Time
MedicalResearch.com Interview with: [caption id="attachment_39301" align="alignleft" width="143"] Dr. Billington[/caption]
Charles Billington MD
Chief, Section of Endocrinology and Metabolism
Minneapolis VA Health Care System
Professor of Medicine, University of Minnesota
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: We wanted to know if adding gastric bypass to intense lifestyle and medical therapy would improve overall diabetes treatment as represented by the triple endpoint of blood sugar, blood pressure and cholesterol control. We found that adding gastric bypass did provide significant benefit at five years after surgery, but that the size of the benefit declined substantially from the first to the fifth year. We also found that gastric bypass did provide significantly better blood sugar control throughout the five years, but the rate of diabetes remission at five years was low. There were many more adverse events in the gastric bypass group.
03 Jan Program Improves Sleep For Mothers Hospitalized For Delivery
MedicalResearch.com Interview with: Kathryn A. Lee, RN, CBSM, PhD
Department of Family Health Care Nursing
University of California at San Francisco
San Francisco, California
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Sleep deprivation can adversely affect health and wellbeing in any patient population.
In pregnancy, adverse outcomes may include preterm birth, longer labor, cesarean birth, and depression.
We found that women with high-risk pregnancies were sleep deprived even prior to hospitalization. Our sample averaged 29 weeks gestation, and half reported getting only between 5 and 6.5 hours of sleep at home before hospital admission. Our sleep hygiene intervention strategies gave them more control over the environment in their hospital room, and they self-reported significantly better sleep than controls. Interestingly, both groups increased their sleep time to almost 7 hours at night, on average, in the hospital before they were discharged home.
03 Jan Should Money Be Used To Encourage Breastfeeding?
MedicalResearch.com Interview with: Clare Relton, PhD
School of Health and Related Research
University of Sheffield, Sheffield, England
MedicalResearch.com: What are the key findings of your report?
Response: Our five year research project explored whether offering financial incentives (shopping vouchers) for breastfeeding increased breastfeeding. We studied what happened to breastfeeding rates at 6 to 8 weeks post-partum in areas in England with low (<40%) breastfeeding prevalence. Our cluster randomized clinical trial (which included 10 010 mother-infant dyads) showed that areas with the financial incentive had significantly higher rates of breastfeeding at 6 to 8 weeks (37.9% vs 31.7%) compared to usual care.
The financial incentive scheme was widely acceptable to healthcare providers (midwives, health visitors, doctors) and mothers. The financial incentives made it easier for everyone to discuss breastfeeding and mothers reported feeling valued (supported and rewarded) for breastfeeding.
03 Jan Even With Preserved Ovaries Hysterectomy Linked To Increased Cardiac and Metabolic Risks
MedicalResearch.com Interview with: [caption id="attachment_39148" align="alignleft" width="166"] Dr. Laughlin-Tommaso[/caption]
Dr. Shannon Laughlin-Tommaso MD
Associate Professor of Obstetrics and Gynecology
Consultant, Division of Gynecology, Department of Obstetrics & Gynecology
Mayo Clinic, Rochester New York
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: There are increasing data from a number of studies about the long term risks of hysterectomy both with and without removing the ovaries. We studied women who underwent hysterectomy with conservation of both ovaries to determine the long-term risk of cardiovascular disease using the Rochester Epidemiology Project (REP). The advantage of using the REP is that we were able to follow women for an average of 22 years, where previous studies had only been able to follow for 7-10 years and we were able to determine which women already had cardiovascular disease risk factors at the time of hysterectomy.
We found that women who undergo hysterectomy have a 33% increased risk of new onset coronary artery disease, a 13% increased risk of hypertension, a 14% increased risk in lipid abnormalities, and an 18% increased risk of obesity. For women who had a hysterectomy before age 35 years, these risks were even higher: 2.5-fold risk of coronary artery disease and 4.6-fold risk of congestive heart failure.
29 Dec Increased Prenatal Care Linked To State Medicaid Expansion
MedicalResearch.com Interview with: [caption id="attachment_39102" align="alignleft" width="200"] Dr. Laura Wherry
credit: UCLA Health[/caption] Laura R. Wherry, Ph.D. Division of General Internal Medicine and Health Services Research David Geffen School of Medicine at UCLA Los Angeles, CA 90024 MedicalResearch.com: What is the background for this study? Response: All states provide Medicaid coverage to pregnant women, but many low-income women do not qualify for the program when they are not pregnant. However, state decisions to expand Medicaid coverage to low-income parents and adults allow low-income women to have Medicaid coverage prior to, and between, their pregnancies. Increased health insurance coverage for low-income women during these non-pregnancy periods may help improve their preconception health and their planning of pregnancies, ultimately leading to healthier pregnancies and infants. This study examines how state expansions in Medicaid coverage for low-income parents before the Affordable Care Act affected the health insurance status of mothers prior to additional pregnancies (i.e. their pre-pregnancy health insurance status). I also examine whether there are changes in pregnancy intention (i.e. whether the pregnancy was mistimed or unwanted), as better access to pre-pregnancy insurance coverage could increase contraception utilization and improve the planning of pregnancies. Finally, I examine whether there were changes in insurance coverage during pregnancy and in the utilization of prenatal care, since women who have pre-pregnancy insurance coverage may experience fewer barriers to establishing care during their pregnancies.