
Medical Imaging
31 Aug Brain Imaging Patterns Moving Closer To Identifying Schizophrenia on Functional MRI
MedicalResearch.com Interview with: [caption id="attachment_36710" align="alignleft" width="179"] Dr. Rish[/caption]
Irina Rish PhD
IBM T.J. Watson Research Center
Yorktown Heights, NY 10598
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Schizophrenia is a chronic and severe psychiatric disorder that affects roughly about 1% of population. Although it is not as common as other mental disorders, such as depression, anxiety, and attention deficit disorder (ADD), and so on, schizophrenia is perhaps one of the most debilitating psychiatric disorders, preventing people from normal functioning in daily life. It is characterized primarily by a range of psychotic symptoms, including hallucinations (false auditory, visual or tactile perceptions detached from reality), as well as delusions, disorganized thoughts, speech and behavior, and multiple other symptoms including difficulty showing (and recognizing) emotions, poor executive functioning, inattentiveness, problems with working memory, and so one. Overall, schizophrenia has a devastating impact not only on patients and their families, but on the economy, as it was estimated to cost the US about 2% off gross national product in treatment costs, missed work, etc.
Thus, taking steps towards better understanding of the disease can potentially lead to more accurate early diagnosis and better treatments.
In this work, the objective was to identify "statistical biomarkers' of schizophrenia from brain imaging data (specifically, functional MRI), i.e. brain activity patterns that would be capable of accurately discriminating between schizophrenic patients and controls, and reproducible (stable) across multiple datasets. The focus on both predictive accuracy (generalization to previously unseen subjects) as well as on stability (reproducibility) across multiple datsets differentiates our work from majority of similar studies in neuroimaging field that tend to focus only on statistically significant differences between such patterns on a fixed dataset, and may not reliably generalize to new data.
Our prior work on neuroimaging-based analysis of schizoprenia http://journals.plos.org/plosone/article/related?id=10.1371/journal.pone.0050625, as well as other research in the field, suggest that disrupted functional connectivity can be a much more informative source of discriminative patterns than local changes in brain activations, since schizophrenia is well known to be a "network disease", rather than a localized one.
29 Jul MRI Biomarkers Track Cognitive Impairment Due to Head Trauma
Posted at 02:17h
in Author Interviews, Brain Injury, Cleveland Clinic, Cognitive Issues, MRI, Occupational Health
MedicalResearch.com Interview with:
[caption id="attachment_36217" align="alignleft" width="160"] Dr. Virendra Mishra[/caption]
Virendra Mishra, Ph.D.
Department of Imaging Research
Cleveland Clinic Lou Ruvo Center for Brain Health in Las Vegas
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Repetitive head trauma has been shown to be a risk factor for various neurodegenerative disorders, mood swings, depression and chronic traumatic encephalopathy. There has been a significant amount of research into identifying an imaging biomarker of mild traumatic brain injury (mTBI) due to repetitive head trauma. Unfortunately, most of the biomarkers have not been able to find a successful translation to clinics. Additionally, the quest for the mTBI imaging biomarker especially using Magnetic Resonance Imaging (MRI) techniques has been done by looking at either the gray matter (T1-weighted) or the white matter (Diffusion Tensor Imaging) independently; and both have shown changes that are associated with repetitive head trauma.
Hence in this study, we wanted to investigate if combining gray matter and white matter information enables us to better predict the fighters who are more vulnerable to cognitive decline due to repetitive head trauma. Our method found seven imaging biomarkers that when combined together in a multivariate sense were able to predict with greater than 73% accuracy those fighters who are vulnerable to cognitive decline both at baseline and follow-up. The imaging biomarkers were indeed a combination of gray and white matter measures of regions reported previously in the literature. A key point in our study was we found the regions predicting cognitive decline without enforcing any assumptions on the regions previously reported.
19 Jun Photodynamic Therapy Being Developed To Target Prostate Cancer
MedicalResearch.com Interview with: Dr. Susanne Lütje Ärztlicher Dienst Universitätsklinikum Essen (AöR) Klinik für Nuklearmedizin Essen Germany MedicalResearch.com: What is the background for this study? What are the main findings? Response: Prostate cancer (PCa) is the most common cancer in men and accounts for a significant amount of morbidity and mortality. At present, the curative treatment option of choice for localized stages of PCa is radical prostatectomy, which may include extended lymph node dissection. Unfortunately, surgical procedures can be accompanied by complications such as urinary incontinence. Most importantly, small tumor deposits may not be seen by the surgeon during surgery and could ultimately lead to disease recurrence. To overcome these issues, new and innovative treatments are needed. The prostate-specific membrane antigen (PSMA) is a surface protein that is overexpressed in prostate cancer and can be used as a target to guide new therapies. Photodynamic therapy (PDT) is an ablative procedure in which tumor cells can be destroyed effectively by irradiation of light of a specific wavelength, which activates previously administered photosensitizers. The photosensitizers can respond by emitting fluorescence or emitting oxygen radicals which can cause cellular damage. Coupling the photosensitizer to an agent that targets PSMA on the tumor surface offers the possibility to selectively and effectively destroy prostate tumor remnants and micrometastases, while surrounding healthy tissues remain unaffected. In our study, the PSMA targeting antibody D2B was coupled to the photosensitizer IRDye700DX and radiolabeled with 111In. In a mouse model, this multi-modality agent was used to preoperatively visualize tumor lesions with SPECT/CT to allow rough localization of the tumors. During surgery, the fluorescent signal originating from the photosensitizer facilitates visualization of tumors and residual tumor tissue, so the surgeon can be guided towards accurate resection of the entire tumors and metastases. In addition, the PSMA-targeted PDT can be applied to destroy small tumor deposits in cases where close proximity of the tumors.09 Jun MRI At Six Months Can Predict Which High Risk Babies Will Develop Autism
MedicalResearch.com Interview with: [caption id="attachment_35164" align="alignleft" width="150"] Dr. Piven[/caption]
Joseph Piven, MD
The Thomas E. Castelloe Distinguished Professor of Psychiatry
UNC School of Medicine
Director of the Carolina Institute for Developmental Disabilities
Co-senior author of the study
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Babies with older siblings with autism are at an increased risk (20%) of getting autism over the general population (1%). Infants who later are diagnosed with autism don’t have any of the stigmata of autism in the first year of life. The symptoms of autism unfold in the first and particularly in the second year of life and beyond.
We have evidence to support the idea that behavioral symptoms of autism arise from changes in the brain that occur very early in life. So we have employed MRI and computer analyses to study those early brain changes and abnormalities in infancy to see if early brain changes at 6 months of age can predict whether babies at high-risk of developing autism will indeed develop the condition at age two.
For this particular study, we used data from MRIs of six-month olds to show the pattern of synchronization or connection across brain regions throughout the brain and then predict which babies at high familial risk of developing autism would be most likely to be diagnosed with the condition at age two.
01 Jun Diagnostic Accuracy of FFR-CT Varies Across Spectrum of Coronary Artery Disease
MedicalResearch.com Interview with: Dr Christopher Michael Cook MBBS Bsc(Hons) MRCP MRC Clinical Research Fellow NHLI, Cardiovascular Medicine, Imperial College London MedicalResearch.com: What is the background for this study? Response: FFR-CT is a novel non-invasive technique for estimating the functional significance of a coronary stenosis from CT coronary angiography images. A number of meta-analyses already exist for determining the...
21 May MRI Guided Prostate Biopsies Can Improve Care and Reduce Costs
MedicalResearch.com Interview with: [caption id="attachment_34738" align="alignleft" width="133"] Dr. Gulani[/caption]
Vikas Gulani, MD, PhD
Director, MRI, UH Cleveland Medical Center
Associate Professor, Radiology, CWRU School of Medicine
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: We wanted to learn if performing MR before prostate biopsy, followed by MR guided strategies for biopsy, are cost effective for the diagnosis of prostate cancer in men who have not previously undergone a biopsy and who have a suspicion of prostate cancer.
The most significant findings are as follows:
We found that all three MR guided strategies for lesion targeting (cognitive targeting, MR-ultrasound fusion targeting, and in-gantry targeting) are cost effective, as the increase in net health benefits as measured by addition of quality adjusted life years (QALY), outweigh the additional costs according to commonly accepted willingness to pay thresholds in the United States.
Cognitive targeting was the most cost effective. In-gantry biopsy added the most health benefit, and this additional benefit was cost-effective as well.
21 Apr No Magic Age To Stop Performing Screening Mammograms
MedicalResearch.com Interview with: Cindy S. Lee, MD Department of Radiology and Biomedical Imaging University of California, San Francisco, San Francisco Now with Department of Radiology NYU Langone Medical Center, Garden City, New York MedicalResearch.com: What led you and colleagues to conduct this study? Response: I am a breast imager. I see patients who come in for their screening mammograms and I get asked, a lot, if patients aged 75 years and older should continue screening, because of their age. There is not enough evidence out there to determine how breast cancer screening benefits women older than 75. In fact, all previously randomized trials of screening mammography excluded people older than 75 years. Unfortunately, age is the biggest risk factor for breast cancer, so as patients get older, they have higher risks of developing breast cancer. It is therefore important to know how well screening mammography works in these patients.19 Apr Cardiac Magnetic Resonance Can Exclude Clinically Relevant Coronary Artery Disease
MedicalResearch.com Interview with: [caption id="attachment_34037" align="alignleft" width="132"] Pr. Schwitter[/caption]
Pr. Juerg Schwitter MD
Médecin Chef Cardiologie
Directeur du Centre de la RM Cardiaque du CHUV
Centre Hospitalier Universitaire Vaudois - CHUV
Suisse
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Coronary artery disease (CAD) is still one of the leading causes of death in the industrialized world and as such, it is also an important cost driver in the health care systems of most countries. For the European Union, the estimated costs for CAD management were 60 billion Euros in 2009, of which approximately 20 billion Euros were attributed to direct health care costs (1). In 2015, the total costs of CAD management in the United States were estimated to be 47 billion dollars (2).
Substantial progress has been achieved regarding the treatment of CAD including drug treatment but also revascularizations procedures. There exists a large body of evidence demonstrating myocardial ischemia as one of the most important factors determining the patient’s prognosis and reduction of ischemia has been shown to improve outcome.
On the other hand, techniques to detect CAD, i.e. relevant myocardial ischemia, were insufficient in the past. Evaluation of myocardial perfusion by first-pass perfusion cardiac magnetic resonance (CMR) is now closing this gap (3) and CMR is recommended by most international guidelines for the work-up of known or suspected CAD (4,5).
Still, a major issue was not clarified until now, i.e. “how much ischemia is required to trigger revascularization procedures”. Thus, this large study was undertaken to assess at which level of ischemia burden, patients can be safely deferred from revascularization and can be managed by risk factor treatment only. Of note, this crucial question was addressed in both, patients with suspected CAD but also in patients with known (and sometimes already advanced) CAD, thereby answering this question in the setting of daily clinical practice.
18 Apr Doctors Continue To Order Mammograms Outside of Current Age Guidelines
MedicalResearch.com Interview with: Archana Radhakrishnan MD MHS Division of General Internal Medicine Johns Hopkins University Baltimore, Maryland MedicalResearch.com: What is the background for this study? What are the main findings? Response: We were interested in understanding the current practice trends in breast cancer screening recommendations by doctors in light of the guideline changes. We performed a national survey of primary care providers and gynecologists asking about their breast cancer screening practices. We found that a large number of doctors recommend breast cancer screening to younger and older women—upwards of 80% of doctors recommend it for younger women (ages 40-44) and almost 70% for women 75 and older. But this varies by the type of doctor that a woman see. Gynecologists were, in general, more likely to recommend routine mammograms.30 Mar Ischemic Stroke: Collateral Blood Vessels Detected by Arterial Spin Labeling MRI Correlates With Good Neurological Outcome
MedicalResearch.com Interview with: Jalal B. Andre M.D., D.A.B.R.® Drector of neurological MRI and MRI safety officer at Harborview Medical Center University of Washington MedicalResearch.com: What is the background for this study? Response: Acute ischemic stroke (AIS) patients with good collaterals have better clinical outcomes. AIS is characterized by an ischemic penumbra, a region of salvageable brain tissue, that surrounds a core of irreversible ischemic infarct. The penumbra is tenuously perfused by collateral blood vessels which, if extensive enough, can maintain penumbral perfusion, improving the odds that a larger volume of brain tissue will survive. Standard, first-line methods for evaluating collaterals in the acute setting include CT angiography, MR angiography, and (less commonly) digital subtraction angiography. Arterial spin labeling (ASL) is an emerging MRI technique that assesses cerebral perfusion. Its advantages include relatively short scan time (4-6 minutes), lack of ionizing radiation, and independence from an exogenous contrast agent (contraindicated in patients with impaired renal function or documented sensitivity). Collaterals can be identified within ASL images as foci of curvilinear hyperintensity bordering regions of hypoperfusion. We sought to explore a novel relationship between the presence of ASL collaterals (ASLc) and neurological outcome in acute ischemic stroke patients.20 Mar Instantaneous Wave-Free Ratio To Evaluate Coronary Artery Disease
MedicalResearch.com Interview with: [caption id="attachment_32970" align="alignleft" width="200"] Dr. Matthias Götberg[/caption]
Matthias Götberg, MD, PhD
Director Cardiac Cath Lab
Department of Coronary Heart Disease
Skane University Hospital- Lund
Lund, Sweden
MedicalResearch.com: What is the background for this study?
Response: Cardiologists encounter patients with narrowing of the coronary arteries on a daily basis. They typically use visual estimation of the severity of narrowing when performing coronary angiography, but it is difficult to accurately assess, based on a visual estimation alone, whether a stent is needed to widen the artery and allow the blood to more freely.
FFR (Fractional Flow Reserve) is more precise tool and results in better outcomes than using angiography alone to assess narrowing of the coronary arteries. With FFR, the doctor threads a thin wire through the coronary artery and measures the loss of blood pressure across the narrowed area. To acquire an accurate measurement, the patient must be given adenosine, which is a drug that dilates the blood vessels during the procedure. This drug causes discomfort; patients describe having difficulty breathing or feeling as if someone is sitting on their chest. The drug also adds to the cost of the procedure and can have other rare but serious side effects.
iFR (Instantaneous Wave-Free Ratio) is also based on coronary blood pressure measurements using a thin wire, but unlike FFR, it uses a mathematical algorithm to measure the pressure in the coronary artery only when the heart is relaxed and the coronary blood flow is high. As a result, a vasodilator drug is not needed.
iFR has been validated in smaller trials and have been found to be equally good as FFR to detect ischemia, but larger randomized outcome trials are lacking.
iFR-Swedeheart is a Scandinavian Registry-based Randomized Clinical Trial (RRCT) in which 2000 patients were randomized between iFR and FFR as strategies for performing assessment of narrowed coronary vessels. The primary composite endpoint at 12 months was all-cause death, non-fatal myocardial infarction, and unplanned revascularization.
RRCT is a new trial design originating from Scandinavia using existing web-based national quality registries for online data entry, randomization and tracking of events. This allows for a very high inclusion rate and low costs to run clinical trials while ensuring robust data quality.
19 Mar iFR Can Assess Need For Coronary Revascularization Without Adenosine
Posted at 23:13h
in Author Interviews, Heart Disease, Imperial College, Medical Imaging, Surgical Research
MedicalResearch.com Interview with:
[caption id="attachment_33035" align="alignleft" width="149"] Dr. Davies[/caption]
Dr. Justin Davies PhD
Senior Reserch Fellow and Hononary Consultant Cardiologist
National Heart and Lung Institute,
Imperial College London
MedicalResearch.com: What is the background for this study?
Response: We know from the FAME study that compared to angiography alone, FFR guided revascularization improves long-term clinical outcomes for our patients. Despite this, adoption of FFR into everyday clinical practice remains stubbornly low. One major factor for this is the need for adenosine (or other potent vasodilator medications) in order to perform an FFR measurement. Adenosine is expensive, unpleasant for the patient, time consuming and even potentially harmful.
iFR is a newer coronary physiology index that does not require adenosine for its measurement. In the prospective, multi center, blinded DEFINE FLAIR study, 2492 patients were randomly assigned to either FFR guided revascularisation or iFR guided revascularization and followed up for a period of 1 year.
19 Mar Radiation Exposure and Vascular Access in Acute Coronary Syndromes: The RADMatrix Trial
[caption id="attachment_32906" align="alignleft" width="200"] Dr. Marco Valgimigli[/caption]
MedicalResearch.com Interview with:
Dr. Marco Valgimigli, MD, PhD
Interventional Cardiology
Sandro Pertini Hospital, ASL RM2, Rome, Italy
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Every year millions of people with coronary artery disease are treated worldwide with percutaneous coronary intervention (PCI). Radial access as compared to femoral access reduces bleeding and mortality in patients with acute coronary syndrome (ACS) undergoing invasive management. However, prior studies have raised concerns over the increased risk of radiation exposure for both patients and operators with radial instead of femoral access and it remains still unclear whether radial access increases the risk of operator or patient radiation exposure in contemporary practice when performed by expert operators.
The MATRIX (Minimizing Adverse Haemorrhagic Events by TRansradial Access Site and Systemic Implementation of angioX) trial is the largest randomized trial comparing radial versus femoral access in ACS patients undergoing invasive management. In this radiation sub-study (RAD-MATRIX), we collected fluoroscopy time and dose area product (DAP) and equipped radial operators consenting to participate with dedicated dosimeters, each wearing a thorax (primary endpoint), wrist and head (secondary endpoints) lithium fluoride thermo luminescent dosimeter, during study conduct to establish non-inferiority of radial versus femoral access.
Among eighteen operators, performing 777 procedures in 767 patients, the non-inferiority primary endpoint was not achieved. Operator equivalent dose at the thorax was significantly higher with radial than femoral access. After normalization of operator radiation dose by fluoroscopy time or DAP, the difference remained significant. Radiation dose at wrist or head did not differ between radial and femoral access. Thorax operator dose did not differ in the right radial compared to the left radial access. In the overall MATRIX population, fluoroscopy time and DAP were higher with radial as compared to femoral access.
19 Mar Instantaneous Wave-free Ratio vs Fractional Flow Reserve to Guide PCI
MedicalResearch.com Interview with: [caption id="attachment_33059" align="alignleft" width="200"] Dr. Matthias Götberg[/caption]
Dr. Matthias Götberg MD PhD
Department of Cardiology, Clinical Sciences
Lund University, Skåne University Hospital
Lund, Sweden
MedicalResearch.com: What is the background for this study?
Response: Cardiologists encounter patients with narrowing of the coronary arteries on a daily basis. They typically use visual estimation of the severity of narrowing when performing coronary angiography, but it is difficult to accurately assess, based on a visual estimation alone, whether a stent is needed to widen the artery and allow the blood to more freely.
FFR (Fractional Flow Reserve) is more precise tool and results in better outcomes than using angiography alone to assess narrowing of the coronary arteries. With FFR, the doctor threads a thin wire through the coronary artery and measures the loss of blood pressure across the narrowed area. To acquire an accurate measurement, the patient must be given adenosine, which is a drug that dilates the blood vessels during the procedure. This drug causes discomfort; patients describe having difficulty breathing or feeling as if someone is sitting on their chest. The drug also adds to the cost of the procedure and can have other rare but serious side effects.
iFR (Instantaneous Wave-Free Ratio) is also based on coronary blood pressure measurements using a thin wire, but unlike FFR, it uses a mathematical algorithm to measure the pressure in the coronary artery only when the heart is relaxed and the coronary blood flow is high. As a result, a vasodilator drug is not needed.
iFR has been validated in smaller trials and have been found to be equally good as FFR to detect ischemia, but larger randomized outcome trials are lacking.
iFR-Swedeheart is a Scandinavian Registry-based Randomized Clinical Trial (RRCT) in which 2000 patients were randomized between iFR and FFR as strategies for performing assessment of narrowed coronary vessels. The primary composite endpoint at 12 months was all-cause death, non-fatal myocardial infarction, and unplanned revascularization.
RRCT is a new trial design originating from Scandinavia using existing web-based national quality registries for online data entry, randomization and tracking of events. This allows for a very high inclusion rate and low costs to run clinical trials while ensuring robust data quality.
15 Mar Clinical Outcomes Following a Low-Suspicion MRI for Prostate Cancer
MedicalResearch.com Interview with: [caption id="attachment_32943" align="alignleft" width="180"] Dr. Boessen[/caption] Lars Boesen MD PhD Department of Urology Herlev Gentofte University Hospital Herlev MedicalResearch.com: What is the background for this study? What are the main findings? Response: Transrectal ultrasound-guided biopsies (TRUS-bx) traditionally used for detecting prostate cancer (PCa) are prone to sampling errors due to difficulties in target identification....
07 Mar Using Post-Resuscitation ECG To Predict Need For Brain CT
MedicalResearch.com Interview with: [caption id="attachment_32752" align="alignleft" width="200"] Dr. Won Young Kim[/caption]
Won Young Kim, MD
Department of Emergency Medicine
Ulsan University College of Medicine
Asan Medical Center
Seoul, Korea
MedicalResearch.com: What is the background for this study?
Response: The current advanced cardiac life support guidelines recommended emergent percutaneous intervention for out-of-hospital cardiac arrest (OHCA) survivors with ST-segment elevation and suspected cardiac origin without ST-segment elevation. However, spontaneous subarachnoid hemorrhage (SAH) is a well-known cause of cardiac arrest, and its electrocardiogram may mimic myocardial infarction or ischemia. The need and timing for brain computed tomography in non-traumatic OHCA remain controversial.
The present study aimed at determining the role of the post-resuscitation ECG in patients with significant ST-segment changes on initial ECG to investigate the difference in post-resuscitation ECG characteristics between OHCA patients with SAH and those with suspected cardiac origin of OHCA.
01 Mar Subtle Differences in Brain Volume Detected On MRI In ADHD
MedicalResearch.com Interview with: M. (Martine) Hoogman PhD. Postdoc and PI of ENIGMA-ADHD Radboud universitair medisch centrum Department of Human Genetics Nijmegen, The Netherlands MedicalResearch.com: What is the background for this study? What are the main findings? Response: There are many neuro-imaging studies aimed at investigating structural brain changes related to ADHD, but the results are often inconclusive. There are two main reasons for this: 1) the small sample size of the studies and 2) the heterogeneous methods used. We tried to address these issues by forming an international collaboration to provide a sample size sufficient to detect even small effects in volume differences. And in addition, we analyzed all the raw scans again using homogenized methods. There are data of more than 1700 patients (aged 4-63 years of age) and more than 1500 healthy controls in our dataset, coming from 23 sites around the world. We studied the possible volume differences between cases and controls of 7 subcortical regions and intracranial volume by performing mega- and meta-analysis.25 Feb Can Patients With A Pacemaker or Defibrillator Get An MRI?
MedicalResearch.com Interview with: [caption id="attachment_32206" align="alignleft" width="200"] Dr. Robert Russo[/caption]
Robert Russo, MD, PhD, FACC
The Scripps Research Institute
The La Jolla Cardiovascular Research Institute
MedicalResearch.com: What is the background for this study?
Response: For an estimated 2 million people in the United States and an additional 6 million people worldwide, the presence of a non-MRI-conditional pacemaker or implantable cardioverter defibrillator (ICD) is considered a contraindication to magnetic resonance imaging. This creates a dilemma for at least half of these patients, who are predicted to require an MRI scan during their lifetime after a cardiac device has been implanted. Safety concerns for patients with an implanted cardiac device undergoing MRI are related to the potential for magnetic field-induced cardiac lead heating resulting in myocardial thermal injury, and a detrimental change in pacing properties. As a result, patients with an implanted device have long been denied access to MRI, although it may have been the most appropriate diagnostic imaging modality for their clinical care. Despite the development of MRI-conditional cardiac devices, a strategy for mitigating risks for patients with non MRI-conditional devices and leads will remain an enduring problem for the foreseeable future due to an ever increasing demand for MRI and the large number of previously and currently implanted non-MRI-conditional devices.
10 Feb False Positive Mammograms Can Lead Women To Delay or Skip Next Exam
MedicalResearch.com Interview with: [caption id="attachment_31912" align="alignleft" width="174"]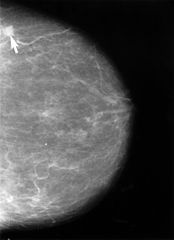 Mammogram showing small lesion
- Wikipedia[/caption] Firas Dabbous, PhD Manager, Patient Centered Outcomes Research Russell Institute for Research & Innovation Advocate Lutheran General Hospital Park Ridge, IL MedicalResearch.com: What is the background for this study? Response: When women are told that there is something abnormal on their screening mammogram that can cause stress and worry while undergoing additional testing, even when they are later told that there is nothing wrong. We wanted to know if receiving a false positive screening mammogram would cause women to think twice before getting their next screening mammogram, and maybe delay coming back for their next screen. This is important because patients who have a false positive experience may have higher chance to develop breast cancer at a later point in time. Therefore, it is important to understand their screening patterns to better educate and inform them about the importance of adhering to mammography guidelines and emphasize the importance of returning on schedule for their next screens.
02 Feb Annual CT Lung Cancer Screening Among Former Smokers Remains Underutilized
MedicalResearch.com Interview with: [caption id="attachment_31705" align="alignleft" width="138"] Dr. Ahmedin Jemal[/caption]
Ahmedin Jemal, DVM, PHD
Vice President, Surveillance and Health Services Research
American Cancer Society, Inc.
250 Williams St.
Atlanta, GA 30303
MedicalResearch.com: What is the background for this study?
Response: In December 2013, the United States Preventive Services Task Force (USPSTF) recommended annual screening for lung cancer with low dose computed tomography (LDCT) for current or former heavy smokers who quit within the past 15 years.
A previous study estimated that only 2-4% of heavy smokers received LDCT for lung cancer screening in 2010 in the United States. We sought to determine whether lung cancer screening among high risk smokers increased in 2015, following the USPSTF recommendation in 2013.
30 Jan Comprehensive Lung Cancer Screening Is Complex Task With Many False Positives
MedicalResearch.com Interview with: [caption id="attachment_31587" align="alignleft" width="200"] Dr. Linda Kinsinger[/caption]
Linda Kinsinger, MD, MPH
National Center for Health Promotion and Disease Prevention
U.S. Department of Veterans Affairs
NW Washington DC 20420
MedicalResearch.com: What is the background for this study?
Response: The U.S. Preventive Services Task Force recommends annual lung cancer screening with low-dose computed tomography (LDCT) for current and former heavy smokers ages 55 to 80.
However, clinicians have questioned the practical aspects of implementing lung cancer screening. VA provides care for 6.7 million Veterans each year, mostly older men – many of whom are current or former smokers – thus the implementation of a lung cancer screening program for VA patients would require substantial resources. In order to understand the feasibility and implications of this for patients and clinical staff, VA implemented a three-year Lung Cancer Screening Demonstration Project (LCSDP) in eight geographically-diverse VA hospitals. Investigators identified 93,033 primary care patients at eight sites who were assessed on screening criteria, of whom 2,106 patients were screened between July 2013 and June 2015.
25 Jan Many CT Scans Can Be Avoided During ER Evaluation of Head Trauma
Posted at 23:13h
in Author Interviews, Brain Injury, Cost of Health Care, CT Scanning, Electronic Records, Emergency Care, Kaiser Permanente
MedicalResearch.com Interview with:
[caption id="attachment_31510" align="alignleft" width="156"] Dr. Adam Sharp[/caption]
Adam L. Sharp MD MS
Research Scientist/Emergency Physician
Kaiser Permanente Southern California
Kaiser Permanente Research
Department of Research & Evaluation
Pasadena, CA 91101
MedicalResearch.com: What is the background for this study?
Response: Millions of head computed tomography (CT) scans are ordered annually in U.S. emergency Departments (EDs), but the extent of avoidable imaging is poorly defined. Ensuring appropriate use is important to ensure patient outcomes and limited resources are optimized. A large number of stake holders have highlighted the need to reduce “unnecessary” CT scanning as part of their recommendations for the Choosing Wisely campaign. However, despite calls for improved stewardship, the extent of avoidable CT use among adults with minor trauma in community EDs is not known.
The Canadian CT Head Rule (CCHR) is perhaps the most studied of many validated decision instruments designed to assist providers in evaluating patients with minor head trauma. This study aims to describe the scope of overuse of CT imaging by ED providers in cases where application of the CCHR could have avoided imaging.
Secondarily, we sought to describe the extent to which avoidable CTs, if averted, would have resulted in “missed” intracranial hemorrhages requiring a neurosurgical intervention.
12 Jan PET Scanning Highlights Link Between Stress and Heart Disease
Posted at 12:15h
in Author Interviews, Brigham & Women's - Harvard, Heart Disease, Lancet, Medical Imaging, MRI, Social Issues
MedicalResearch.com Interview with:
[caption id="attachment_31180" align="alignleft" width="135"] Dr Ahmed Tawakol[/caption]
Dr Ahmed Tawakol MD
Co-Director, Cardiac MR PET CT Program
Massachusetts General Hospital and
Harvard Medical School
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: While the link between stress and heart disease has long been established, the mechanism mediating that risk hasn’t been clearly understood. Animal studies showed that stress activates bone marrow to produce white blood cells, leading to arterial inflammation. This study suggests an analogous path exists in humans. Moreover, this study identifies, for the first time in animal models or humans, the region of the brain (the amygdala) that links stress to the risk of heart attack and stroke.
The paper reports on two complementary studies.
The first analyzed imaging and medical records data from almost 300 individuals who had PET/CT brain imaging, primarily for cancer screening, using a radiopharmaceutical called FDG that both measures the activity of areas within the brain and reflects inflammation within arteries. All participants in that study had no active cancer or cardiovascular disease at the time of imaging and each had information in their medical records on at least three additional clinical visits after imaging.
The second study enrolled 13 individuals with a history of post-traumatic stress disorder, who were evaluated for their current levels of perceived stress and received FDG-PET scanning to measure both amygdala activity and arterial inflammation.
09 Jan ACA: Screening Disparities Fall For Mammograms But Not Colonoscopies
Posted at 13:02h
in Author Interviews, Breast Cancer, Cancer Research, Colon Cancer, Cost of Health Care, Mammograms, Medical Imaging, Race/Ethnic Diversity, Radiology
MedicalResearch.com Interview with:
[caption id="attachment_31020" align="alignleft" width="133"] Dr. Gregory Cooper[/caption]
Dr. Gregory Cooper, MD
Program Director, Gastroenterology
UH Cleveland Medical Center
Co-Program Leader for Cancer Prevention and Control, UH Cleveland Medical Center
Professor, Medicine, CWRU School of Medicine
Co-Program Leader for Cancer Prevention and Control
UH Seidman Cancer Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The Affordable Care Act, among other features, removed out of pocket expenses for approved preventive services, and this may have served as a barrier to cancer screening in socioeconomically disadvantaged individuals. If so, then the gap in screening between socioeconomic groups should narrow following the ACA.
The main findings of the study were that although in the pre-ACA era, there were disparities in screening, they narrowed only for mammography and not colonoscopy.
17 Dec MRI Can Better Diagnose Fetal Brain Abnormalities in-Utero
MedicalResearch.com Interview with: Prof Paul D Griffiths, FRCR and Cara Mooney, Study Manager: MERIDIAN Clinical Trials Research Unit The University of Sheffield MedicalResearch.com: What is the background for this study? What are the main findings? Response: Around three in every 1000 pregnancies is complicated by a fetal abnormality. In the UK Ultrasonography (USS) has, for many years, been the mainstay of antenatal screening and detailed anomaly scanning to detect such abnormalities. However previous studies have suggested that in utero Magnetic Resonance (iuMR) imaging may be a useful adjunct to USS for detecting these brain abnormalities in the developing fetus. This study was designed to test the diagnostic accuracy and clinical impact of introducing fetal MR in to the diagnostic pathway. Our results show that iuMR has an overall diagnostic accuracy of 93% compared to ultrasound at 68%, this is an increase in diagnostic accuracy of 25%. When divided into gestational age group the improvement in diagnostic accuracy ranged from 23% in the 18-23 week group, and 29% in the 24 week and over group. IuMR provided additional diagnostic information in 49% of cases, changed prognostic information in at least 20% and the contribution to clinical management was felt to be at least ‘significant’ in 35% of cases. IuMR also had high patient acceptability with at least 95% of women stating that they would have an iuMR if a future pregnancy were complicated by a fetal brain abnormality.12 Dec Image-Guided Biopsies May Reduce Need For Surgery in Breast Cancer Patients Who Respond to Chemotherapy
Posted at 21:52h
in Author Interviews, Breast Cancer, Chemotherapy, Mammograms, MD Anderson, Surgical Research
MedicalResearch.com Interview with:
[caption id="attachment_30458" align="alignleft" width="175"] Dr. Henry M. Kuerer[/caption]
Henry M. Kuerer, MD, PhD, FACS
Executive Director, Breast Network Programs
MD Anderson Cancer Network
PH and Fay Etta Robinson Distinguished Professor in Research
Department of Breast Surgical Oncology
Director, Breast Surgical Oncology Training Program
MedicalResearch.com: What is the background for this study?
Response: Worldwide, triple negative and HER2 positive breast cancers, combined, account for about 370,000 women diagnosed annually. With recent advances in neoadjuvant systemic therapy (NST, chemotherapy and targeted therapy given before surgery) for both subsets, the pCR (pathologic complete response- when no residual cancer is found) rates found at the time of surgery in these populations can be as high as 60 percent. This high rate of pCR naturally raises the question of whether surgery is required for all patients, particularly those who will receive adjuvant radiation.
We believe surgery may potentially be redundant – at least for these two subtypes of breast cancer – because of such a high chance for no evidence of disease at the time of pathological review. If there’s no cancer left after the patient has received chemotherapy and the patient is going to receive local radiation therapy, is surgery actually needed?
The challenge has been that standard breast imaging methods cannot accurately predict residual disease after NST. However, by doing the same image-guided percutaneous needle biopsies after neoadjuvant systemic therapy that we do at time of diagnosis, our preliminary research reveals that we may be able to accurately predict which women will have cancer or not.
09 Dec Cerebral Perfusion Is Perturbed by Preterm Birth and Brain Injury
MedicalResearch.com Interview with: Eman S. Mahdi, MD, MBChB Pediatric Radiology Fellow [caption id="attachment_30368" align="alignleft" width="133"] Dr. Catherine Limperopoulos[/caption]
Catherine Limperopoulos, PhD
Director, Developing Brain Research Laboratory
Co-Director of Research, Division of Neonatology
Diagnostic Imaging and Radiology
Children’s National Health System
Washington, DC
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Premature birth is a major public health concern in the United States affecting 1 in 10 infants each year. Prematurity-related brain injury is very common and associated with a high prevalence of brain injury and accompanying lifelong neurodevelopmental morbidities.
Early disturbances in systemic and cerebral hemodynamics are thought to mediate prematurity-related brain injury. The extent to which cerebral blood flow (CBF) is disturbed in preterm birth is poorly understood, in large part because of the lack of monitoring techniques that can directly and non-invasively measure cerebral blood flow.
We report for the first time early disturbances in global and regional cerebral blood flow in preterm infants following brain injury on conventional magnetic resonance imaging (MRI) over the third trimester of ex-uterine life using arterial spin labelling images. In terms of regional differences, we saw a marked decrease in blood flow to the thalamus and the pons, regions known to be metabolically active during this time.
02 Dec CT Angiography Study Finds No Association Between Alcohol and Coronary Artery Disease
MedicalResearch.com Interview with: Pál Maurovich-Horvat MD, PhD, MPH, FSCCT Assistant Professor of Cardiology Director of the MTA-SE Cardiovascular Imaging Research Group Heart and Vascular Center, Semmelweis University Budapest, Hungary MedicalResearch.com: What is the background for this study? What are the main findings? Response: Several studies have been published on alcohol consumption and its association with the presence of coronary artery disease, however the data remains controversial. Some studies suggested that moderate alcohol consumption reduces the risk of heart disease and others found no protective effect. Our study is the first investigation that aims to assess the effect of alcohol on the coronary arteries using coronary CT angiography. We found no association between regular alcohol consumption and the presence of coronary disease.02 Dec God Activates Reward Centers In Brain
MedicalResearch.com Interview with: [caption id="attachment_30097" align="alignleft" width="133"] Dr. Jeffrey S. Anderson[/caption]
Jeffrey S. Anderson, MD, PhD
Director the fMRI Neurosurgical Mapping Service
Principal Investigator for the Utah Functional Neuroimaging Laboratory
University of Utah
MedicalResearch.com: What is your study about?
Response: Billions of people find meaning in life and make choices based on religious and spiritual experiences. These experiences range from epiphanies that change the lives of celebrated mystics to subtle feelings of peace and joy in the lives of neighbors, friends, or family members that are interpreted as spiritual, divine, or transcendent.
Astonishingly, with all we understand about the brain, we still know very little about how the brain participates in these experiences. We set out to answer what brain networks are involved in representing spiritual feelings in one group of people, devout Mormons.