
JAMA
17 Jul Primary Care Practice Interventions Helped Maintain Adherence to Opioid Prescription Guidelines
MedicalResearch.com Interview with: [caption id="attachment_35965" align="alignleft" width="110"] Dr. Liebschutz[/caption]
Jane M. Liebschutz, MD, MPH
Associate Professor of Medicine
Section of General Internal Medicine
Boston University School of Medicine
Boston, Massachusetts
MedicalResearch.com: What is the background for this study?
Response: The number of patients receiving opioids for chronic pain has risen over the past 2 decades in the US, in parallel with an increase in opioid use disorder. The CDC and professional medical societies have created clinical guidelines to improve the safety of opioid prescribing, yet individual prescribers can find them onerous to implement.
We developed an intervention to change clinical practice to support primary care physicians who prescribe the majority of opioids for chronic pain. The intervention included 4 elements- a nurse care manager to help assess, educate and monitor patients, an electronic registry to keep track of patient data and produce physician level reports, an individualized educational session for the physician by an opioid prescribing expert based on the physician-specific practice information and online resources to help with decision-making for opioid prescribing (www.mytopcare.org). We tested whether the intervention would improve adherence to guidelines, decrease opioid doses and decrease early refills, as a marker of potential prescription opioid misuse among 985 patients of 53 primary care clinicians in four primary care practices.
15 Jul Patient Proxies Increasingly Important As Health Care Fragments
MedicalResearch.com Interview with: [caption id="attachment_35938" align="alignleft" width="142"] Dr. Teno[/caption] Dr. Joan Teno, MD MD Cambia Palliative Care Center of Excellence Seattle, WA MedicalResearch.com: What is the background for this study? What are the main findings? Response: Our interest is understanding how continuity of care has changed with the eventual goal of understanding the impact on quality...
14 Jul Study Reports Hair Repigmentation During Immunotherapy For Lung Cancer
MedicalResearch.com Interview with: Dr. Noelia Rivera MD Dermatologist Hospital Universitari Germans Trias i Pujol, Badalona Universitat Autònoma de Barcelona MedicalResearch.com: What is the background for this study? Response: In the last few years some new therapies targeting immune checkpoints have been developed. The programmed death receptor-1 (PD-1) are immune checkpoints that prevent the immune system to act against own tissues. By blocking these mediators it is possible to prevent tumors to escape from the immune system. About half of the patients receiving these therapies will develop mild to moderate cutaneous adverse events. In the pre-authorization studies for malignant melanoma these include rash, vitiligo, and pruritus. "Rash" has commonly been reported as an adverse event in many oncologic trials evaluating the drugs, without providing further information about the clinical or histological details. Lately, lichenoid eruptions associated to these therapies have been reported and it suggests that an important percentage of these reactions present lichenoid histological features.13 Jul Higher HIV Viral Loads Linked to Increased Squamous Cell Cancers of Skin
Posted at 23:51h
in Author Interviews, Brigham & Women's - Harvard, Cancer Research, Dermatology, HIV, JAMA, Kaiser Permanente, Merck
MedicalResearch.com Interview with:
[caption id="attachment_35902" align="alignleft" width="200"] Dr. Asgari[/caption]
Maryam M. Asgari, MD, MPH
Department of Dermatology
Massachusetts General Hospital,
Department of Population Medicine
Harvard Medical School, Boston, Massachusetts
Division of Research, Kaiser Permanente
Northern California, Oakland
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Nonmelanoma skin cancer – defined as basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) – is a common malignant condition, affecting more than 2 million Americans every year. BCCs are more common than SCCs among individuals with healthy immune systems, while SCCs are more predominate than BCCs among people who are immunocompromised.
We examined how laboratory markers used to evaluate HIV disease progression may be associated with subsequent nonmelanoma skin cancer risk in white patients previously diagnosed with at least one such cancer from 1996 to 2008. We measured CD4 count, viral load and subsequent nonmelanoma skin cancer. The study included 455 participants with HIV and 1,952 without HIV. All were members of the Kaiser Permanente Northern California health care plan.
12 Jul Use of IVC Filters Drops After FDA Device Warning
MedicalResearch.com Interview with: [caption id="attachment_35872" align="alignleft" width="148"] Dr. Bashir[/caption]
Riyaz Bashir MD, FACC, RVT
Professor of Medicine
Director, Vascular and Endovascular Medicine
Department of Medicine
Division of Cardiovascular Diseases
Temple University Hospital
Philadelphia, PA 19140
MedicalResearch.com: What is the background for this study?
Response: The use of inferior vena cava filters (IVCF) has been increasing in the United States (US) despite uncertainty about the effectiveness of IVCFs in reducing venous thromboembolism (VTE)-associated morbidity and mortality. Prompted by the report of high prevalence of fracture and embolization of Bard IVCFs, the US Food and Drug Administration (FDA) issued a device safety warning on August 9th 2010.
In this study, we evaluated national trends of IVCF placement in the US between 2005 and 2014 using the National Inpatient Sample database. The authors found that there was a 29% reduction in filter use following the 2010 FDA advisory, even though the rates of VTE-related hospitalizations remained unchanged.
11 Jul EKGs of Low Risk Patients Remain Common and Associated With More Cardiac Testing
MedicalResearch.com Interview with: Sacha Bhatia, MD, MBA, FRCPC Scientist, Women's College Research Institute Director, Women’s College Hospital Institute for Health System Solutions and Virtual Care Cardiologist, Women's College Hospital and University Health Network Canada MedicalResearch.com: What is the background for this study? What are the main findings? Response: The USPSTF recommends against screening with resting electrocardiography (ECG) for the prediction of coronary heart disease (CHD) events in asymptomatic adults at low risk for CHD events. We conducted a retrospective cohort study of the frequency of resting ECGs in low risk patients within 30 days of an annual health exam. We found that 21.5% of low risk patients in Ontario, Canada had a ECG, with significant variation among primary care physicians (1.8% to 76.1%). Moreover, low risk patients who had a ECG were five times more likely to receive another cardiac test or cardiology consultation than those that did not receive an ECG. At one year the rate of mortality, cardiac hospitalizations and revascularization was <0.5% in each group.11 Jul Fewer Fractures With Fosamax (Alendronate) For Patients on Steroids
MedicalResearch.com Interview with: [caption id="attachment_35801" align="alignleft" width="193"] Prof. Lorentzon[/caption]
Mattias Lorentzon, PhD
Professor, Senior Physician
Head of Geriatric Medicine, Institute of Medicine, Sahlgrenska Academy
Sahlgrenska University Hospital, Mölndal
Mölndal, Sweden
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: It was previously known that alendronate reduces the risk of vertebral fractures in patients using oral glucocorticoids, but there were no studies regarding hip fractures, which are the most severe osteoporotic fractures, often resulting in disability and mortality.
We found that older patients prescribed alendronate after starting medium to high doses of oral prednisolone had a much lower risk of hip fracture than patients not taking alendronate.
10 Jul BLISS – Baby Led Introduction To Solids – May Make Feeding Less Fussy
MedicalResearch.com Interview with: Dr. Anne-Louise M. Heath and Professor Rachael Taylor Co-Principal Investigators for the BLISS study. MedicalResearch.com: What is the background for this study? What are the main findings? Response: Conventional approaches to complementary feeding generally advise parents to spoon-feed their infant pureed foods, gradually progressing to greater variety and texture so that by the time the infant is one year of age, they are eating more or less what the family does. Baby-led weaning (BLW) is an alternative approach where the infants feeds themselves right from the start of complementary feeding. Because children of this age cannot use utensils, this means hand-held foods are necessary. Advocates of BLW suggest that children have a lower risk of obesity because they remain in control of their own food intake, but research examining this issue directly is scarce. Health professionals have also expressed concern that BLW might put the infant at increased risk of iron deficiency (parents might avoid red meat for fear of the infant choking, and iron-fortified cereals are not easy for the infant to feed themselves), growth faltering (if only low energy foods are offered) and choking (from the infant feeding themselves ‘whole’ foods). Our study therefore examined a version of BLW that had been modified to address these issues (called BLISS - a Baby-Led Introduction to SolidS). Two hundred families took part in our 2-year intervention, with half following traditional feeding practices and half receiving guidance and support to follow our BLISS approach. We found that BLISS children were not less likely to be overweight than those following traditional feeding practices, nor was growth faltering an issue. BLISS child ate about the same amount of food as control children, and their ability to eat to appetite was not different either. However, it seems that children following a baby-led approach to complementary feeding are less fussy about food, and have a healthier attitude to food, which might make a difference to their health long term.07 Jul Clinical Perineural Invasion of Cutaneous SCC May Warrant Adjuvant Treatment
Posted at 17:54h
in Author Interviews, Brigham & Women's - Harvard, Cancer Research, Dermatology, JAMA
MedicalResearch.com Interview with:
Dr. Chrysalyne D. Schmults, MD, MSCE
Associate Professor of Dermatology, Harvard Medical School
Director, Mohs and Dermatologic Surgery Center and
Mr. Pritesh S. Karia, MPH
Department of Epidemiology
Johns Hopkins Bloomberg School of Public Health, Baltimore, Maryland
Department of Dermatology
Brigham and Women's Faulkner Hospital
Harvard Medical School, Boston, Massachusetts
Jamaica Plain, MA 02130-3446
MedicalResearch.com: What is the background for this study?
Response: Perineural nerve invasion (PNI) is a well-recognized risk factor for poor prognosis in patients with cutaneous squamous cell carcinoma (CSCC). Most cases of CSCC with PNI are identified on histologic examination at the time of surgery and the patient has no clinical symptoms or radiologic evidence of PNI. These cases are classified as incidental PNI (IPNI). However, some patients with PNI present with clinical symptoms and/or radiologic evidence of PNI. These cases are classified as clinical PNI (CPNI). A few studies have shown differences in disease-related outcomes between CSCC patients with IPNI and CPNI but consensus regarding adjuvant treatment and detailed guidelines on follow-up schedules have not yet materialized.
06 Jul Google Searches Valuable Source of Cancer Incidence and Mortality Data
Posted at 23:37h
in Author Interviews, Cancer Research, Dermatology, JAMA, University of Pennsylvania
MedicalResearch.com Interview with:
[caption id="attachment_35759" align="alignleft" width="200"] Dr. Weher[/caption]
Mackenzie R. Wehner, MD, MPhil
Department of Dermatology
University of Pennsylvania
Philadelphia, PA
MedicalResearch.com: What is the background for this study?
Response: For some diseases, we have national registries, in which information about every person with that disease is entered for research purposes. For other diseases, unfortunately, we do not have such registries. There are growing opportunities to use information like internet searches to better understand behaviors and diseases, however. Our study was a proof-of-concept: we aimed to find out whether internet searches for diseases correlated with known incidence (how many people are diagnosed with the disease) and mortality (how many people die of the disease) rates. E.g. does the number of people who searched 'lung cancer' online correlate with the number of people who we know were diagnosed with or who died of lung cancer during that same time period? This is important to know if researchers in the future want to use internet search data for diseases where we lack registry information.
06 Jul Study Helps Explains Why Dopamine Drugs Not Effective For Depression
MedicalResearch.com Interview with: [caption id="attachment_35752" align="alignleft" width="144"] Dr. Rutledge[/caption]
Robb B. Rutledge, PhD
Max Planck University College London Centre for Computational Psychiatry
and Ageing Research
University College London
London, England
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Depression is associated with deficits in how the brain responds to rewards, something the neurotransmitter dopamine is strongly implicated in.
Dopamine represents what is called a reward prediction error, the difference between experienced and predicted reward. This error signal is used for learning. For example, if the outcome of a decision is better than expected, you can update your expectations using this error signal and you should expect more next time. Previous research has shown that depression reduces these signals in the brain when people are learning about the world around them. We designed a task where participants did not have to learn anything during the experiment and we found that in this situation reward prediction error signals were not affected by depression. The signals we measured in the ventral striatum, a brain area with a lot of input from the dopamine neurons, looked the same in depressed and non-depressed individuals. We also found that the emotional impacts of reward prediction errors were similar in depressed and non-depressed individuals when we eliminated the need for learning during the task in both the lab and using a smartphone experiment with 1833 participants.
06 Jul Effect of Depth and Duration of Cooling on Death or Disability at Age 18 Months Among Neonates With Hypoxic-Ischemic Encephalopathy
MedicalResearch.com Interview with: [caption id="attachment_35668" align="alignleft" width="150"] Dr. Shankaran[/caption]
Seetha Shankaran, M.D.
Professor, Neonatology
Wayne State University School of Medicine
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The study was performed because infants with moderate or severe hypoxic-ischemic encephalopathy (abnormal neurological exam within 6 hours of birth due to lack of blood and oxygen supply to the brain at birth) have rates of death or survival with disability that were still high in spite of current intensive care including hypothermia.
Whole-body hypothermia, cooling the infant for 72 hours at a depth of 33.5°C that was performed by the Neonatal Research Network funded by the Eunice Kennedy Shriver National Institute of Child Health and Human Development was the first trial of this therapy in the USA. We found that hypothermia therapy did decrease the rate of death or survival with disability from 62 to 44%. Since 44% is still high we wanted to see if longer cooling or deeper cooling or both would reduce this rate.
This was a randomized controlled clinical trial to examine whether longer cooling or deeper cooling or both reduced the rate of death or survival with disability among full term neonates with hypoxic-ischemic encephalopathy. The study lasted from October of 2010 to January 2016. 364 infants were enrolled. Neonates were randomly assigned to 4 groups of cooling therapy and the major findings were that neither longer cooling nor deeper cooling nor both were more superior to cooling for 72 hours at 33.5°C.
Our results were surprising because at the time we planned this study there were reports from animal model studies that longer/deeper cooling were more protective to the brain.
05 Jul Clinicians Multitask on Electronic Health Records 30% of Visit Time with Patients
MedicalResearch.com Interview with: [caption id="attachment_35660" align="alignleft" width="132"] Dr. Ratanawongsa[/caption]
Neda Ratanawongsa, MD, MPH
Associate Chief Health Informatics Officer for Ambulatory Services, San Francisco Health Network
Associate Professor, Division of General Internal Medicine
UCSF Center for Vulnerable Populations
Physician, Richard H. Fine People's Clinic (RHPC)
Zuckerberg San Francisco General Hospital
San Francisco, CA 94110
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: U.S. federal incentives allowed many safety net healthcare systems to afford fully functional electronic health record systems (EHRs). Although EHRs can help clinicians provide care to vulnerable populations, clinicians may struggle with managing the EHR workload, particularly in resource-limited settings. In addition, clinicians’ use of EHRs during clinic visits may affect how they communicate with patients.
There are two forms of EHR use during clinic visits. Clinicians can multitask, for example, by ordering laboratory tests while chatting with a patient about baseball. However, like distracted driving, using EHRs while talking with increases risks – in this case, the risk of errors in patient-provider communication or in the EHR task. Alternatively, clinicians can use EHRs in complete silence, which may be appropriate for high-risk tasks like prescribing insulin. However, silence during visits has been associated with lower patient satisfaction and less patient-centered communication.
So we studied how primary and specialty care clinicians used EHRs during visits with English- and Spanish-speaking patients in a safety net system with an EHR certified for Centers for Medicare & Medicaid Services meaningful use incentive programs. We found that multitasking EHR use was more common than silent EHR use (median of 30.5% vs. 4.6% of visit time). Focused patient-clinician talk comprised one-third of visit time.
We also examined the transitions into and out of silent EHR use. Sometimes clinicians explicitly stated a need to focus on the EHR, but at times, clinicians drifted into silence without warning. Patients played a role in breaking silent EHR use, either by introducing small talk or by bringing up their health concerns.
05 Jul Newer Insulin Formulation Reduces Risk of Hypoglycemia
MedicalResearch.com Interview with: [caption id="attachment_35738" align="alignleft" width="150"] Dr. Lane[/caption]
Wendy Lane MD
Director of Clinical Research
Mountain Diabetes and Endocrine Center
Asheville, NC
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The SWITCH1 trial was the first double blinded insulin trial to compare the rate of severe, nocturnal severe and symptomatic blood glucose-confirmed hypoglycemia between two basal insulins, insulin glargine U100 and insulin degludec U100, in patients with type 1 diabetes.
The trial design (double blinded crossover treat-to-target) eliminated any bias in the results, which showed clear-cut reductions in all categories of hypoglycemia with insulin degludec compared to insulin glargine.
Severe hypoglycemia has dangerous and greatly feared consequences including cognitive impairment, seizures, coma and death, and it is the main barrier to effective use of insulin in the treatment of type 1 diabetes. Insulin degludec, which was shown to reduce the risk of hypoglycemia compared to insulin glargine in the SWITCH1 trial, should be viewed by clinicians as an advancement in insulin therapy which will increase its safety and improve the quality of life of our patients with type 1 diabetes.
04 Jul More Adults Walking For Transportation or Leisure, But Demographic Deparities Remain
MedicalResearch.com Interview with: [caption id="attachment_35687" align="alignleft" width="200"] Dr. Ussery[/caption]
Emily Neusel Ussery, MPH PhD
Epidemiologist, Physical Activity and Health Branch
CDC
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Walking is an easy way for most people to start and maintain a physically active lifestyle. Step It Up! The Surgeon General’s Call to Action to Promote Walking and Walkable Communities identifies walking as an important public health strategy to increase physical activity levels in the U.S. A previous report found that the percentage of adults who reported walking for transportation or leisure increased by 6 percentage points between 2005 and 2010, but it is unknown if this increase has continued. This report examined trends in the proportion of U.S. adults who reported walking for transportation or leisure for at least one 10-minute period in the past week, using nationally representative data from the 2005, 2010, and 2015 National Health Interview Surveys. We also examined differences in walking trends by sociodemographic characteristics. If you take walking seriously, make sure you invest in some custom boots to make sure you don't damage your feet. For those who need to transport larger items while walking isn't an option, utilizing a Large Item Courier service can help ensure safe and efficient delivery.
04 Jul JAMA Study Finds Radiofrequency For Treating Chronic Low Back Pain
MedicalResearch.com Interview with: [caption id="attachment_35689" align="alignleft" width="133"] Dr. Maas[/caption]
Esther Maas, PhD
Postdoctoral Research Fellow
Partnership for Work, Health and Safety
School of Population and Public Health
University of British Columbia
Vancouver, BC
MedicalResearch.com: What is the background for this study?
Esther Maas, PhD Chronic low back pain causes more disability than any other condition, and has major social and economic consequences. Radiofrequency denervation is a commonly used treatment in pain clinics for a subgroup of patients with chronic low back pain resulting from anatomical structures such as facet joints, sacroiliac joint and intervertebral disc. Radiofrequency denervation uses an electric current that damages the innervating nerve of the painful structure. Despite its frequent application, until now, there was only very low quality and conflicting evidence for its effectiveness. The aim of this study was to establish whether radiofrequency denervation in addition to a standardized exercise program is more effective than the standardized exercise program alone in the selected subgroup of patients with chronic low back pain.
04 Jul How Well Do Personal Sound Amplifiers Compare To Conventional Hearing Aides?
MedicalResearch.com Interview with: [caption id="attachment_35679" align="alignleft" width="200"] Dr. Nicholas Reed[/caption]
Nicholas S. Reed, AuD
Instructor | Department of Otolaryngology-Head/Neck Surgery
PhD Candidate | Graduate Training Program in Clinical Investigation
Center on Aging and Health
Johns Hopkins University School of Medicine
Johns Hopkins University Bloomberg School of Public Health
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Hearing Aids are medical devices regulated by the FDA which must be purchased through a licensed individual while personal sound amplification products (PSAPs) are essentially unregulated devices some of which can manipulate and increase sound similar to a hearing aid but cannot market themselves are devices for hearing loss. PSAPs can be purchased online or in the back of a store and are generally less expensive than hearing aids.
We aimed to explore a select group of PSAPs to see if they helped someone with mild to moderate hearing loss improve speech understanding (i.e. ability to repeat back sentences) in the presence of mild background noise (think a lunch crowd at a restaurant) as well as a hearing aid. We selected four PSAP devices that were technologically strong (i.e. meet many standards a hearing aid might be asked to meet) and one PSAP that was technologically fairly poor (i.e. lots of sound distortion) after an in-house electroacoustic analysis of devices. Our hearing aid was selected because it was a popular choice at a university audiology clinic. Forty-two people completed the speech testing unaided (i.e. with no device) and then with each of the five PSAPs and one hearing aid (order of devices was randomized).
We looked at improvement with the devices from unaided. We found that some PSAPs help people understand speech about as well as a hearing aid in this controlled environment while one PSAP actually hindered participants’ ability to understand speech due to sound distortion – imagine how difficult it can be when listening on a poor cell phone signal.
29 Jun TAVR Linked To Improved Quality of Life Even After Two Years
MedicalResearch.com Interview with: [caption id="attachment_35663" align="alignleft" width="171"] Dr. Baron[/caption]
Suzanne J. Baron, MD, MSc
Saint Luke’s Mid America Heart Institute
School of Medicine
University of Missouri, Kansas City
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Transcatheter Aortic Valve Replacement (TAVR) has emerged as a viable treatment option for patients with severe aortic stenosis in patients at high and intermediate surgical risk. Prior studies have demonstrated that both TAVR and surgical AVR (SAVR) results in substantial quality of life benefit in patients at high surgical risk.
Whether these results applied to an intermediate risk population was unknown and so we performed a prospective study alongside the PARTNER 2A trial to compare both short- and long-term health status outcomes in intermediate-risk patients with AS treated with either TAVR or SAVR. The analysis included 1833 patients (950 TAVR, 833 SAVR), who were evaluated at 1 month, 1 year and 2 years post procedure. By 1 month, quality of life had improved in both the TAVR and SAVR groups, although the gain was significantly greater in patients treated with TAVR via the transfemoral approach as opposed to patients treated with SAVR or with TAVR via the transthoracic approach (i.e. direct aortic access or transapical access). At 1 and 2 years, both TAVR (via either approach) and SAVR were associated with similarly large, clinically meaningful improvements from baseline in both disease-specific and generic health status scales at 2 years.
28 Jun Electroacupuncture Reduced Leakage in Stress Urinary Incontinence
MedicalResearch.com Interview with: Baoyan Liu, MD Guang’an Men Hospital China Academy of Chinese Medical Sciences Beijing, China [caption id="attachment_35600" align="alignleft" width="200"]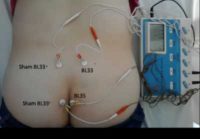 Patient with Electroacupuncture[/caption]
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The prevalence of stress urinary incontinence(SUI) is as high as 49% and varies according to the population studied and the definition of stress urinary incontinence.
SUI causes psychological burden, affects relationships, lowers physical productivity, and decreases quality of life in women. Yet, few effective therapies are available for treating stress urinary incontinence.
In this randomized clinical trial that included 504 women, the mean decrease in urine leakage, measured by the 1-hour pad test from baseline to week 6, was 9.9 g with
electroacupuncture vs 2.6 g with sham electroacupuncture, a significant difference.
27 Jun Limited Benefit To Expedited Stress Testing of Chest Pain In ER Patients
MedicalResearch.com Interview with: Alexander Sandhu, MD MS Cardiology Fellow Stanford University MedicalResearch.com: What is the background for this study? What are the main findings? Response: Millions of patients present to the emergency department with chest pain but most do not have lab or EKG findings that indicate the patient is having a heart attack. In patients without signs of a heart attack, stress testing is frequently used to determine the need for further workup and treatment. However, there is limited evidence regarding the benefit of stress testing in these patients. We evaluated how cardiac testing - stress testing and coronary angiography - in these low-risk patients was associated with clinical outcomes. We used a statistical approach that took advantage of the fact that testing is more available on weekdays than weekends. We found that testing was associated with more angiography and revascularization (coronary stenting or coronary artery bypass surgery) but was not associated with a reduction in future heart attacks.22 Jun USPSTF Recommends Children and Adolescents Be Screened For Obesity
MedicalResearch.com Interview with: [caption id="attachment_35533" align="alignleft" width="140"] Dr. Grossman[/caption]
David C. Grossman, M.D., M.P.H.
US Preventive Services Task Force Chair
Senior Investigator, Kaiser Permanente Washington Health Research Institute
Senior Associate Medical Director, Market Strategy & Public Policy
Kaiser Permanente Washington
Physician, Washington Permanente Medical Group, Pediatrics
MedicalResearch.com: What is the background for this recommendation?
Response: Recognizing that obesity is a nation-wide health problem, affecting approximately 17% of 2-to 19-year-old children and adolescents in the U.S., the Task Force finalized its recommendation on screening for obesity in children and adolescents and the benefits and harms of weight management interventions. The Task Force found sufficient evidence to recommend screening for obesity in children and adolescents age 6 years and older and then offering or referring those who are found to be obese comprehensive, intensive behavioral interventions to manage their weight and improve overall health.
MedicalResearch.com: What are the potential benefits and harms of early screening and intervention for obesity in children?
Response: The Task Force found that intensive behavioral interventions for children and adolescents who have obesity can result in benefits of improvement in weight status for up to 12 months’ post-intervention. Additionally, the evidence indicated very little harm from screening and comprehensive, intensive behavioral interventions. This is due to likely minimal harms of using BMI (body mass index), the absence of reported harms of behavioral interventions, and the noninvasive nature of the programs.
19 Jun Fecal Testing Better At Detecting Colon Cancer Than Advanced Atypical Changes
MedicalResearch.com Interview with: [caption id="attachment_35515" align="alignleft" width="160"] Dr. Katsoula[/caption]
Anastasia Katsoula, MD MSc
Aristotle University of Thessaloniki
Greece
MedicalResearch.com: What is the background for this study?
Response: Early detection of colorectal cancer (CRC) has proven to be effective in reduction of cancer-related mortality. Fecal immunochemical testing (FIT) has been recently advocated for population-based screening for CRC in average-risk individuals due to its high accuracy and potential for adherence, based on results from previous systematic reviews and meta-analyses in average-risk populations. However, the potential role of FIT for screening of subjects at increased risk for CRC has not yet been elucidated, hence colonoscopy is currently the only recommended screening option for subjects at increased risk of CRC. We performed a systematic review and meta-analysis to explore the diagnostic accuracy of FIT for CRC or advanced neoplasia (AN) in patientswith personal or familial history of CRC, using colonoscopy as the reference standard.
19 Jun Most Youth With Opioid Disorders Do Not Receive Medications For Addiction
MedicalResearch.com Interview with: [caption id="attachment_35432" align="alignleft" width="154"] Dr. Hadland[/caption]
Scott Hadland, MD, MPH, MS
Youth Addiction Specialist
Assistant Professor of Pediatrics
Boston University School of Medicine
Director, Urban Health and Advocacy Track, Boston Children’s Hospital and Boston Medical Center
Associate Program Director, Boston Combined Residency Program in Pediatrics, Boston Medical Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Almost no data have been available on this topic to date. A recent study showed that teens in subspecialty treatment for opioid addiction were significantly less likely than adults to receive a medication. Our study was the first to comprehensively look across the health care system, including looking at adolescents and young adults diagnosed with opioid use disorder in outpatient clinics, emergency departments, and inpatient hospitals.
We had three important findings. First, looking at a large sample of 9.7 million adolescents and young adults between the age of 13 and 25 years, we found that the number of youth diagnosed with opioid use disorder increased six-fold from 2001 to 2014. This is perhaps not surprising given the national opioid crisis we know to be occurring.
Second, we found that only a minority of youth (1 in 4) received buprenorphine or naltrexone, the two medications available for opioid addiction that can be prescribed in usual medical settings. These two medications are evidence-based and their use is recommended by the American Academy of Pediatrics. Utilizing them is critical to ensure that we offer effective treatment early in the life course of addiction, which can help prevent the long-term harms of addiction.
Third, we found significant differences in who received medications. Whereas approximately 1 in 3 young adults in our study received a medication, only 1 in 10 of the 16- and 17-year-olds we studied received one, and among adolescents under 15 years of age, 1 in 67 received a medication. Females were less likely than males to receive medications, as were black youth and Hispanic youth relative to white youth.
17 Jun Volunteers Plus Free Hearing Aids Can Supply Adequate Auditory Care
MedicalResearch.com Interview with: Aileen Wertz, MD Otolaryngology - Head and Neck Surgery University of Michigan MedicalResearch.com: What is the background for this study? What are the main findings? Response: The key finding of this study is: free, comprehensive audiologic care, including hearing aids and fitting, is feasible within a well-established free clinic model. We found that donated hearing aids and volunteer health care providers were able to run the clinic and that 20 patients have thus far been fit with hearing aids.15 Jun Comparison of NOACs with Warfarin In Atrial Fibrillation Patients With Single Stroke Risk Factor
MedicalResearch.com Interview with: [caption id="attachment_35355" align="alignleft" width="110"] Dr. Lip[/caption]
Gregory Y. H. Lip, MD
Professor of Cardiovascular Medicine
University of Birmingham
Adjunct Professor of Cardiovascular Sciences, Thrombosis Research Unit, Aalborg University, Denmark
National Institute for Health Research (NIHR) Senior Investigator.
Visiting Professor of Haemostasis Thrombosis & Vascular Sciences, Aston University, Birmingham, UK
Institute of Cardiovascular Sciences
City Hospital
Birmingham England UK
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The randomized clinical trials comparing non-Vitamin K antagonist oral anticoagulants (NOACs) vs warfarin largely focused on recruitment of high risk atrial fibrillation(AF) patients with >2 stroke risk factors, with only the trials testing dabigatran or apixaban including a minority of patients with 1 stroke risk factor.
Despite this, regulatory approvals of all NOACs have been for stroke prevention in AF patients with ≥1 stroke risk factors. No difference between NOACs compared to warfarin in risk of ischemic stroke/systemic embolism, was seen but for ‘any bleeding’, this was lower for apixaban and dabigatran compared to warfarin.
15 Jun Extended-Release Amantadine Reduces Dyskinesia in Parkinson’s Disease
MedicalResearch.com Interview with: Rajesh Pahwa MD Department of Neurology University of Kansas Medical Center, Kansas City, KS, MedicalResearch.com: What is the background for this study? What are the main findings? Response: Dyskinesia are one of the major unmet needs in Parkinson Disease patients. At the present time there are no approved medication for dyskinesia, however immediate release amantadine is used in PD patients with dyskinesia. ADS-5102 is a long acting, extended release capsule formulation of amantadine HCl administered once daily at bedtime. This study investigated the safety, efficacy and tolerability of ADS-5102 in Parkinson’s disease (PD) patients with levodopa-induced dyskinesia. This was a randomized, double-blind, placebo-controlled study of Parkinson’s disease patients with levodopa-induced dyskinesia. In total, 126 patients were randomized to placebo or 274 mg ADS-5102 administered orally at bedtime. ADS-5102 was associated with a significant reduction in dyskinesia at 12 weeks compared with placebo, as measured by the mean change in Unified Dyskinesia Rating Scale (treatment difference, –7.9; P =.0009). OFF time was significantly reduced in ADS-5102 patients compared to placebo (treatment difference -0.9 hours, p=.017).14 Jun 20% of Hospitalized Patients Receiving Antibiotics Experience Side Effects
MedicalResearch.com Interview with: Dr. Pranita D. Tamma
Assistant Professor of Pediatrics
Director, Pediatric Antimicrobial Stewardship Program
The Johns Hopkins University School of Medicine
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: A study examining the impact of antibiotics prescribed for nearly 1500 adult patients admitted to The Johns Hopkins Hospital found that adverse side effects occurred in a fifth of them, and that nearly a fifth of those side effects occurred in patients who didn’t need antibiotics in the first place.
In the study, the researchers evaluated the electronic medical records of 1488 adults admitted to the general medicine services at The Johns Hopkins Hospital between September 2013 and June 2014. The patients were admitted for reasons ranging from trauma to chronic disease, but all received at least 24 hours of antibiotic treatment.
The researchers followed patients for 30 days after hospital discharge to evaluate for the development of antibiotic-associated adverse events. To determine the likelihood that an adverse reaction was most likely due to antibiotics and to identify how many adverse reactions could be avoided by eliminating unnecessary antibiotic use, two infectious disease clinicians reviewed all of the data.
14 Jun More Education Means Lowers Cardiovascular Risk, Regardless of Income
MedicalResearch.com Interview with: [caption id="attachment_35213" align="alignleft" width="133"] Dr. Kubota[/caption]
Yasuhiko Kubota, MD, MPH
Visiting Scholar
Division of Epidemiology and Community Health
School of Public Health
University of Minnesota, Minneapolis, MN
MedicalResearch.com: What is the background for this study?
Response: Educational inequality is one of the most important socioeconomic factors contributing to cardiovascular disease. Since education is usually completed by young adulthood, educational inequality may affect risk of cardiovascular disease early in the life course. We thought it would be useful to calculate the lifetime risk of cardiovascular disease according to educational levels in order to increase public awareness of the importance of education.
Thus, our aim was to evaluate the association of educational attainment with cardiovascular disease risk by estimating the lifetime risks of cardiovascular disease using a US. biracial cohort. Furthermore, we also assessed how other important socioeconomic factors were related to the association of educational attainment with lifetime risk of cardiovascular disease.
13 Jun Dramatic Increase in ACL Injuries and Surgery in Adolescent Girls
Posted at 11:32h
in Author Interviews, Exercise - Fitness, Gender Differences, JAMA, Pediatrics, Surgical Research
MedicalResearch.com Interview with:
[caption id="attachment_35287" align="alignleft" width="200"] Mackenzie Herzog[/caption]
Mackenzie M. Herzog, MPH
PhD Candidate, Injury Epidemiology
The University of North Carolina at Chapel Hill
MedicalResearch.com: What is the background for this study?
Response: In 1999, a study by Arendt et al. reported that women were more likely to tear their ACL than men while playing the same sport. Since then, numerous studies have investigated this sex difference in ACL injury, and many prevention programs targeting youth athletes have been developed and tested. Although randomized trials have demonstrated the value of injury prevention programs in reducing the risk of ACL injury, the overall impact of these programs has not been examined in the general population. Our study investigated the net impact of research and prevention efforts over nearly 20 years in reducing ACL injuries by assessing time trends of ACL reconstruction, a consequence of ACL injury, among commercially-insured individuals in the United States.