
23 Jan Unnecessary Routine Preoperative Cataract Testing Costs Medicare Millions
Posted at 12:56h
in Author Interviews, Cost of Health Care, JAMA, Ophthalmology, Surgical Research, UCSF
MedicalResearch.com Interview with:
Catherine L. Chen, MD, MPH
Assistant Professor
UCSF Department of Anesthesia & Perioperative Care
MedicalResearch.com: What is the background for this study? What are the main findings?
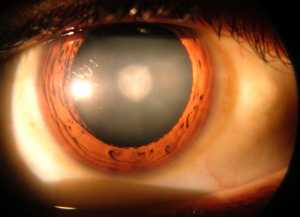
Response: Routine preoperative medical testing (such as common laboratory tests looking at a patient's blood cell counts and kidney function, or cardiac tests like an EKG) are not recommended in patients undergoing cataract surgery, but these tests still occur quite frequently among Medicare cataract surgery patients because these patients tend to be older and sicker than the general population. In the past, researchers have used a 30-day window counting backwards from the date of surgery to determine whether a given test should be categorized as a routine preoperative test. However, we know that testing often takes place outside this window and therefore, the frequency and cost of routine preoperative medical testing has generally been underreported.
In our study, we used a new method to figure out how to determine the start of the routine preoperative testing period. In cataract patients, ocular biometry is a diagnostic test that is performed in anticipation of cataract surgery, and this test is only performed in cataract patients who will be having cataract surgery in the near future. For each patient, we calculated the elapsed time between the ocular biometry and cataract surgery dates to get a better idea of when to start looking for unnecessary routine preoperative testing. Our goal was to identify all the routine preoperative medical testing that occurs once the decision has been made to operate and better estimate the cost to Medicare of this unnecessary testing.
In a previous study that we published in the New England Journal of Medicine, we reported a significant spike in the rate of routine preoperative medical testing that occurs in the 30 days before surgery compared to the baseline rate of testing. In our current study, we discovered that there is a second spike in testing that occurs in the 30 days after ocular biometry. In fact, even if you exclude the testing that takes place during the 30 days before surgery, there is still a 41% increase in testing rates during the interval between ocular biometry and cataract surgery over the baseline rate of testing. In addition, we found that the cost of routine preoperative testing was 47% higher when looking at the entire biometry to surgery timeframe compared to testing that occurs just in the 30 days before surgery.
We estimate that the cost to Medicare of all of this unnecessary testing approaches $45.4 million annually.














 Dr. Jacobs[/caption]
Dr. Lisa K. Jacobs MD
Johns Hopkins School of Medicine
Baltimore, Maryland
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Breast preservation is the preferred treatment for many women diagnosed with breast cancer. The most common question that a patient will ask after the surgery is, “Did you get it all?” In the ideal case, this is accomplished in a single outpatient surgery with very good cosmetic results. In our study, Beyond the Margins-Economic Costs and Complications Associated with Repeated Breast-Conserving Surgeries we evaluated the detrimental effects of an unsuccessful initial surgery due to positive surgical margins. Using private insurance claims data, we found that 16% of patients planning breast preservation required a second breast-conserving surgery and an additional 7% converted to mastectomy. Of those patients that required additional surgery there was a 56% ($16,072) increase in cost and a 48% increase in complications. Those complications include infection, hematoma, seroma, and fat necrosis. This study demonstrates that repeated surgery has not only cosmetic consequences, but also has financial implications and increased risk.

