
Author: Marie Benz MD FAAD
27 Jul Cross-Sex Hormone Therapy Associated With Medical Risks and Psychosocial Benefits in Transgender Patients
Posted at 22:15h
in Annals Internal Medicine, Author Interviews, Brigham & Women's - Harvard, Hormone Therapy, Sexual Health, Testosterone
MedicalResearch.com Interview with:
[caption id="attachment_34884" align="alignleft" width="160"] Dr. Streed[/caption]
Carl G Streed Jr. M.D.
Pronouns: he, him, his, himself
Fellow, Division General Internal Medicine & Primary Care
Brigham & Women’s Hospital
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Recent reports estimate that 0.6% of adults in the United States, or approximately 1.4 million persons, identify as transgender. Despite gains in rights and media attention, the reality is that transgender persons experience health disparities, and a dearth of research and evidence-based guidelines remains regarding their specific health needs. The lack of research to characterize cardiovascular disease (CVD) and CVD risk factors in transgender populations receiving cross-sex hormone therapy (CSHT) limits appropriate primary and specialty care. As with hormone therapy in cisgender persons (that is, those whose sex assigned at birth aligns with their gender identity), existing research in transgender populations suggests that CVD risk factors are altered by CSHT.
26 Jul Mobile Message Delivery Can Help Parents Learn Safe Infant Sleep Practices
MedicalResearch.com Interview with: [caption id="attachment_36168" align="alignleft" width="147"] Dr. Moon[/caption]
Rachel Y. Moon, M.D.
Division Head, General Pediatrics
Professor of Pediatrics
University of Virginia School of Medicine
Charlottesville, VA 22908
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Approximately 3500 babies die suddenly and unexpectedly during sleep in the US every year. Even though there are safe sleep recommendations, many parents do not follow them because of misinformation or misconceptions.
Therefore we tested 2 complementary interventions to promote infant safe sleep practices. The first was a nursing quality improvement intervention aimed at ensuring that mothers would hear key messages and that there was appropriate role modeling of safe sleep practices by hospital personnel.
The second was a mobile health intervention, in which mothers received videos and text messages or emails with safe sleep information during the baby's first two months of life. We randomized mothers to receive either the safe sleep interventions or breast-feeding interventions (the control interventions). Mothers who received the mobile health intervention reported statistically significantly higher rates of placing their babies on their back, room sharing without bed sharing, no soft bedding use, and pacifier use, compared with mothers who received a control intervention. Although the nursing quality improvement intervention did not influence infant safe sleep practices, there was an interaction such that mothers who received both the safe sleep nursing quality improvement intervention and the safe sleep mobile health intervention had the highest rates of placing their babies on the back.
26 Jul Disadvantaged Neighborhoods Help Explain Some Of Alzheimer’s Disease Racial Disparities
MedicalResearch.com Interview with: [caption id="attachment_36164" align="alignleft" width="125"] Dr. Amy Kind[/caption]
Amy Kind, M.D., Ph.D.
Associate Professor, Division of Geriatrics
Director, Department of Medicine Health Services and Care Research Program
University of Wisconsin School of Medicine and Public Health and
Associate Director- Clinical
Geriatrics Research, Education and Clinical Center (GRECC)
William S. Middleton Veteran’s Affairs Hospital
MedicalResearch.com: What is the background for this study? What are the main findings?
Background: Dementia due to Alzheimer’s Disease (AD) disproportionately impacts racial/ethnic minorities and the socioeconomically disadvantaged—populations often exposed to neighborhood disadvantage. Neighborhood disadvantage is associated with education, health behaviors and mortality. Health improves with moving to less disadvantaged neighborhoods (Ludwig, Science 2012). Although studies have linked neighborhood disadvantage to diseases like diabetes and cancer, little is known about its effect on development of dementia.
Objective: To examine the association between neighborhood disadvantage, baseline cognition, and CSF biomarkers of Alzheimer’s Disease among participants in the WRAP study, comprising a cohort of late-middle-aged adults enriched for parental family history of AD.
Methods: We created and validated neighborhood-level quantifications of socioeconomic contextual disadvantage for the full US—over 34 million Zip+4 codes—employing the latest American Community Survey and Census data. This metric--the Area Deprivation Index (ADI)--incorporates poverty, education, housing and employment indicators; predicts disparity-related health outcomes; and is employed by Maryland and Medicare through our provision. We used standard techniques to geocode all WRAP subjects with a documented address (N= 1479). WRAP participants were ranked into deciles of neighborhood disadvantage, by ADI. Baseline cognitive function (indexed by factor scores) and CSF biomarker outcomes for levels of Aβ42 and P-tau181 (n=153 with CSF samples) were examined by neighborhood disadvantage decile.
26 Jul Dementia Care Management Improved Quality of Life For Both Caregivers and Patients With Dementia
MedicalResearch.com Interview with: [caption id="attachment_36157" align="alignleft" width="144"] Dr. Thyrian[/caption]
Jochen René Thyrian, PhD
German Center for Neurodegenerative Diseases (DZNE)
Greifswald, Germany
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Dementia presents a challenge to the health care systems worldwide. People with dementia (PWD) need comprehensive medical, nursing, psychological and social support to delay the progression of disease and sustain autonomy and social inclusion. Evidence-based interventions alleviate the burden of disease for PwD and their caregivers, as no curative treatment is currently available. Involving caregivers is important because they provide the largest proportion of care for PwD. General physicians in residency have been identified as the first point of contact for PwD and is thus a promising setting for identification, comprehensive needs assessment and initiating dementia-specific treatment and care.
In this study we tested the effectiveness and safety of a model of collaborative care, Dementia Care Management (DCM) on patient-oriented outcomes in n=634 people screened positive for dementia in primary care. DCM is provided by specifically trained nurses, supported by a computerized intervention management system, in close cooperation with the treating physician at the people´s homes. Recommendations for improving treatment and care were based on a comprehensive needs assessment, discussed interprofessionally and their implementation monitored/ adjusted over the course of 6-12 months
26 Jul Sex Differences In Brain Structure of Boys and Girls With Conduct Disorder
MedicalResearch.com Interview with: [caption id="attachment_36153" align="alignleft" width="122"] Dr. Smaragdi[/caption]
Areti Smaragdi, PhD
University of Southampton
Southampton, UK
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Conduct Disorder is a psychiatric disorder that involves severe antisocial behavior – symptoms of the condition include behaviors like physical fighting, pathological lying, and serious theft. The disorder affects around 5% of school-aged children and adolescents, and is up to three times more common in boys than girls. Because of this, very little research has focused on the possible brain basis of the disorder in girls.
We used MRI scanning methods to measure the brain structure of 48 boys and 48 girls with Conduct Disorder (14-18 years old) and 52 boys and 52 girls without severe antisocial behavior. We found that boys and girls with Conduct Disorder had reduced thickness and more folding in the prefrontal cortex, an area at the front of the brain which is responsible for reward and punishment processing and helping us to control our emotions and impulses. In contrast, in some other areas such as the superior frontal gyrus, which is involved in short-term memory, boys and girls with Conduct Disorder showed structural changes in opposite directions (e.g., more versus less folding) compared with controls. This suggests that there are common abnormalities in brain structure in boys and girls with Conduct Disorder, but also some sex differences that might indicate that the causes of the disorder are partly different in boys and girls.
26 Jul Risk of Suicide Attempts With Methylphenidate Treatment for ADHD
MedicalResearch.com Interview with: Professor Ian Chi Kei Wong and Kenneth KC Man, Senior Research Assistant Department of Social Work and Social Administration, Faculty of Social Science Department of Pharmacology and Pharmacy, LKS Faculty of Medicine The University of Hong Kong MedicalResearch.com: What is the background for this study? What are the main findings? Response: Patients with attention-deficit/hyperactivity disorder (ADHD) are at higher risk of various mental health problems. Previous studies suggested that individuals with ADHD are having a higher chance of both attempted and completed suicide. Methylphenidate is a psychostimulant that is recommended for the treatment of ADHD. With the increasing usage of methylphenidate over the past decade, there are concerns about the safety of the medication, in particular, psychiatric adverse effects such as suicide attempt. The current study looked into over 25,000 patients aged 6 to 25 years in Hong Kong who were receiving methylphenidate in 2001 to 2015. Using the self-controlled case series design, in which the patients act as their own control, we found that the risk of suicide attempt was 6.5 fold higher during a 90-day period before methylphenidate was initiated, remained elevated 4-fold during the first 90 days of treatment, and returned to the normal level during ongoing treatment.26 Jul Obstructive Sleep Apnea May Accelerate Alzheimer’s Disease
MedicalResearch.com Interview with: [caption id="attachment_36148" align="alignleft" width="168"] Dr. Bubu[/caption]
O. Michael Bubu, M.D., M.P.H., C.P.H
Wheaton College
MedicalResearch.com: What is the background for this study?
- Obstructive Sleep Apnea (OSA) and Alzheimer’s disease (AD) are both chronic disease conditions that are highly prevalent, cause significant morbidity and mortality to those afflicted, and have an enormous socio-economic impact. Recent human and animal studies describe associations between Sleep Disordered Breathing (SDB) and Alzheimer's Disease (AD). However, whether OSA accelerates longitudinal increases in amyloid (Aβ) burden in MCI patients is presently unclear.
- In this study, we examined the effect of Obstructive Sleep Apnea (OSA) on longitudinal changes in brain amyloid deposition, and Alzheimer’s disease (AD) Cerebrospinal fluid (CSF) biomarkers including CSF beta-amyloid 42 peptide (Aβ-42), CSF TAU protein, CSF phosphorylated TAU protein (PTAU) in Cognitive Normal (CN), Mild Cognitive Impairment (MCI) and AD elderly. Brain amyloid (Aβ) burden, CSF Abeta42 and tau proteins are biomarkers (measurable substances whose presence are indicative) of AD-associated pathologic changes in the brain.
- Data from 1639 subjects (516 CN, 798 MCI and 325 AD, mean ages = 74.4 ± 5.8; 73.4 ± 7.4 and 75.1 ± 7.8 respectively), in the Alzheimer’s disease Neuroimaging Initiative (ADNI) database was used. OSA was self-reported and participants were labeled OSA positive, or OSA negative (mean ages = 72.3 ± 7.1; and 73.9 ± 7.3 respectively). Statistical analyses were conductedto examine whether OSA positive compared to OSA negative participants experienced significant differences in the rate of change of AD biomarkers over time (mean = 2.52 ± 0.51 years) in each group (CN, MCI and AD). Both OSA positives and negatives were similar in age, APOE e4 status, and history of cardiovascular disease. The final models controlled for sex, body mass index (BMI), and Continuous Pulmonary Airway Pressure (CPAP) use.
26 Jul Menopause Facilitates Transmission of Cognitive Resources To Grandchildren
MedicalResearch.com Interview with: [caption id="attachment_36141" align="alignleft" width="200"] “Grandmother” by Joe Shlabotnik[/caption]
Carla Aimé PhD
Institute of Evolutionary Sciences of Montpellier
France
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: In all human populations, regardless of environmental and socioeconomic conditions, menopause occurs in women well before the end of their expected lifespan. Conversely, extensive post-reproductive life-span is rare in other species; except in some cetaceans. Evolutionary theory predicts that menopause and extensive post-reproductive lifespan should emerge and persist in populations only if it is advantageous for gene transmission. Identifying this advantage is a long-standing issue, and some hypotheses has already been suggested by other researchers. However, testing these hypotheses about the emergence of menopause is difficult, in particular because menopause exists today in all human populations. It is thus not possible to measure in real life the evolutionary advantage related to menopause by comparing gene transmission of women who stop reproduction and women who don't stop reproduction. Here, we used computer simulations to overcome this difficulty by modeling the emergence of menopause in simulated human populations.
The main finding were the following :
- Physiological constraints are not required for menopause to emerge.
- The increasing cost of reproduction with age cannot explain menopause.
- Grandmothering is part of the process leading to menopause : stopping reproduction allow reallocating resources to existing children and grand-children, thus leading to increase gene transmission via increased fertility of children and survival of grand children
- Cognitive resources are also important. Indeed, cognitive abilities allow accumulation of skills and experience over the lifespan, thus providing an advantage for resource acquisition. These surplus resources can then be used to increase the number of offspring or be transmitted to existing offspring and grandoffspring. Stopping reproduction during aging allows allocating more resources to assist offspring and grandoffspring, thus increasing children’s fertility and grandchildren’s survival.
26 Jul Better Coordination Needed Between Hospital Physicians and Home Health Care Providers
MedicalResearch.com Interview with: [caption id="attachment_36137" align="alignleft" width="155"] Dr. Jones[/caption]
Christine D. Jones, MD, MS
Assistant professor
Director of Care Transitions, Hospital Medicine Group
University of Colorado School of Medicine
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The background for this study is that referrals to home health care at hospital discharge have increased over recent years. Yet, care coordination including information exchange and communication is often suboptimal between the hospital and home health care and may contribute to medication list discrepancies and even hospital readmissions.
We spoke with focus groups of home health nurses and our main findings were that improvements in key areas could care coordination after hospital discharge.
Specific solutions included:
1) Clearly defining the accountability for home health orders after discharge between hospitalists and primary care providers
2) Changes to insurance requirements that currently only allow physicians to write home health orders so that nurse practitioners and physician assistants can also write home health orders
3) Enhancing access for home health agencies to hospital electronic health records and direct phone lines
4) Encouraging liaisons from home health agencies to meet patients in the hospital to align clinician and patient expectations
5) Direct coordination between home health nurses and clinicians or pharmacists to resolve medication discrepancies
6) Ensuring that detailed information about cognitive and behavioral health is included in information provided to home health from referring hospitals
26 Jul Military Units With One Suicide Attempt At Greater Risk of Additional Attempts
MedicalResearch.com Interview with: [caption id="attachment_36118" align="alignleft" width="180"] Dr. Ursano[/caption]
Robert J. Ursano, M.D.
Professor of Psychiatry and Neuroscience
Director, Center for the Study of Traumatic Stress
Dept of Psychiatry
Uniformed Services University of the Health Sciences
Bethesda, MD
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: This study is part of the STARRS study- a study to identify risk and protective factors for suicide in US Army. Originally funded by NIMH it is not funded by DoD. It has been called the "Framingham study" for suicide and has been highly productive.
In this study we report that units with one suicide attempt are at increased risk of a second- indicating clustering of suicide attempts.
26 Jul Genetic Risk of Schizophrenia May Contribute to Cognitive Dysfunction
MedicalResearch.com Interview with: [caption id="attachment_36131" align="alignleft" width="180"] Dr. Smeland[/caption]
Olav B. Smeland MD PhD
Postdoctoral researcher
SFF NORMENT, KG Jepsen Centre for Psychosis Research, Division of Mental
Health and Addiction, Oslo University Hospital & Institute of Clinical Medicine
University of Oslo Oslo, Norway
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Schizophrenia is a severe mental disorder associated with widespread cognitive impairments. The cognitive deficits are associated with disabilities in social, economic and occupational functioning and lower quality of life among individuals with schizophrenia. Despite this, current treatment strategies largely fail to ameliorate these cognitive impairments.
To develop more efficient treatment strategies in schizophrenia, a better understanding of the disease mechanisms underlying cognitive deficits is needed. For a long time we have known that schizophrenia is heritable, and in recent years many schizophrenia risk genes have been identified. Moreover, several studies have indicated that genetic risk of schizophrenia may contribute to cognitive dysfunction.
In this study, we aimed to identify schizophrenia risk genes that also influence cognitive function. In a large international collaboration of researchers, we combined genome-wide association studies on schizophrenia and the cognitive traits of verbal-numerical reasoning, reaction time and general cognitive function. In total, we analyzed genetic data from more than 250.000 participants. We were able to identify 21 genetic variants shared between schizophrenia and cognitive traits. For 18 of these genetic variants, schizophrenia risk was associated with poorer cognitive performance.
26 Jul Once-Daily, Fixed-Dose Combination Tablet Containing Doravirine Achieved HIV-1 Viral Suppression
MedicalResearch.com Interview with: [caption id="attachment_36123" align="alignleft" width="142"] Dr. Squires[/caption]
Dr. Kathleen Squires MD
Professor and Director of Infectious Diseases
Thomas Jefferson University
Philadelphia, PA
MedicalResearch.com: What is the background for this study? What are the main findings?
- The pivotal Phase 3 DRIVE-AHEAD study evaluated the safety and efficacy of a once-daily, single tablet, fixed-dose combination containing doravirine, an investigational non-nucleoside reverse transcriptase inhibitor (NNRTI) for the treatment of HIV-1 infection, compared to a fixed-dose combination containing efavirenz.
- After 48 weeks of treatment, 84 percent of the 364 treatment-naïve patients taking once-daily DOR/3TC/TDF achieved levels of HIV-1 RNA <50 copies/mL compared to 81 percent of the 364 patients taking once-daily EFV/FTC/TDF, with an estimated treatment difference of 3.5 percent.
- Increases in mean CD4+ T-cell counts from baseline for the DOR/3TC/TDF and EFV/FTC/TDF groups were 198 and 188 cells/mm3, respectively, with an estimated treatment difference of 10.1.
- In addition, comparable efficacy was observed across both treatment groups among individuals with high viral load (HIV-1 RNA >100,000 copies/mL) at baseline, which consisted of 69 patients in the DOR/3TC/TDF group and 73 patients in the EFV/FTC/TDF group (Observed Failure approach).
- Of those patients with a high viral load (HIV-1 RNA >100,000 copies/mL) at baseline, 81 percent in the DOR/3TC/TDF group and 81 percent in the EFV/FTC/TDF group achieved the study’s primary endpoint of <50 copies/mL of HIV-1 RNA, with a treatment difference of 1.0 percent.
- The study also met its primary safety endpoint, showing that treatment with DOR/3TC/TDF resulted in fewer patients reporting events of several pre-specified neuropsychiatric adverse events compared to EFV/FTC/TDF by Week 48, including dizziness (8.8 percent versus 37.1 percent); sleep disorders and disturbances (12.1 percent versus 25.5 percent); and inability to think clearly or concentrate (4.4 percent versus 8.2 percent).
25 Jul ONCEMRK Study: Once Daily Raltegravir In Combination With Other Antivirals Effective For Some HIV Patients
MedicalResearch.com Interview with: [caption id="attachment_36099" align="alignleft" width="141"] Dr. Pedro Cah[/caption]
Dr. Pedro Cahn
Chief of the infectious disease unit at Juan A. Fernandez Hospital
Buenos Aires, Argentina, and
ONCEMRK lead study investigator
MedicalResearch.com: What is the background for this study? What are the main findings?
The ONCEMRK Phase 3 study was conducted to evaluate the efficacy and safety of once-daily ISENTRESS (raltegravir) HD 1200 mg (given as two 600 mg oral tablets) compared to twice daily raltegravir 400 mg, each in combination therapy with emtricitabine plus tenofovir disoproxil fumarate in previously untreated adults with HIV-1 infection with levels of HIV-1 RNA ≥ 1,000 copies/mL.
- Week 96 data showed:
- 5 percent of the 531 patients taking once-daily raltegravir 1200 mg (2 x 600 mg) achieved viral suppression of less than 40 copies/mL of HIV-1 RNA, compared to 80.1 percent of the 266 patients taking twice-daily raltegravir 400 mg, both in combination therapy with emtricitabine plus tenofovir disoproxil fumarate, with a treatment difference of 1.4 percent.
- Increases in CD4+T-cell counts from baseline were comparable for the two treatment regimens, with an average increase of 261.6 cells/mm3 for once-daily raltegravir (1200 mg) and 262.2 cells/mm3 for twice-daily raltegravir (400 mg).
- Efficacy was consistent across a variety of patient populations, including those with high viral load at baseline (HIV-1 RNA >100,000 copies/mL).
- Treatment-emergent viral mutations leading to any drug resistance were detected in less than 1 percent of patients in both treatment arms, with 4/531 (0.8 percent) in the once-daily raltegravir (1200 mg) treatment arm, and 2/266 (0.8 percent) in the twice-daily raltegravir (400 mg) treatment arm through 96 weeks.
- The rate of discontinuation of therapy due to adverse events through 96 weeks was low (1.3 percent in patients receiving once-daily raltegravir (1200 mg) and 2.3 percent in patients receiving twice-daily raltegravir (400 mg).
25 Jul Chronic Traumatic Encephalopathy Found In Brains of Nearly All NFL Players Examined
MedicalResearch.com Interview with: [caption id="attachment_36085" align="alignleft" width="150"] Dr. Daneshvar[/caption]
Daniel H. Daneshvar, M.D., Ph.D.
Chronic Traumatic Encephalopathy Center
Team Up Against Concussions | Founder
Boston University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Chronic traumatic encephalopathy (CTE) is a neurodegenerative disease associated with repetitive head impacts. CTE was first described in JAMA in 1928. In the 99 years since, just over 100 cases of CTE have been described in the world’s literature.
This study nearly doubles the number of reported cases of CTE, with 177 cases of CTE in football players. Of note, 110 of the 111 athletes who played in the NFL had CTE. This study represents the largest and the most methodologically rigorous description of a series of patients with CTE ever published. Such a richness of data regarding the clinical and pathological features of CTE has never been previously compiled. As such, this study represents an important advance to the medical literature and an enormous scientific advance in our understanding of chronic traumatic encephalopathy.
25 Jul Unregulated Direct-to-Consumer Treatment Centers Provide Stem Cells for Patients With Heart Failure
MedicalResearch.com Interview with: [caption id="attachment_36068" align="alignleft" width="143"] Dr. Hauptman[/caption]
Dr. Paul J. Hauptman, MD
Professor of Internal Medicine
Division of Cardiology
Assistant Dean, Clinical and Translational Research
Saint Louis University School of Medicine
St. Louis MO 63110-0250
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: A publication in 2016 by Leigh Turner from the University of Minnesota in 2016 shed light on the proliferation of stem cell centers or "businesses" that offer non FDA approved treatments, described as "stem cell therapy" for a variety of conditions. We opted to evaluate sites that claimed to treat heart failure. We collected data on type of infusion, need for a medical evaluation, board certification status of the center physician, cost and other factors. Self reported patient volumes were very variable. Most centers/businesses claimed to use autologous stem cells; a number offered ancillary treatment (i.e. vitamin infusions and hyperbaric oxygen); only one appeared to have a board-certified cardiologist involved. The costs were high for single infusions (mean price of $7694, SD 2737 for autologous cells; slightly less for allogeneic cells). Efficacy claims made during telephone calls with the centers were highly positive.
25 Jul Sex and Ethnicity Data Missing From Many FDA Medical Device Approval Reports
MedicalResearch.com Interview with: [caption id="attachment_36071" align="alignleft" width="169"] Dr. Dhruva[/caption]
Sanket Dhruva, MD, MHS, FACC
Cardiology, VA Connecticut Healthcare System
Robert Wood Johnson Foundation Clinical Scholar
Yale University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: In 2012, Congress passed the Food & Drug Administration (FDA) Safety and Innovation Act, with the goal of increasing enrollment and availability of data in important patient groups such as the elderly, women, and racial and ethnic minorities. In 2014, as mandated by the legislation, the FDA released an Action Plan to address these issues. This Action Plan included the goal of increasing the transparency by posting demographic information of pivotal (or key) clinical trials used to support approval decisions.
We examined how often these data were available in 2015 for all studies used to support approval of all original high-risk medical devices approved in the calendar year following the FDA Action Plan. Examples of these medical devices include stents, bone grafts, heart valves, and spinal cord stimulators. We wanted to understand if age, sex, and race and ethnicity data were available and if the results of clinical studies supporting these medical devices were analyzed to assess if there were differences in safety and effectiveness by these important demographic factors.
Our main findings are that FDA Summaries publicly reported age for 65% of study populations, sex for 66%, and race and/or ethnicity for 51%. Analyses to assess if demographic factors may have impacted device safety and effectiveness were only conducted by age for 9%, by sex for 17%, and by race for 4% of clinical studies.
25 Jul Trying Statins Again After Adverse Effect Linked To Lower Risk of Heart Attack
Posted at 15:28h
in Annals Internal Medicine, AstraZeneca, Author Interviews, Brigham & Women's - Harvard, Heart Disease, Merck, Pharmacology
MedicalResearch.com Interview with:
[caption id="attachment_36047" align="alignleft" width="120"] Dr. Turchin[/caption]
Alexander Turchin, MD,MS
Director of Quality in Diabetes
Associate Professor, Harvard Medical School
Brigham and Women's Hospital
Boston, MA
MedicalResearch.com: What is the background for this study?
Response: Cardiovascular disease is the # 1 cause of death in the U.S. and worldwide. Statins are some of the most effective medications available for prevention of cardiovascular events.
However, many patients stop statins, frequently because of adverse reactions. In our study we aimed to assess the risk-benefit balance of trying a statin again after experiencing an adverse reaction.
24 Jul Iris Freckles Are A Potential Biomarker for Chronic Sun Damage
MedicalResearch.com Interview with: [caption id="attachment_36103" align="alignleft" width="200"] Iris Freckles
Credit: © Africa Studio / Fotolia[/caption] Dr.med.univ. Christoph Schwab Departement of Ophthalmology Medical University of Graz Graz, Austria MedicalResearch.com: What is the background for this study? What are the main findings? Response: Knowledge about risk factors and/or pathways involved in pathogenesis is from special importance in order of preventing diseases. The role of sunlight in several eye diseases is unclear. In our study we found a close relation between sun light exposure - evaluated by a full body skin examination and a personal questionnaire - and iris freckles. Therefore we suggest the presence of iris freckles as a novel biomarker indicating high ocular sun exposure.
24 Jul Diet Rich in Anti-Inflammatory Foods May Help Preserve Brain Function
MedicalResearch.com Interview with: Yian Gu, PhD Assistant Professor of Neuropsychology (in Neurology and Taub Institute for Research on Alzheimer's Disease and the Aging Brain) Columbia University Medical Center MedicalResearch.com: What is the background for this study? What are the main findings? Response: We have previously shown that elderly individuals who consume healthier diet (certain foods, nutrients, and dietary patterns) have larger brain volume, better cognition, and lower risk of developing Alzheimer’s disease. The current study aimed to examine the biological mechanisms for the relationship between diet and brain/cognitive health.24 Jul Small Cell Lung Cancers Form Chemotherapy-Resistant Circulating Tumor Spheres
MedicalResearch.com Interview with: [caption id="attachment_36074" align="alignleft" width="133"] Prof. Hamilton[/caption]
Prof. Gerhard Hamilton
Department of Obstetrics and Gynecology
Medical University of Vienna
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Small cell lung cancer (SCLC) is a highly aggressive tumor (15 % of all lung cancers) mainly of patients with high tobacco consumption which shows an extremely poor survival (< 5% 2-year survival rate). Unfortunately the
low survival rates of advanced SCLC cases has not improved significantly during the last decades, with platinum drugs/etoposide and topotecan employed for first- and second-line chemotherapy, respectively. All kinds of new chemotherapeutics, targeted drugs and immunotherapies either failed or resulted in prolongation of survival of several months at best. SCLC responds well to first-line therapy but relapses within a short time as chemoradioresistant tumor. The failure of hundreds of registered studies seem to be linked to the lack of knowledge of the mechanism of resistance of SCLCs and proper ways to reverse the refractoriness.
Small cell lung cancer is distinguished by excessive numbers of circulating tumor cells (CTCs) in advanced stages. CTCs contain the founder of metastasis and seem to constitute a highly chemoresistant cell population. Thus, we ware able to establish a panel of permanent CTC lines in vitro for the first time (8 SCLC lines so far from blood samples). Although CTCs were considered to be chemoresistant we detected that they are chemosensitive in vitro in form of single cell suspensions. However, all CTC lines developed spontaneously into large multicellular aggregates, termed tumorospheres, which grow up to 1-2 mm in size and exhibit high chemoradioresistance due to limited drug perfusion as well as content of quiescent and hypoxic cells. Resistance to irradiation seems to be caused by lack of oxygen, such limiting the generation of oxygen radicals. High resistance mediated by the occurrence of tumorospheres easily explains the failure of a large number of drugs - if one is not able to achieve a sufficient concentration of a drug in cancer cells and the cells are quiescent, the respective compounds will not be able to destroy the target cells, regardless of their chemical nature.
24 Jul Duration of Dual Anti-Platelet Therapy After Cardiac Stenting Needs To Be Personalized
MedicalResearch.com Interview with: Abhishek Sharma MD and Division of Cardiovascular Medicine State University New York Downstate Medical Center Dr.Sahil Agarwal M.B.B.S., M.D. Division of Cardiology St. Luke's University Health Network Bethlehem, Pennsylvania MedicalResearch.com: What is the background for this study? Response: Prior randomized control trials (RCTs) and meta-analysis of these trials which have attempted to compare differences in outcomes between strategies of short (S) (3-6 months) and longer (L) (12-30 months) durations of dual anti-platelet therapy (DAPT) after drug eluting stents (DES) implantation have reported conflicting results. In general, the events rates in these studies were small, affecting statistical power. To overcome this limitation, we conducted an updated meta-analysis to compare the efficacy and safety of strategies of S-DAPT versus L-DAPT strategy after DES implantation by restricting inclusion to randomized studies with follow-up durations of 24 months or longer. The current meta-analysis is the first to compare outcomes between S-DAPT and L-DAPT in a meta-analysis restricted to trials with patient follow-up of 24 months or longer. We found no significant difference in the rates of mortality or of stent thrombosis with S-DAPT or L-DAPT. S-DAPT was associated with significantly lower risk of major bleeding but slightly higher risk of future myocardial infarctions.22 Jul Changes in Hospital Inpatient Stays Over Ten Years: Less Cardiac Care, More Mental Health and Sepsis Admissions
MedicalResearch.com Interview with: Ruirui Sun, Service Fellow, Economist Center for Delivery, Organization and Markets Agency for Healthcare Research and Quality MedicalResearch.com: What is the background for this study? Response: Hospital inpatient care has experienced changes due to factors such as population growth, rising of prevalence of chronic disease and efforts to reduce unnecessary hospitalizations. We generated information from the National Hospital Utilization and Costs path on Fast Stats (https://www.hcup-us.ahrq.gov/faststats/landing.jsp ), to present the trends on national hospitalization and costs from 2005 to 2014, as well as the most common diagnoses among inpatient stays over the 10-year period. MedicalResearch.com: What are the main findings?- Between 2005 and 2014, the inflation-adjusted mean cost per inpatient stay increased by 12.7 percent, from $9,500 to $10,900.
- Inflation-adjusted cost per stay for patients covered by private insurance or Medicaid increased 16-18 percent. Cost per stay for Medicare-covered patients and the uninsured changed minimally.
- The rate of inpatient stays decreased the most among patients in the highest income quartiles (15-20 percent decrease).
- The proportion of Medicaid-covered inpatient stays increased by 15.7 percent, whereas the proportion paid by private insurance and that were uninsured decreased by 12.5 and 13.0 percent, respectively.
- Mental health/substance use accounted for nearly 6 percent of all inpatient stays in 2014, up 20.1 percent from 2005.
- Between 2005 and 2014, septicemia and osteoarthritis became two of the five most common reasons for inpatient stays. Septicemia hospital stays almost tripled.
- Nonspecific chest pain and coronary atherosclerosis decreased by more than 60 percent from 2005 to 2014, falling off the list of top 10 reasons for hospitalization.
21 Jul Drugs That Target Th17 Cells Can Improve Debilitating Skin Disease Hidradenitis suppurativa
MedicalResearch.com Interview with: [caption id="attachment_36058" align="alignleft" width="200"]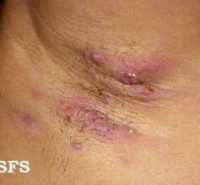 Hidradenitis suppurativa
Wikipedia image[/caption] Dr Jean Fletcher Assistant Professor Schools of Medicine and Biochemistry & Immunology Trinity College Dublin, the University of Dublin Dublin, Ireland MedicalResearch.com: What is the background for this study? What are the main findings? Response: Hidradenitis suppurativa (HS) is an inflammatory skin disease which causes deep, painful lesions in areas such as the underarms and groin. 1-4% of people are thought to suffer from the disease, however as it is under recognised and often misdiagnosed these may be conservative estimates. The pain and distress associated with HS leads to a poor quality of life with many patients experiencing depression. Current interventions include combinations of antibiotics, surgery to remove lesions and more recently the use of the biologic therapies such as TNF inhibitors; however these are often ineffective and there is a pressing need for more effective treatments. The cause of Hidradenitis suppurativa is unknown, however there are known risk factors which include smoking and obesity, and there is an association with inflammatory bowel disease, which suggests that dysregulation of the immune system may play a role.
21 Jul Majority of Murdered Women Are Killed By Current or Former Partners
Posted at 20:16h
in Accidents & Violence, Author Interviews, CDC, Emory, Gender Differences, Race/Ethnic Diversity
MedicalResearch.com Interview with:
[caption id="attachment_36053" align="alignleft" width="120"] Dr. Petrosky[/caption]
EmikoPetrosky MD M.P.H
Science Officer, National Violent Death Reporting System at Centers for Disease Control and Prevention
Centers for Disease Control and Prevention
Emory University Rollins School of Public Health
MedicalResearch.com: What is the background for this study?
Response: Homicide is one of the leading causes of death for women aged 44 years and younger. In 2015, 3,519 girls and women died by homicide in the United States. It is the 5th leading cause of death for women under 45 years age (defining women as 18-44 years of age).
The National Violent Death Reporting System (NVDRS) links together data from death certificates, coroner/medical examiner reports, and law enforcement reports, resulting in more information about the circumstances of death than what is available elsewhere.
21 Jul How To Evaluate Cognitive Function in the Aging Physician?
MedicalResearch.com Interview with: [caption id="attachment_36003" align="alignleft" width="161"] Dr. Dellinger[/caption]
E. Patchen Dellinger, M.D.
Professor, Department of Surgery
University of Washington, Box 356410
Seattle, Washington 98195-6410
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: As I passed the age of 70 myself and began considering when to slow down and/or retire I decided to examine the literature about age and physician competence. I have had a wonderful, rewarding time in surgery but have always wanted to provide the best possible care for my patients. On my review of an extensive literature on this topic I found examples of physicians who had become dangerous to their patients with age but persisted because of their eminence and also of physicians who continued to deliver high quality care well into old age.
In medicine, unlike most other safety conscious industries, we have not really taken a systematic approach to the issue of policies related to the aging physician.
21 Jul Stress of 911 Linked To Decrease In Male Babies Born With Birth Defects
MedicalResearch.com Interview with: Parvati Singh B. Tech, MBA, MPA PhD student, Department of Public Health, University of California, Irvine and Dr. Tim Bruckner, first author MedicalResearch.com: What is the background for this study? What are the main findings? Response: This study builds upon earlier research by our group which showed that male fetal deaths rose and the number of liveborn males fell after the 9/11 attacks. Here we show that, in California, the number of live born males with birth defects fell after 9/11. This finding appears consistent with the notion that frail male gestations, such as those with defects, may have been lost in utero as a result of the stress induced by the 9/11 attacks.21 Jul Erectile Dysfunction Should Be a Marker For Diabetes
MedicalResearch.com Interview with: [caption id="attachment_36076" align="alignleft" width="192"] Damiano Pizzol [/caption]
Damiano Pizzol
Operational Research Unit, Doctors with Africa Cuamm
Beira, Mozambique
MedicalResearch.com: What is the background for this study?
Response: Since the 1970s the association between diabetes and the development of erectile dysfunction has been documented both in animal models and humans Several studies have considered the prevalence of erectile dysfunction in diabetes and the majority agree that the incidence of erectile dysfunction in men with diabetes is two- to three-fold higher than in the general population. It is estimated that erectile dysfunction affects up to 75% of all men with diabetes, it is age correlated and occurs at a younger age in men with diabetes.
20 Jul Cochlear Bridges the Technology Gap with First Made for iPhone Cochlear Implant Sound Processor
MedicalResearch.com Interview Provided on behalf of: Jan Janssen, Senior Vice President
Research and Development
Cochlear Limited
MedicalResearch.com: What is the background for this device?
Response: Cochlear implants treat hearing loss by electrical stimulation of the hearing nerve, bypassing the damaged parts of the hearing pathway. Cochlear implants system consist out of an external sound processor that detects and processes the sounds and then sends them to the implant. The implant receives this information and turns it into electrical signals that are delivered to the hearing nerve and from there to the brain.
The Nucleus® 7 Sound Processor is the world’s first and only Made for iPhone cochlear implant sound processor, allowing users to stream sound from their iPhone®, iPad® and iPod touch® directly to their cochlear implant sound processor. It not only enhances the experience of talking on the phone, it also makes features like enjoying music or watching videos, as well as audio apps such as Maps or FaceTime, more easily accessible.
The Nucleus 7 Sound Processor is also the smallest and lightest behind-the-ear sound processor on the market.
20 Jul Daily Crossword Puzzles May Help Sustain Brain Function As We Age
MedicalResearch.com Interview with: [caption id="attachment_36033" align="alignleft" width="133"] Prof. Wesnes[/caption]
Professor Keith A. Wesnes
BSc PhD FSS CPsychol FBPsS
Head Honcho, Wesnes Cognition Ltd
Professor of Cognitive Neuroscience, Medical School, University of Exeter, UK
Visiting Professor, Department of Psychology
Northumbria University, Newcastle, UK
Adjunct Professor, Centre for Human Psychopharmacology, Swinburne University, Melbourne, Australia
Visiting Professor, Medicinal Plant Research Group
Newcastle University, UK
Wesnes Cognition Ltd, Little Paddock, Streatley Hill, Streatley on Thames UK
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: This data we reported were taken from the PROTECT study, a 10-year research programme being conducted jointly by Kings College London and the University of Exeter Medical School. It started in November 2015 and over 20,000 individuals aged 50 to 96 years have enrolled.
A highly novel feature of the study is that it is run entirely remotely, the participants logging on via the internet at home and providing demographic and life style information, and also performing online cognitive tasks of key aspects of cognitive function. The tasks are from two well-validated systems, CogTrack and the PROTECT test system, and assess major aspects of cognitive function including focused and sustained attention, information processing, reasoning and a range of aspects of memory.
One of the lifestyle questions was ‘How frequently do you engage in word puzzles, e.g. crosswords?’ and the 6 possible answers were: never; occasionally; monthly; weekly; daily; more than once per day. We analysed the cognitive data from 17,677 individuals who had answered the question, and found that the more often the participants reported engaging in such puzzles, the better their cognitive function on each of the 9 cognitive tasks they performed. The group who never performed such puzzles were poorest on all measures, and the improvements were mostly incremental as the frequency of use increased. The findings were highly statistically reliable, and we controlled for factors including age, gender and education. To evaluate the magnitudes of these benefits, we calculated the average decline over the age-range on the various tasks in the study population. The average difference between those who ‘never’ did puzzles to those who did so ‘more than once a day’ was equivalent to 11 years of ageing; and between those who never did puzzles and all those who did was 8 years.