

 Dr. Tong[/caption]
Dr Tammy Y N Tong PhD
Cancer Epidemiology Unit
Nuffield Department of Population Health
University of Oxford, Oxford, UK
MedicalResearch.com: What is the background for this study?
Response: Vegetarian and vegan diets have become increasingly popular in recent years, partly due to the perceived health benefits, but also concerns about the environment and animal welfare. However, the full extent of the potential health benefits and hazards of these diets is not well understood. Previous studies have suggested that vegetarians have a lower risk of coronary heart disease than non-vegetarians, but data from large studies are limited, and little has been reported on the difference in risk of stroke.
 Dr. Sepehrvand[/caption]
Nariman Sepehrvand, MD
Research Associate & PhD Candidate
Canadian VIGOUR Centre, and Department of Medicine,
University of Alberta, Edmonton, Canada
Medical Research: Can you tell us a little bit about the background of this study?
Dr. Sepehrvand: As you know the traditional randomized clinical trials (RCT) have been criticized from time to time for the lack of generalizability, high costs and lengthy processes. Pragmatic trials with the primary goal of informing patients, clinicians, healthcare administrators and policy-makers about the effectiveness of biomedical and behavioral interventions have the potential to address those shortcomings by enrolling a population representative of the populations in which the intervention will be eventually applied to and by streamlining and simplifying the trial-related procedures. We knew about the challenges that trialists encounter in the design and implementation of pragmatic trials, so we were wondering how pragmatic or explanatory are cardiovascular (CV) RCTs and if there has been any change over time!
 Dr. Deepak L. Bhatt[/caption]
Deepak L. Bhatt, MD, MPH, FACC, FAHA, FSCAI, FESC
Professor of Medicine, Harvard Medical School
Executive Director of Interventional Cardiovascular Programs,
Brigham and Women’s Hospital Heart & Vascular Center
MedicalResearch.com: What is the background for this study?
Response: Dual antiplatelet therapy (DAPT) is known to improve outcomes in patients with acute coronary syndromes (ACS), prior myocardial infarction (MI), or recent coronary stenting. What was unknown is whether patients with diabetes and stable coronary artery disease – a group generally believed to be at high ischemic risk – would benefit from initiation of long-term DAPT with low-dose aspirin plus ticagrelor versus low-dose aspirin (plus placebo). This is what THEMIS was designed to test, with THEMIS-PCI designed prospectively to examine those patients specifically who had a history of previous percutaneous coronary intervention (PCI).

 Dr. Zeig-Owens[/caption]
Rachel Zeig-Owens, Dr.P.H., MPH
FDNY
Research Assistant Professor
Albert Einstein Medical Center
MedicalResearch.com: What are the main findings?
Response: We found that the most exposed members, those who arrived first at the World Trade Center (WTC ) site—when the air-borne dust was thickest—have a 44% increased risk of cardiovascular disease (CVD) compared to those who arrived later in the day. This is a level risk that was similar to other known risk factors for CVD.
 Dr. Nicolau[/caption]
Jose Carlos Nicolau, MD PhD
Heart Institute
University of Sao Paulo Medical School,
Sao Paulo, Brazil
MedicalResearch.com: What is the background for this study?
Response: There are few evidence about the late phase (1-3 years) of patients with diabetes and myocardial infarction, especially regarding quality of life (qol) and health resource utilization. Our study showed that the population with diabetes (dm), compared with the population without diabetes, have worse quality of life, more hospitalizations, and when hospitalized showed a longer hospital stay. Additionally, as expected, dm population have worse outcomes, including the composite of cv death, myocardial infarction or stroke, and all-cause death.
 Prof. John McMurray[/caption]
Prof. John McMurray
Professor of Cardiology
Institute of Cardiovascular & Medical Sciences
University of Glasgow
MedicalResearch.com: What is the background for this study?
Response: SGLT2 inhibitors prevent the development of heart failure (HF) in patients with type 2 diabetes (T2D) – can they be used to treat patients with established heart failure? Also, although introduced as a glucose-lowering treatment for T2D, experimental evidence suggests these drugs may have non-glucose mediated benefits. So, might they be a treatment for HF even in patients without diabetes?
 Prof. Danchin[/caption]
Nicolas Danchin MD, FESC
Professor of Medicine, Consultant Cardiologist
Intensive Cardiac Care Unit
Hôpital Européen Georges Pompidou
Paris, France
MedicalResearch.com: What is the background for this study?
Response: FAST-MI is a programme of nationwide French surveys, carried out every 5 years in France since 2005 in patients hospitalised with STEMI or NSTEMI. Patients are included consecutively for one month and 10-year follow-up is organized. We can thus analyse patients' outcomes in relation with their profile. Knowing that diabetic patients represent a large proportion of patients with AMI, we thought it would be worthwhile determining whether they suffered specific complications, and in particular, heart failure, both at the acute stage and in the subsequent months.

 Dr. Windham[/caption]
Gwen Windham, MD MHS
Professor of Medicine
Memory Impairment & Neurodegenerative Dementia (MIND) Center
University of Mississippi Medical Center
MedicalResearch.com: What is the background for this study?
Response: Silent infarctions are a primary cause of strokes in the brain, but they are also common in people without a history of a stroke. Infarctions are generally only reported if they are larger (at least 3mm) and are ignored clinically if they are smaller (less than 3mm).
We examined 20 years of cognitive decline among stroke free, middle-aged people with and without smaller, and larger infarctions. The comparison groups included participants as follows: those with
(1) no infarctions, the reference group;
(2) only smaller infarctions;
(3) only larger infarctions
4) both smaller and larger infarctions
 Dr. Baden[/caption]
Megu Baden, MD, PhD
Department of Nutrition
Harvard T. H. Chan School of Public Health
Boston, MA02115
MedicalResearch.com: What is the background for this study? Would you give an example of healthful vs non-healthful plantbased diet?
Response: Plant-based diets are recommended for health and recently also for their environmental benefits. However, most previous studies defined it as either vegetarian or non-vegetarian, and importantly, without differentiation for the quality of plant foods. As you know, not all plant foods are equally good to our health.
Therefore, to capture the quality of plant-based diets, we established overall, healthful and unhealthful plant-based diet indices. A higher score on the overall plant based diet index indicates greater intake of all types of plant foods and less of animal foods. A higher score on the healthful plant based diet index indicates greater intake of only healthy plant foods (whole grains, fruits, vegetables, nuts, legumes, vegetable oils, tea/coffee), and less of less healthy plant foods (fruit juices, refined grains, potatoes, sugar-sweetened beverages, sweets/desserts) and animal foods. A higher score on the unhealthful plant based diet index indicates greater intake of only less healthy plant foods, and less of healthy plant foods and animal foods.
In this study, we used these plant-based diet indices and investigated the associations between 12-year changes in plant-based diet quality and subsequent total and cause-specific mortality in two large US cohorts.

 Dr. Yano[/caption]
Yuichiro Yano MD
Assistant Professor in Family Medicine and Community Health
Duke University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: African Americans are disproportionally affected by hypertension-related cardiovascular disease compared with other racial/ethnic groups in the United States and have higher blood pressure levels inside and outside the clinic than whites and Asians. However, little is known, among African Americans, regarding whether higher mean blood pressure measured outside of the clinic setting on 24-hour ambulatory blood pressure monitoring is associated with an increased risk for cardiovascular disease events, independent of blood pressure measured in the clinic setting.
 Dr. Kaski[/caption]
Dr Juan Pablo Kaski MD(Res) FRCP FESC
Director of the GOSH Centre for Inherited Cardiovascular Diseases
Great Ormond Street Hospital,
University College London Institute of Cardiovascular Science,
London, UK
MedicalResearch.com: What is the background for this study? Would you briefly explain what is meant by Hypertrophic Cardiomyopathy?
Response: Hypertrophic cardiomyopathy (HCM) is a genetic condition characterised by abnormal thickening of the muscle of the heart and can affect people of all ages. It is associated with an increased risk of sudden cardiac death (SCD) and, in the last few years, a clinical risk tool that estimates the 5-year risk of SCD in adults with HCM has been developed.
However, there are no similar risk models in children, where risk stratification has traditionally been based on clinical risk factors extrapolated from the adult population. We have recently shown that this approach does not discriminate risk well in children, and so the aim of this study was to develop a new risk tool to provide an individualised risk of SCD in children with HCM.

 Nicola Bondonno PhD
National Health and Medical Research Council Early Career Research Fellow
School of Medical and Health Sciences
Edith Cowan University
Joondalup Perth WA
MedicalResearch.com: What is the background for this study?
Response: In an aging society, there could be a huge importance in appropriate evidence-based diets to reduce mortality risk. Therefore, our main question was ‘do diets high in flavonoids reduce the risk of all-cause and cause-specific mortality and is this relationship affected by lifestyle risk factors for early mortality’?
In brief, this is the largest study of flavonoid intake and mortality outcomes to date. This population based cohort study was conducted in 56,048 men and women of the Danish Diet, Cancer, and Health Cohort, followed for 23 years, with estimated intakes of 219 individual flavonoid compounds. The results provide a clarity not seen in previous smaller, often underpowered studies.

 Dr. Ushio[/caption]
Misti Ushio, Ph.D.
Chief Executive Officer
[caption id="attachment_50688" align="alignleft" width="125"]
 Dr. Graziano[/caption]
Michael Graziano, PhD
Chief Scientific Officer
TARA Biosystem
MedicalResearch.com: What is the background for this study?
Response: Almost half of all drug recalls are due to cardiac toxicity that was not picked up during early screens. These human cardiac liabilities can go undetected because historically it has been challenging to predict how human hearts will respond to potentially cardiotoxic drugs despite rigorous testing in both animals and in vitro systems throughout drug development. Traditional in vitro systems and animal models do not translate well to humans, and human donor tissue availability is limited for in vitro testing.
There is great potential for human-induced pluripotent stem cell cardiomyocytes (iPSC-CMs) to bridge this human translation gap, but it’s been a challenge to train these cells to recapitulate pharmacology seen in mature human heart cells.
This stems from the fact that existing experimental models utilize immature human iPSC-CMs which lack relevant physiological hallmarks of adult human cardiac muscle and therefore fail to predict drug responses seen in the clinic.
 Nancy Niguidula, MS, DPH
Doctorate in Public Health in Toxicology
Ambry Genetics
MedicalResearch.com: What is the background for this study?
Response: The clinical presentations of many inherited cardiovascular conditions overlap; thus, genetic testing may clarify diagnoses, help with risk stratification, facilitate appropriate clinical management decisions, and aid in identifying asymptomatic, at-risk relatives. A large number of professional societies have developed practice guidelines and recommendations for genetic testing of cardiovascular diseases. These include international and collaborative expert panels that establish genetic screening and treatment recommendations by drawing on evidence-based medicine. To further strengthen the clinical utility of cardiovascular genetic testing, the American College of Medical Genetics and Genomics (ACMG) published a guideline for 59 genes with clinical actionability that should be reported if found on whole exome sequencing, even when unrelated to the testing indication.
 Dr. Cheng[/caption]
Dr. Alan Cheng, MD MBA
Vice President at Medtronic
Clinical Research and Therapy Development, Cardiac Rhythm Management
Medtronic, Minnesota 55112
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Ventricular arrhythmias can be life threatening among patients with certain types of heart disease. While implantable cardioverter defibrillators (ICDs) have become the primary means in managing these events, we still don’t fully understand when ventricular arrhythmias occur and whether they are just random events that occur at any time of the day.
We pooled patient-level data from 6 prospective studies of ICD recipients and leveraged the continuous monitoring features of the ICD to understand when ventricular arrhythmias occur. Across almost 4000 patients with almost 2 years average follow up from the time of implant, we saw that ventricular arrhythmias aren’t randomly distributed throughout the day. In fact, there is a predilection for these events to occur during normal waking hours as compared to the times of the day when most patients are asleep.
Additionally, we found that across the year, the spring season had higher rates of arrhythmia occurrence when compared to summer. We didn’t observe any differences in arrhythmia occurrence by the days of the week or months of the year. This analysis is not the first to explore this question but it is the largest to date.
 Dr. Chaudhary[/caption]
Muhammad Ali Chaudhary, MD
Research Scientist
Center for Surgery and Public Health
Department of Surgery
Brigham and Women’s Hospital
Harvard Medical School
Harvard T. H. Chan School of Public Health
MedicalResearch.com: What is the background for this study?
Response: Many studies have documented disparities in cardiovascular care for minorities, specifically African Americans compared to white patients. Coronary artery bypass grafting (CABG) is a common procedure in the United States, and the outcomes and post-surgical care for African Americans tend to be worse. We examined whether patients insured through TRICARE — a universal insurance and equal-access integrated healthcare system that covers more than 9 million active-duty members, veterans and their families — experienced these disparities. We found no racial disparities in quality-of-care outcomes, providing insights about the potential impacts of universal insurance and an equal-access health care system.
The study included 8,183 TRICARE patients, aged 18-64, who had undergone CABG. The study took its data from TRICARE health care claims from the Military Health System Data Repository for the years of 2006 to 2014.
 Dr. Friedman[/caption]
Paul Friedman, M.D.
Professor of Medicine
Norman Blane & Billie Jean Harty Chair
Mayo Clinic Department of Cardiovascular Medicine
Honoring Robert L. Frye, M.D.
MedicalResearch.com: What is the background for this study?
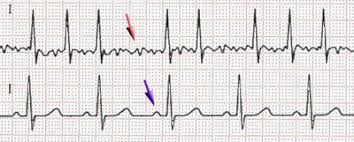
Response: Atrial fibrillation is an irregular heart rhythm that is often intermittent and asymptomatic. It is estimated to affect 2.7–6.1 million people in the United States, and is associated with increased risk of stroke, heart failure and mortality. It is difficult to detect and often goes undiagnosed. After an unexplained stroke, it is important to accurately detect atrial fibrillation so that patients with it are given anticoagulation treatment to reduce the risk of recurring stroke, and other patients (who may be harmed by this treatment) are not. Currently, detection in this situation requires monitoring for weeks to years, sometimes with an implanted device, potentially leaving patients at risk of recurrent stroke as current methods do not always accurately detect atrial fibrillation, or take too long.
We hypothesized that we could train a neural network to identify the subtle findings present in a standard 12-lead electrocardiogram (ECG) acquired during normal sinus rhythm that are due to structural changes associated with a history of (or impending) atrial fibrillation. Such an AI enhanced ECG (AI ECG) would be inexpensive, widely available, noninvasive, performed in 10 seconds, and immensely useful following embolic stroke of unknown source to guide therapy. To test this hypothesis, we trained, validated, and tested a deep convolutional neural network using a large cohort of patients from the Mayo Clinic Digital Data Vault.
 MedicalResearch.com: What is the background for this study?
Response: We know that having atrial fibrillation puts you at a higher risk of falls, especially if you are elderly and frail. Additionally, some of the medications used to treat it can cause bradycardia (low heart rate), which could itself increase the risk of falls. Therefore, the aim of this study was to investigate if common medications used to treat atrial fibrillation in older patients were associated with fall-related injuries and syncope (fainting). The medications investigated were rate-lowering drugs (beta-blockers, digoxin, verapamil, diltiazem) and the anti-arrhythmic drugs (amiodarone, propafenone, and flecainide).
 Dr. Jackson[/caption]
Jeffrey L Jackson, MD, MPH
Medical College of Wisconsin
Milwaukee, Wisconsin
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Unfortunately, most systematic reviews exclude non-English trials, mostly for convenience, but nearly all systematic reviews wind up excluding at least 1 non-English trial. We looked at whether this was justified, since Google Translate is a free and easily usable platform. We had native-language speakers in 9 languages (Chinese, French, German, Italian, Japanese, Korean, Romanian, Russian and Spanish) abstract data and had another researcher abstract all the articles using Google Translate.
We found that there was over 90% agreement and that the few differences were due to human error, not to problems with the translations.

 Dr. Phelan[/caption]
Dermot Phelan, MD, PhD
Director of the Sports Cardiology Center
Cleveland Clinic in Cleveland, Ohio
MedicalResearch.com: What is the background for this study?
Response: It is well recognized that long-term elite endurance athletes are at higher risk of atrial fibrillation. We wished to evaluate whether this held true for primarily strength-type athletes. We had the opportunity to screen almost 500 former NFL athletes. It became clear that we were seeing more atrial fibrillation than one would expect during the screenings.

 Dr. Wee[/caption]
Christina C. Wee, MD, MPH
Associate Professor of Medicine
Harvard Medical School
Director , Obesity Research Program Division of General Medicine
Beth Israel Deaconess Medical Center (BIDMC)
Associate Program Director, Internal Medicine Program, BIDMC
Deputy Editor of the Annals of Internal Medicine
MedicalResearch.com: What is the background for this study?
Response: New research is showing that for many people without diagnosed heart disease, the risk of bleeding may outweigh the benefits of taking a daily aspirin particularly in adults over 70 years of age. The American Heart Association and the American College of Cardiology recently updated their guidelines and now explicitly recommend against aspirin use among those over the age of 70 who do not have existing heart disease or stroke.
Our study found that in 2017, a quarter of adults aged 40 years or older without cardiovascular disease – approximately 29 million people – reported taking daily aspirin for prevention of heart disease. Of these, some 6.6. million people did so without a physician's recommendation.
 Dr. Bach[/caption]
Richard G. Bach, MD FACC
Professor of Medicine
Washington University School of Medicine
Director, Cardiac Intensive Care Unit
Director, Hypertrophic Cardiomyopathy Center
Barnes-Jewish Hospital
St. Louis, MO 63110
MedicalResearch.com: What is the background for this study?
Response: Elderly patients represent the largest group of those hospitalized for an acute coronary syndrome, and age is an important marker of increased risk. The risk of death and recurrent cardiovascular events is greatest among the elderly. High intensity lipid lowering by statins has been shown to reduce the incidence of recurrent cardiovascular events after an acute coronary syndrome in general, but there remains limited data on efficacy and safety of that treatment in the elderly, and guidelines do not routinely advocate higher intensity treatment for patients older than 75 years. In practice, older age has been associated with a lower likelihood of being prescribed intensive lipid lowering therapy. IMPROVE-IT evaluated the effect of higher-intensity lipid lowering with ezetimibe combined with simvastatin compared with simvastatin-placebo among patients after ACS, and observed that ezetimibe added to statin therapy incrementally lowered LDL-cholesterol level and improved CV outcomes. IMPROVE-IT enrolled patients with no upper age limit, which gave us the opportunity to examine the effect of age on outcome on the benefit of more intensive lipid lowering with ezetimibe combined with simvastatin vs. simvastatin monotherapy.
 Dr. Chen[/caption]
Guanmin Chen MD PhD MPH
Senior Biostatistician Research Facilitation, Alberta Health Services
Adjunct Research Assistant Professor
University of Calgary
Co-authors: Guanmin Chen, PhD, MD, MPH, Megan S. Farris, MSc, Tara Cowling, MA, MSc, Stephen M. Colgan, PhD, Pin Xiang, PharmD, Louisa Pericleous, PhD, Raina M. Rogoza, MSc, Ming-Hui Tai, MSc, PhD, and Todd Anderson, MD
MedicalResearch.com: What are the main findings?
Response:
 Dr. Apple[/caption]
Dr. Fred Apple, PhD, DABCC
Medical director,Clinical Laboratories, Clinical Chemistry, Clinical and Forensic Toxicology and Point of Care Testing, Hennepin HealthCare
Principal investigator, Minneapolis Medical Research Foundation
Professor, Department of Laboratory Medicine and Pathology
University of Minnesota
MedicalResearch.com: What is the background for this study?
Response: Few studies have addressed the role of high sensitivity cardiac troponin (hs-cTn) assays in ruling out myocardial infarction (MI) based on the measurement of a single baseline specimen in US patients presenting to the emergency department with symptoms suggestive of ischemia. Most studies have been published predicated on patients in Europe, Australia, and New Zealand. As US emergency departments have different ordering practices for using cTn in triaging patients, it is important to validate the role of hs-cTn assays in US practices to assure providers of appropriate utilization. We have published two papers using the Abbott ARCHITECT hs-cTnI assay, the same one used outside the US in clinical practice (as this assay is not yet FDA cleared) in a US cohort (clinicialtrials.gov trial: UTROPIA - Sandoval Y, Smith SW, Shah ASV, Anand A, Chapman AR, Love SA, Schulz K, Cao J, Mills NL, Apple FS. Rapid rule-out of acute myocardial injury using a single high-sensitivity cardiac troponin I measurement. Clin Chem 2017;63:369-76. Sandoval Y, Smith SW, Love SA, Sexter A, Schulz K, Apple FS. Single high-sensitivity cardiac troponin I to rule out myocardial infarction. Am J Med 2017;130:1076-1083) that have shown similar rule out capacities predicated on clinical presentation, a normal ECG and the role of hs-cTnI testing.
 Dr. Badve[/caption]
Sunil Badve MBBS, MD, DNB, FRACP, PhD, FASN
Senior Research Fellow, Renal & Metabolic Division
Staff specialist nephrologist | St George Hospital
University of New South Wales
The George Institute for Global Health
Australia
MedicalResearch.com: What is the background for this study?
Response: Despite the high prevalence of cardiovascular thrombotic events and venous thromboembolism (VTE) in chronic kidney disease (CKD), oral anticoagulant therapy is often underutilized in patients with advanced CKD and dialysis-dependent end-stage kidney disease (ESKD) due to uncertainty of benefit and potential bleeding complications. This comprehensive systematic review was performed to study the benefits and harms of oral anticoagulant therapy in patients with CKD.
 Dr. Cordon[/caption]
Ben Cordon, PhD
NIHR Post-doctoral Academic Clinical Fellow
Specialist Registrar training in cardiology
[caption id="attachment_50229" align="alignleft" width="112"]
 Dr. Ware[/caption]
James S. Ware, PhD, MRCP
Reader in Genomic Medicine
Group head within the Cardiovascular Genetics & Genomics Unit
Imperial College London
MedicalResearch.com: What is the background for this study?
Response: Non-ischaemic dilated cardiomyopathy is a common cause of heart failure and carries the risk of life-threatening ventricular arrhythmia. An implantable cardioverter defibrillator (ICD) can be life-saving in this condition. However, the decision to implant an ICD is not one that can be taken lightly - ICD insertion carries its own risks, such as infection or inappropriate shocks, and our ability to predict who will benefit from a device is currently far from perfect. Genetic sequencing is affordable and widely available and for DCM, like many diseases, it is hoped that genetic stratification may one day help deliver personalised management. In DCM, variants in the Lamin A/C gene for example are known to cause a phenotype with early and severe arrhythmias and, as a result, international guidelines advocate a lower threshold for ICD insertion in these patients. However, Lamin A/C is an infrequent cause of DCM. The commonest known genetic cause of DCM are protein-truncating variants in the gene encoding Titin (TTNtv), accounting for ~15% of DCM cases. We wanted to know if this group had a higher risk of arrhythmia than the general DCM population.
Earlier work from our group on this topic found that patients with TTNtv-associated DCM were more likely to have a clinical history of arrhythmia (composite of atrial and ventricular arrhythmia, including NSVT), at the time of their initial DCM diagnosis. But it was unclear if this was driven by ventricular arrhythmia, atrial arrhythmia, or both or if it would translate into a long-term risk of potentially dangerous ventricular arrhythmia of the sort for which an ICD can be life-saving. In another study we analysed a larger cohort of ambulant DCM patients but did not find an increased risk of ventricular arrhythmia – but this was a relatively low-risk group, with comparatively mild symptoms (NHYA I/II heart failure) and moderately impaired LV function. As a result, the overall arrhythmic event rate was low, meaning that the power to detect differences between the TTNtv and non-TTNtv groups was reduced.
 Prof. Rahimi[/caption]
Dr Kazem Rahimi
Deputy Director of the George Centre for Healthcare Innovation
James Martin Senior Fellow in Essential Healthcare
Honorary Consultant Cardiologist at the John Radcliffe Hospital
Deputy Director of the George Institute for Global Health
MedicalResearch.com: What is the background for this study?
Response: In the last century, we have witnessed a dramatic change in the spectrum of valvular heart disease and the prevalence of this condition has been rapidly increasing, due to population ageing, with poor patient outcomes and high healthcare costs associated with the only effective treatment available, which is valve repair or replacement. However, modifiable risk factors for valvular heart disease remain largely unknown, which limits prevention and treatment. We used a state-of-the-art, gene-based method called Mendelian randomization to determine the causality of the association between systolic blood pressure and risk of valvular heart diseases.