
JAMA
12 Mar Rates of Invalid Baseline Concussion Testing May Be Alarmingly High
MedicalResearch.com Interview with: [caption id="attachment_40530" align="alignleft" width="200"] Dr. Christopher Abeare[/caption]
Christopher Abeare, Ph.D.
Associate Professor
Clinical Neuropsychology
Department of Psychology
University of Windsor
Windsor, Ontario
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: In this study, we examined the prevalence of invalid performance on baseline neurocognitive testing in sport concussion. Baseline testing is a commonly employed practice in which the cognitive abilities of athletes are assessed pre-season. These baseline test results are then used as a point of comparison against which post-injury neurocognitive test results can be compared, thereby creating a more individualized approach to the assessment of neurocognitive functioning.
However, there has been growing concern about the validity of baseline test results, meaning that there is concern over the degree to which the scores on these baseline tests actually reflect an athlete’s true cognitive ability. There are many reasons why their test scores might not reflect their actual ability, ranging from inattentiveness during testing and lack of appreciation of the importance of doing their best on testing to intentional underperformance (aka “sandbagging” or malingering).
As a result of these concerns, 4 different validity measures have been developed. We compared these 4 validity measures, head to head, in a sample of 7897 athletes aged 10 to 21 years.
We found that 56% of athletes failed at least 1 of these validity measures, suggesting that as many as 56% of athletes have scores that may not reflect their true ability level. We then tested the hypothesis that age would be related to the proportion of athletes with invalid performance. Our findings supported this hypothesis in that nearly 84% of 10-year-olds failed at least one validity measure and 29% of 21-year-olds failed at least one.
12 Mar Combination Meropenem-Vaborbactam (Vabomere) Successfully Treats Complicated Urinary Tract Infections
MedicalResearch.com Interview with: [caption id="attachment_40520" align="alignleft" width="148"] Dr. Kaye[/caption]
Keith S. Kaye, MD, MPH
Professor of Medicine, Division of Infectious Diseases
University of Michigan Medical School
Ann Arbor MI
MedicalResearch.com: What is the background for this study?
Response: Complicated complicated urinary tract infections (cUTI), including acute pyelonephritis, are a major cause of hospital admissions, and are associated with significant morbidity and mortality and can be difficult to treat. While the most common pathogen is Escherichia coli, the more problematic pathogens are multidrug-resistant (MDR) gram-negative organisms including other Enterobacteriaceae species. The prevalence of cUTI due to MDR gram-negative bacteria has risen. In some instances, MDR gram-negative bacteria isolated from the urinary tract can cause bacteremia.
Vabomere was approved by the U.S. Food and Drug Administration (FDA) in August 2017 for the treatment of adult patients with cUTI, including pyelonephritis, caused by designated susceptible Enterobacteriaceae: Escherichia coli, Klebsiella pneumoniae and Enterobacter cloacae species complex. Vabomere is a fixed-dose (2g/2g) combination product of a carbapenem and a β-lactamase inhibitor with potent in vitro activity against Klebsiella pneumoniae carbapenemase (KPC)-producing carbapenem-resistant Enterobacteriaceae (CRE), an important MDR organism associated with serious infections.
The Targeting Antibiotic Non-susceptible Gram-negative Organisms (TANGO I) trial was the pivotal Phase 3 study that compared the efficacy and safety of Vabomere to piperacillin-tazobactam in the treatment of patients with cUTI and acute pyelonephritis.
11 Mar Dermoscopy Helps Improve Diagnosis of Early Melanoma
MedicalResearch.com Interview with: [caption id="attachment_40495" align="alignleft" width="200"]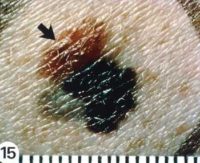 Superficial spreading melanoma arising from a dysplastic nevus
NCI image[/caption] Aimilios Lallas, PhD First Department of Dermatology, School of Medicine Aristotle University Thessaloniki, Greece MedicalResearch.com: What is the background for this study? What are the main findings? Response: Our goal today is to recognize melanoma at the earliest stage, ideally before it invades the dermis and acquires metastatic potential. Melanoma-specific dermoscopic criteria have been tested mainly in the context of invasive melanoma. Although they were proven valid melanoma predictors, the question still remains if they are strong enough to diagnose melanoma in situ (MIS). Our aim was to investigate the diagnostic accuracy of dermoscopic criteria for the diagnosis of melanoma in situ. We identified 5 main positive dermoscopic indicators of MIS: atypical network, regression, irregular hyperpigmented areas, prominent skin markings and angulated lines.
10 Mar Gleason Score 9-10 Prostate Cancer Patients Benefit From Comprehensive Treatment Strategy
MedicalResearch.com Interview with: [caption id="attachment_40464" align="alignleft" width="200"] Dr. Kishan[/caption]
Amar U. Kishan, MD
Assistant Professor
Department of Radiation Oncology
University of California, Los Angeles
MedicalResearch.com: What is the background for this study?
Response: Patients with high risk prostate cancer have several curative treatment options: radical prostatectomy, external beam radiotherapy with androgen deprivation therapy, and external beam radiotherapy with a brachytherapy boost, also with androgen deprivation therapy (so-called extremely dose-escalated radiotherapy). Prior attempts at comparing long-term clinical outcomes between these treatment options have been hampered by the fact that standards of care have changed significantly with respect to the appropriate dose of radiation and the usage of androgen deprivation therapy. Therefore, many comparative effectiveness reports are in essence comparing apples with rotten oranges.
Further, not all high risk prostate cancers are the same. Gleason score 9-10 disease is a particularly aggressive form of prostate cancer that is much more likely to metastasize and potentially cause death. Thankfully, this is a rarer type of prostate cancer -- but this also means that not much data are available specifically for this type of disease.
Therefore, we launched a multi-institutional study of men with Gleason score 9-10 disease, including 1809 men treated across 12 institutions. All men were treated between 2000 and 2013 and therefore were more likely to have treatments that would be commensurate with modern standards.
05 Mar Sustaining Physical Activity With Age Decreases All-Cause Mortality Risk
MedicalResearch.com Interview with: Trine Moholdt, PhD
Research Fellow
Department of Circulation and Medical Imaging | Exercise, Cardiometabolic Health and Reproduction
Norwegian University of Science and Technology
MedicalResearch.com: What is the background for this study?
Response: Although obese individuals have an increased risk of cardiovascular disease, evidence from many observational studies shows that in those who already have cardiovascular disease, being overweight or obese is associated with lower risk of mortality compared to their normal weight counterparts.
This phenomenon is often called the “obesity paradox”. Recently we observed that in individuals who have a high physical activity level, there is no such obesity paradox and body mass index did not associate with survival time in those who with high physical activity (Moholdt et al, American Journal of Medicine, 2017).
03 Mar AI Trained Computer Program Can Monitor Health Forums To Detect Adverse Drug Reactions
MedicalResearch.com Interview with: [caption id="attachment_40358" align="alignleft" width="200"] Dr. Sarin[/caption]
Kavita Sarin, M.D., Ph.D.
Assistant Professor of Dermatology
Stanford University Medical Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Drug reactions occur in the majority of patients undergoing cancer therapies. Half of serious drug reactions are detected after market approval which can result in painful complications and interruption in therapy. Post-market drug surveillance platforms such as FDA monitoring rely on medical publications and physician reporting and take time to identify trends. We sought to determine if we could identify trends in patient discussions in internet health forums to more rapidly identify chemotherapeutic drug reactions. We chose skin reactions as a proof-of-principle because patients can more easily describe what they see on their skin.
Julia Ransohoff, a medical student, and Azadeh Nikfarham, an informatics postdoctoral fellow trained a computer to recognize when a patient undergoing anti-cancer treatment with PD-1 antagonists or EGFR-inhibitors described a drug reaction in their internet forum posts.
02 Mar Focusing On Employment Early Improves Success In Veterans with PTSD
MedicalResearch.com Interview with: [caption id="attachment_40322" align="alignleft" width="133"] Dr. Davis[/caption]
Dr. Lori Davis, MD
Research and Development Service, Tuscaloosa Veterans Affairs (VA) Medical Center,
Department of Psychiatry, School of Medicine, University of Alabama, Tuscaloosa
Tuscaloosa, Alabama
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Symptoms of posttraumatic stress disorder (PTSD) interfere with a person’s ability to function at work, making it harder to stay employed and establish oneself in a career. Veterans with PTSD are uniquely challenged given their motivation to serve others, be leaders and not be generally receptive to reaching out for help.
Conventional wisdom about PTSD and employment has traditionally been to first commit to treatment, learn coping skills, manage one’s symptoms and then reintegrate into mainstream employment. However, this view is being transformed by our research that suggests a more assertive recovery-oriented approach to the treatment of PTSD that involves returning to meaningful competitive employment as soon as possible.
This study compared Evidence-based Supported Employment (also known as Individual Placement and Support or IPS) integrated within PTSD treatment teams to the treatment as usual Transitional Work model offered within the VA. This multisite trial demonstrated significantly greater effectiveness of the IPS-supported employment over stepwise, transitional work vocational rehabilitation for Veterans living with chronic PTSD.
02 Mar Selfies Distort Your Face and Make Your Nose Look Bigger
MedicalResearch.com Interview with: [caption id="attachment_40303" align="alignleft" width="142"] Dr. Paskhover[/caption]
Boris Paskhover, MD
Rutgers New Jersey Medical School
Adjunct Instructor,Department of Otolaryngology-Head and Neck Surgery
NYU Langone Medical Center
MedicalResearch.com: What is the background for this study?
Response: Patient's and the general public routinely mention that their nose appears large, especially when they look at photos taken with their phone. I realized that patients in general are taking selfies more often nowadays. In my training, we routinely would tell patient’s not to use selfies as a marker of how they look, and we instead would take a 5ft distance photograph since we knew that is more realistic. I looked through the medical literature, and it appeared to me that no one had thoroughly discussed why selfies are a bad when evaluating the nose. I contacted a colleague at Stanford who has a PhD with interest in computer graphics and we developed a model for the face/nose.
28 Feb Labor Costs Account For Largest Percentage of Operating Room Expenses
MedicalResearch.com Interview with: [caption id="attachment_40286" align="alignleft" width="201"] Dr. Childers[/caption]
Dr. Chris Childers, M.D.
Division of General Surgery
David Geffen School of Medicine at UCLA
Los Angeles, CA 90095
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Over 20 million Americans undergo a surgical procedure each year with a price tag over $1 trillion. The operating room (OR) is a particularly resource dense environment, yet little is known about the actual costs of running an OR. Most previous efforts focusing on OR costs have come from single-site studies with little detail about the drivers of OR costs.
Using financial statements from all California hospitals we estimated that the average cost to the hospital for one minute of OR time was between $36 and $37. Perhaps more notable was the composition of these costs. Almost two-thirds ($20-21) was attributable to “direct costs” - those generated by the OR itself - including $14 for the wages and benefits of staff, $2.50-3.50 for surgical supplies, and $3 for “other” costs such as equipment repair and depreciation. Interestingly, the remainder ($14-16) was dedicated to “indirect costs” such as the costs associated with hospital security and parking. While these indirect costs are necessary for a hospital to run, they are not under the purview of the operating room.
Finally, we also learned that OR costs have increased quickly over the past 10 years – faster than other sectors of healthcare as well as the rest of the economy.
27 Feb Collaborative Heart Failure Care Did Not Reduce Hospitalizations or Mortality, But Reduced Depression and Fatigue
MedicalResearch.com Interview with: [caption id="attachment_40300" align="alignleft" width="142"] Dr. Bekelman[/caption]
David Bekelman, MD, MPH
Associate Professor of Medicine and Nursing
Eastern Colorado Health Care System, Department of Veterans Affairs, Denver, CO
University of Colorado School of Medicine at the Anschutz Medical Campus, Aurora, CO
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Many of the 5.8 million Americans with heart failure live with bothersome symptoms, reduced function and poor quality of life. Improving their care is important because many people with heart failure live with these challenges for years.
This study evaluated the effect of a team intervention, Collaborative Care to Alleviate Symptoms and Adjust to Illness, also called CASA, on several aspects of quality of life in 314 patients with heart failure. The patients, who received care at diverse health systems in Colorado, were randomized to receive usual care or usual care supplemented with the CASA intervention, which included a nurse and a social worker who collaborated with a primary care provider, cardiologist, and palliative care physician to address the patients’ needs.
The study found that the CASA intervention did not influence the primary outcome of heart failure health status, yet did improve patients’ depression and fatigue. CASA did not influence number of patient hospitalizations or mortality.
27 Feb Varicose Veins Associated With Increased Risk of Deep Vein Blood Clots
MedicalResearch.com Interview with: [caption id="attachment_40213" align="alignleft" width="149"] Shyueluen Chang[/caption]
Shyueluen Chang MD
Phlebologist with Dermatologist background
Vein Clinic, Department of Dermatology,
Chang Gung Memorial Hospital
Taoyuan, Taiwan
MedicalResearch.com: What is the background for this study?
Response: Varicose veins are common, with about 23 percent of U.S. adults having the condition, but they are rarely thought to be associated with serious health risks.
In contrast, venous thrombosis (DVT), pulmonary embolism (PE), and peripheral artery disease (PAD) are also vascular diseases that are associated with serious systemic effects. Not much is known about varicose veins and the risk of other vascular diseases. Elucidating potential associations between varicose veins and health-threatening diseases is important.
Partner's note: Understanding the broader impact of vascular diseases can provide valuable insights into the risks associated with varicose veins.
27 Feb Decision Aids Can Help Heart Failure Patients Determine If They Want an LVAD
MedicalResearch.com Interview with: [caption id="attachment_40246" align="alignleft" width="159"]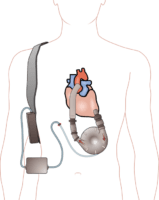 A left ventricular assist device (LVAD) pumping blood from the left ventricle to the aorta, connected to an externally worn control unit and battery pack.
Wikipedia image[/caption] Larry A. Allen, MD, MHS Associate Professor, Medicine Associate Head for Clinical Affairs, Cardiology Medical Director, Advanced Heart Failure Aurora, CO 80045 MedicalResearch.com: What is the background for this study? What are the main findings? Response: Deciding whether or not to get a left ventricular assist device (LVAD) is one of the most challenging medical decisions created by modern medicine. LVADs improve overall survival but also come with serious risks and lifestyle changes. Particularly for older patients with multiple medical problems, this is a complex choice. Our research group at the University of Colorado spent years systematically developing unbiased pamphlet and video decision aids for patients and caregivers. We also developed a clinician-directed decision support training for LVAD program staff. The DECIDE-LVAD trial studied the implementation and effectiveness of this decision support intervention with patients and their caregivers in 6 hospitals in the U.S. When compared to previously used education materials, the decision aids appeared to improve patients’ decision quality and lowered the total number of patients getting LVADs.
26 Feb Standardization and Collaboration Reduced Use of Costly CRRT Treatment for Critically Ill Patients
Posted at 21:12h
in Author Interviews, Cost of Health Care, Critical Care - Intensive Care - ICUs, JAMA, Kidney Disease
MedicalResearch.com Interview with:
[caption id="attachment_40274" align="alignleft" width="143"] Dr. Alban[/caption]
Rodrigo F. Alban, MD FACS
Associate Director Performance Improvement
Associate Residency Program Director
NSQIP Surgeon Champion
Department of Surgery
Cedars-Sinai Medical Center
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Continuous Renal Replacement Therapy (CRRT) is a modality of hemodialysis commonly used to manage renal failure in critically ill patients who have significant hemodynamic compromise. However, it is also resource-intensive and costly and its usage is highly variable and lacks standardization.
Our institution organized a multidisciplinary task force to target high value care in critically ill patients requiring CRRT by standardizing its process flow, promoting cross-disciplinary discussions with patients and family members, and increasing visibility/awareness of CRRT use. After our interventions, the mean duration of CRRT decreased by 11.3% from 7.43 to 6.59 days per patient. We also saw a 9.8% decrease in the mean direct cost of CRRT from $11642 to $10506 per patient. Finally, we also saw a decrease in the proportion of patients expiring on CRRT, and an increase in the proportion of patients transitioning to comfort care.
26 Feb Heart Attacks Rarely Misdiagnosed in Emergency Rooms
MedicalResearch.com Interview with: Daniel A. Waxman, MD, PhD
Department of Emergency Medicine
David Geffen School of Medicine
University of California, Los Angeles
RAND Corporation Santa Monica, California
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: When people talk about medical error, they are usually referring to treatment error—giving the wrong medication, operating on the wrong side of the body, etc. But many believe that diagnostic error—the failure to diagnose a condition when a patient seeks care—is at least as widespread and consequential a problem. However, diagnostic errors are intrinsically difficult to measure, since one can rarely prove that a condition was present at the time it was not diagnosed.
In this study, we introduce a novel method for measuring how often patients who come to the emergency room with symptoms of an imminent cardiovascular emergency such as acute myocardial infarction (heart attack) are discharged home without a diagnosis.
We find that among Medicare patients whose ER visits were attributable to symptoms of an imminent infarction, only about 2.3% were discharged home, and that the figure was under 5% for each of the other four conditions we studied. However, we also found that these relatively low rates did not improve between 2007 and 2014.
26 Feb Despite Advancing Neonatal Health, Preterm Babies Still Risk Cognitive Impairment
MedicalResearch.com Interview with: [caption id="attachment_40257" align="alignleft" width="149"] Sabrina Twilhaar[/caption]
Sabrina Twilhaar, MS, PhD candidate
Child Study Group, sectie Klinische Neuropsychologie
Vrije Universiteit Amsterdam
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: It is well-known that preterm birth has negative consequences for cognitive development.
During the early 1990s important progress in neonatal health care resulted in a considerable increase in the survival of preterm infants. Earlier meta-analyses showed large differences in intelligence between very preterm and full-term born children. However, these meta-analyses included mostly studies on children born before 1990. Because of the advances in neonatal health care since that time, it was important to update our knowledge on the outcomes of more recently born preterm infants. We combined the results of 71 studies, together including 7752 very preterm and 5155 full-term born children, and found a difference in intelligence between very preterm and full-term children that was still large.
Interestingly, despite advancing neonatal health care, we also found no indication of improvement in the cognitive outcomes of very preterm born children during the period from 1990 to 2008. In addition, we searched for factors that increase the risk for poor cognitive outcomes in these children and we found that children with a chronic lung disease that is amongst others caused by mechanical ventilation of the immature lungs are even more at risk for poor cognitive outcomes.
22 Feb USPSTF: Ovarian Cancer Screening Not Recommended in Low-Risk, Asymptomatic Women
MedicalResearch.com Interview with: [caption id="attachment_40206" align="alignleft" width="143"] Dr. Barry[/caption]
Michael J. Barry, M.D., Task Force member
Director of the Informed Medical Decisions Program
Health Decision Sciences Center
Massachusetts General Hospital.
Professor of Medicine
Harvard Medical School and
Physician at Massachusetts General Hospital
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Ovarian cancer is the fifth leading cause of cancer death among women in the United States. It is hard to detect, and many women diagnosed with ovarian cancer do not show signs or symptoms early on. As a result, ovarian cancer is often diagnosed at a late stage, when it is hard to treat successfully.
The U.S. Preventive Services Task Force looked at the latest evidence to see if screening women who do not have signs or symptoms of ovarian cancer can prevent them from dying of the disease. Unfortunately, we found that screening for ovarian cancer does not decrease the number of women who die, but it does lead to some women having unnecessary surgery to remove their ovaries. As a result, we are recommending against ovarian cancer screening in women who are not at high risk.
22 Feb Study Finds No Benefit To Prophylactic Haldol For Delirium in ICU
Posted at 12:08h
in Author Interviews, Critical Care - Intensive Care - ICUs, JAMA, Mental Health Research
MedicalResearch.com Interview with:
 Mark van den Boogaard, PhD, RN, CCRN
Assistant Professor
Department of Intensive Care Medicine
Radboud University Medical Center
Nijmegen Netherlands
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Delirium is affecting many of our intensive care unit (ICU) patients which is impacting their recovery on the short-term as well as on the long-term. Therefore we were very interested to investigate if the use prophylactic haloperidol would be beneficial for the ICU patients. Especially because there were indications that it would be effective in ICU delirium prevention and also because this drug is being used in daily practice to prevent ICU delirium although there is no clear evidence. The overall finding of our large-scale well designed study is that we didn’t find any beneficial effect of prophylactic haloperidol in ICU patients. Moreover, this finding is very consistent over all groups of patients.
21 Feb Despite Promise, EMRs Have Not Reduced Administrative or Billing Expenses
[caption id="attachment_40182" align="alignleft" width="200"] Prof. Barak Richman[/caption]
MedicalResearch.com Interview with:
Barak Richman JD, PhD
Bartlett Professor of Law and Business Administration
Duke University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The US not only has the highest health care costs in the world, we have the highest administrative costs in the world. If we can reduce non-value added costs like the ones we document, we can make substantial changes in the affordability of health care without having to resort to more draconian policy solutions.
Our paper finds that administrative costs remain high, even after the adoption of electronic health records. Billing costs, for example, constituted 25.2% of professional revenue for ED departments and 14.5% of revenue for primary care visits. The other numbers are captured below.
[caption id="attachment_40183" align="alignleft" width="680"]
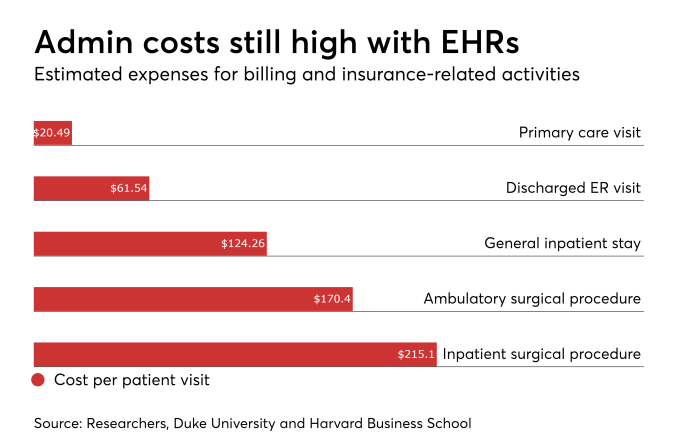 Administrative Costs Still High With EHRs[/caption]
20 Feb Despite Safe Sleeping Recommendations, Infant Suffocations Continue To Rise
MedicalResearch.com Interview with: Guoqing Hu, PhD Department of Epidemiology and Health Statistics Xiangya School of Public Health Central South University Changsha, Hunan, China On behalf of the authors MedicalResearch.com: What is the background for this study? What are the main findings? Response: We've known for some time that suffocation is a leading cause of death for American infants - in fact, it is the cause of over 3/4 of the injury deaths to babies under 12 months of age. We've also known that there are strategies, such as "safe sleeping", that can greatly reduce the risk of a baby suffocating to death. The surprise in our study is that the suffocation rate for infants under 12 months of age appears to be increasing in the United States over the past 15 years. More babies are dying from suffocation today than in the 1990s, and that is a significant public health concern. Think about the implications of each one of those deaths to the infant's parents and loved ones. There are few things more devastating than losing a baby to an unintentional, or "accidental" death. There are ways we can prevent unintentional suffocations, and we need to work together to inform parents and ensure babies are kept safe to reduce those deaths, especially as rates in the US appear to be increasing.19 Feb Bariatric Surgery Associated With Reduced Need For Diabetes Medications at Six Years
MedicalResearch.com Interview with: Dr Jérémie Thereauz Praticien Hospitalier Chirurgie viscérale et digestive MedicalResearch.com: What is the background for this study? What are the main findings? Response: Bariatric surgery has been proved to reduce type 2 diabetes in morbid obese patients. However, results of bariatric surgery at a nationwide level are lacking. The aim of our study...
16 Feb Aggressive Systolic Blood Pressure Control In Older Patients With HFpEF Should Be Avoided
 MedicalResearch.com Interview with:
Dr. Apostolos Tsimploulis, Chief Medical Resident
Dr. Phillip H. Lam, Chief Cardiology Fellow
The Washington, DC Veterans Affairs Medical Center, Georgetown University, and
MedStar Washington Hospital Center, Washington, DC
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Hypertension is a major risk factor for the development of new heart failure (HF). Findings from multiple randomized controlled trials in hypertension have consistently demonstrated that controlling systolic blood pressure (SBP) to normal levels such as to SBP <120 mm Hg reduces the risk of developing new HF.
However, interestingly, once patients develop heart failure, those with a normal SBP value such as SBP <120 mm Hg tend to have poor outcomes. This paradoxical association – also called reverse epidemiology – although poorly understood – has been described with other HF risk factors such as smoking and obesity. Regarding poor outcomes associated with lower SBP in HF patients with reduced ejection fraction (HFrEF – pronounced Hef-ref), it has been suggested that it may be a marker of weak heart muscle that is unable to pump enough blood. However, less is known about this association in patients with HF and preserved ejection fraction (HFpEF – pronounced Hef-pef) –– the heart muscle is not weak in the traditional sense.
This is an important question for a number of reasons: nearly half of all heart failure patients have HFpEF which accounts for about 2.5 to 3 million Americans. These patients have a high mortality similar to those with HFrEF – but unlike in HFrEF few drugs have been shown to improve their outcomes. Thus, there is a great deal of interest in improving their outcomes. One of those approaches is to control . systolic blood pressure and the 2017 ACC/AHA/HFSA Focused Update of the HF guidelines recommend that SBP “should be controlled in patients with HFpEF in accordance with published clinical practice guidelines to prevent morbidity.”
Thus, our study was designed to answer that simple question: do patients with HFpEF and SBP <120 mmHg, which is considered to be normal SBP, have better outcomes than those with SBP ≥120 mmHg.
Using a sophisticated approach called propensity score matching we assembled two groups of patients with HFpEF – one group with SBP <120 mmHg and the other groups had SBP ≥120 mmHg – and patients in both groups were similar in terms of 58 key baseline characteristics. In this population of balanced patients with HFpEF, those with a normal systolic blood pressure had a higher risk of mortality – starting 30 days post-discharge up to about 6 years. Finding from our restricted cubic spline plots suggest that compared with SBP <120 mm Hg, SBP values ≥120 mm Hg (up to 200 mm Hg) was not associated with a higher risk of death.
13 Feb Paid Family and Childbearing Leave Policies at Top US Medical Schools Found Lacking
MedicalResearch.com Interview with: [caption id="attachment_39927" align="alignleft" width="142"] Dr. Mangurian[/caption]
Christina Mangurian, MD, MAS
Associate Professor of Psychiatry
Vice Chair for Diversity, Department of Psychiatry
UCSF Weill Institute for Neurosciences
Director, UCSF Public Psychiatry Fellowship at ZSFG
Core Faculty, UCSF Center for Vulnerable Populations
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: We examined paid family and childbearing leave policies at top-10 medical schools across the US. Despite recommendation from national medical societies for 12 weeks paid childbearing leave because of the benefits to both infant and mother, the average leave at these top schools of medicine was only around 8 weeks. In addition, most policies are very difficult to understand, and are at the discretion of departmental leadership – both of which put women at a disadvantage at getting leave they deserve. Additionally, family leave was only available to the parent that identifies as the "primary caregiver" at five universities, disallowing cooperative parenting.
12 Feb More Car Crashes on 4/20 Marijuana Celebration Day
MedicalResearch.com Interview with: Dr. John A Staples
MD, FRCPC, MPH
Scientist, Centre for Health Evaluation and Outcome Sciences
Clinical Assistant Professor
University of British Columbia
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: Around 64 million Americans live in states that have legalized recreational marijuana. Many policymakers are trying to figure out what that means for traffic safety.
On April 20th, some Americans participate in an annual "4/20" counterculture holiday that celebrates and promotes the use of cannabis. Some 4/20 events such as those in Denver and San Francisco involve thousands of participants. Much like celebrations at midnight on New Year's eve, public 4/20 events sometimes mark 4:20 p.m. by a countdown followed by synchronized mass consumption of cannabis. We thought this was a perfect natural experiment to evaluate the influence that cannabis intoxication has on the risk of motor vehicle crash.
To examine this question, we analyzed 25 years of data on all fatal traffic crashes in the United States. We compared the number of drivers in crashes between 4:20 p.m. and midnight on April 20th to the number of drivers in crashes during the same time interval on control days one week earlier and one week later.
We found that the risk of crash involvement was 12% higher on April 20th than on control days. In the subgroups of drivers younger than 21 years of age, the risk of crash involvement was 38% higher on April 20th than on control days.
Assuming fewer than 12% of Americans celebrate 4/20, our results suggest that substance use at April 20th celebrations more than doubles the risk of fatal crash.
10 Feb Distance to Trauma Center & Prehospital Care Influence Outcomes from Injuries
MedicalResearch.com Interview with: [caption id="attachment_39864" align="alignleft" width="200"] Dr. Jarman[/caption]
Dr. Molly Jarman PhD
Postdoctoral Research Fellow at
Brigham and Womens Hospital
MedicalResearch.com: What is the background for this study?
Response: Injuries are a leading cause of death and disability in the US, and there are well documented disparities in injury incidence and outcomes. Certain populations (i.e. rural, low income, people of color) experience more injury than others, and are more likely to die following and injury.
Past studies focused on individual health and socioeconomic characteristics as the primary driving force behind these disparities, along with variation in the time required to transport an injured patient to the hospital. We wondered if geographic features of an injury incident location contributed to variation in injury mortality that was not explained by differences in individual patient characteristics.
In other words, we know that who you are contributes to injury mortality, and we wanted to know if it also matters where you are when an injury occurs.
08 Feb With or Without Reconstruction, Hard To Predict How You Will Feel After Mastectomy
MedicalResearch.com Interview with: Dr. Clara Nan-hi Lee, MD
Comprehensive Cancer Center
The Ohio State University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: The decision about breast reconstruction is very challenging because it’s unfamiliar, involves complex risk information, affects very personal concerns, and happens at a stressful time. One of the challenges is to predict how one will feel after the surgery. We know from psychology research that people often mis-predict their future emotions. So we were interested to see how well women predict their future well being after surgery.
The main findings are that patients having mastectomy without reconstruction believed they would be less satisfied than they turned out to be. And patients having mastectomy with reconstruction believed they would be more satisfied than they turned out to be.
01 Feb First Signs of Psychotic Disorder May Appear in Childhood With Drop in IQ
MedicalResearch.com Interview with: Josephine Mollon PhD Department of Psychosis Studies, Institute of Psychiatry, Psychology, and Neuroscience King’s College London, London, England Currently with the Department of Psychiatry Yale University School of Medicine New Haven, Connecticut MedicalResearch.com: What is the background for this study? Response: Psychotic disorders, such as schizophrenia, are severe mental disorders that cause a range of abnormalities in perception and thinking. Individuals with psychotic disorders also experience severe impairments in IQ and there is evidence that these impairments begin many years before hallucinations and delusions first appear. Understanding how and when individuals with psychotic disorder experience a drop in IQ scores will help us better predict and treat poor cognition in these individuals, and perhaps even the disorder itself.01 Feb Vancouver Study: 100% of Opioid-Users Tested Positive for Fentanyl
MedicalResearch.com Interview with: William G. Honer, MD, FRCPC, FCAHS
Jack Bell Chair in Schizophrenia
Professor and Head, Department of Psychiatry
University of British Columbia
Vancouver, BC
MedicalResearch.com: What is the background for this study?
Response: The Province of British Columbia, Canada, has experienced a tremendous increase in the number of opioid related overdoses and deaths. In 2012, there were 269 drug overdose deaths, five years later in 2017 the overdose deaths are predicted to have increased 500%. Toxicology studies of deaths, and examination of seized drugs indicate fentanyl is the major cause.
These indirect measures suggest widespread exposure to fentanyl in opioid users, however direct studies of the extent of exposure of opioid users to fentanyl in the community are lacking. We carried out a community-based, longitudinal study using fentanyl testing in urine samples from volunteer participants. (It is called the “Hotel Study” since many of the participants live, or have lived in single room occupancy hotels)
01 Feb Potentially Cancerous Genital Lesions Common in Transplant Population
MedicalResearch.com Interview with:
[caption id="attachment_39776" align="alignleft" width="159"] Dr. Chung[/caption]
Dr. Christina Lee Chung, MD Associate Professor Department of Dermatology Drexel University
MedicalResearch.com: What is the background for this study? What are the main findings?
Response: In early 2016, five years after the inception of our specialty medical-surgical transplant dermatology center, we realized our nonwhite transplant patients were developing skin cancer at higher rates and found interesting trends. These data were published in a previous manuscript. One of the more striking findings was that these patients were developing a high proportion of skin cancer in non-sun-exposed areas such as the genital region. There are no standard guidelines regarding genital skin evaluation and it is unclear how often it is performed in any capacity amongst dermatologists, including practitioners in our center, quite frankly. Our group was concerned that we could be missing skin cancers in this “hidden” area in our high-risk organ transplant population so we launched a quality improvement initiative that incorporated thorough genital skin evaluation as a standard part of post-transplant skin cancer screening.
Fifteen months after we started this modified screening process, we decided to evaluate the results. To account for any variation in examination, we looked at the findings of a single practitioner. We found that genital lesions are common in the transplant population and include high rates of genital warts and skin cancer. However, patient awareness of the presence of genital lesions was alarmingly low. Nonwhite transplant patients, Black transplant recipients in particular, were disproportionately affected by both genital warts and genital skin cancer in our cohort. Similar to cervical cancer, high-risk HPV types were closely associated with genital squamous cell carcinoma development in our transplant population.
31 Jan Rate of Breast Biopsy After Cancer Treatment Relatively Low, and Most Are Benign
MedicalResearch.com Interview with: [caption id="attachment_39729" align="alignleft" width="140"] Dr. Kuerer[/caption]
Henry M. Kuerer, MD, PhD, FACS
Executive Director, Breast Programs
MD Anderson Cancer Network
Endowed Distinguished Professor in Cancer Research
Division of Surgery
MedicalResearch.com: Why did you undertake this study?
Response: Many of our patients feel very overwhelmed with their new cancer diagnosis and have concern over the future need for biopsies. Many think that complete removal of the breast is a good way to prevent future cancer-related biopsies. We did not have any good comprehensive data on the incidence of needing biopsies during follow-up for breast cancer.
As a surgeon this information is something that I can use daily when discussing breast cancer treatment options regarding future expectations following breast cancer treatment.